Related Experiment Video
Updated: Aug 11, 2026

Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
Hypernatremia in the very low birthweight infant

Insights
Forty percent of very low birthweight infants developed hypernatremia (high serum sodium). This was linked to increased weight loss and radiant energy exposure, suggesting dehydration as a cause.
Area of Science:
- Neonatology
- Pediatric Endocrinology
Background:
- Hypernatremia is a critical electrolyte imbalance in neonates.
- Very low birthweight infants are particularly vulnerable to fluid and electrolyte disturbances.
Purpose of the Study:
- To determine the incidence and causes of hypernatremia in very low birthweight infants within the first 72 hours of life.
- To identify factors associated with hypernatremia development in this population.
Main Methods:
- Retrospective analysis of clinical data from 25 very low birthweight infants.
- Assessment of serum sodium levels, weight changes, fluid intake, sodium intake, and radiant energy exposure.
- Correlation analysis between hypernatremia severity and clinical parameters.
Main Results:
- Ten infants (40%) developed hypernatremia (serum sodium >= 150 mEq/l).
- Hypernatremia was associated with significantly greater daily weight loss (5.3% vs 1.7%) and increased radiant energy exposure.
- Severity of hypernatremia correlated with lower birthweight and greater postnatal weight loss, but not with fluid or sodium intake.
Conclusions:
- Dehydration, likely due to increased insensible water loss, is a probable cause of hypernatremia in very low birthweight infants.
- An estimated optimal fluid requirement of 150 ml/kg/day is suggested for these infants in the studied environment.
- Close monitoring of weight loss and fluid balance is crucial for preventing hypernatremia in vulnerable neonates.
Abstract:
The incidence and cause of hypernatremia in twenty-five very low birthweight infants were determined by a retrospective analysis of their clinical course during the first 72 hours of life. Ten (40%) developed a serum sodium greater than or equal to 150 mEq/l. This was associated with a greater weight loss than found in normal infants (5.3 +/- 2.6%/day vs 1.7 +/- 2.3%/day, p less than .05) and with more time spent under radiant energy, but not with the amount of water, or sodium received. The severity of hypernatremia correlated with birthweight (r = -.47, p less than .05) and with postnatal weight loss but not with sodium intake. The excess weight loss in the hypernatremic group, when added to their average measured fluid intake suggests an estimated optimal fluid requirement of 150 ml/kg/day in the environment described. The hypothesized mechanism for hypernatremia is dehydration, possibly through insensible water loss.
Related Concept Videos
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 01:24
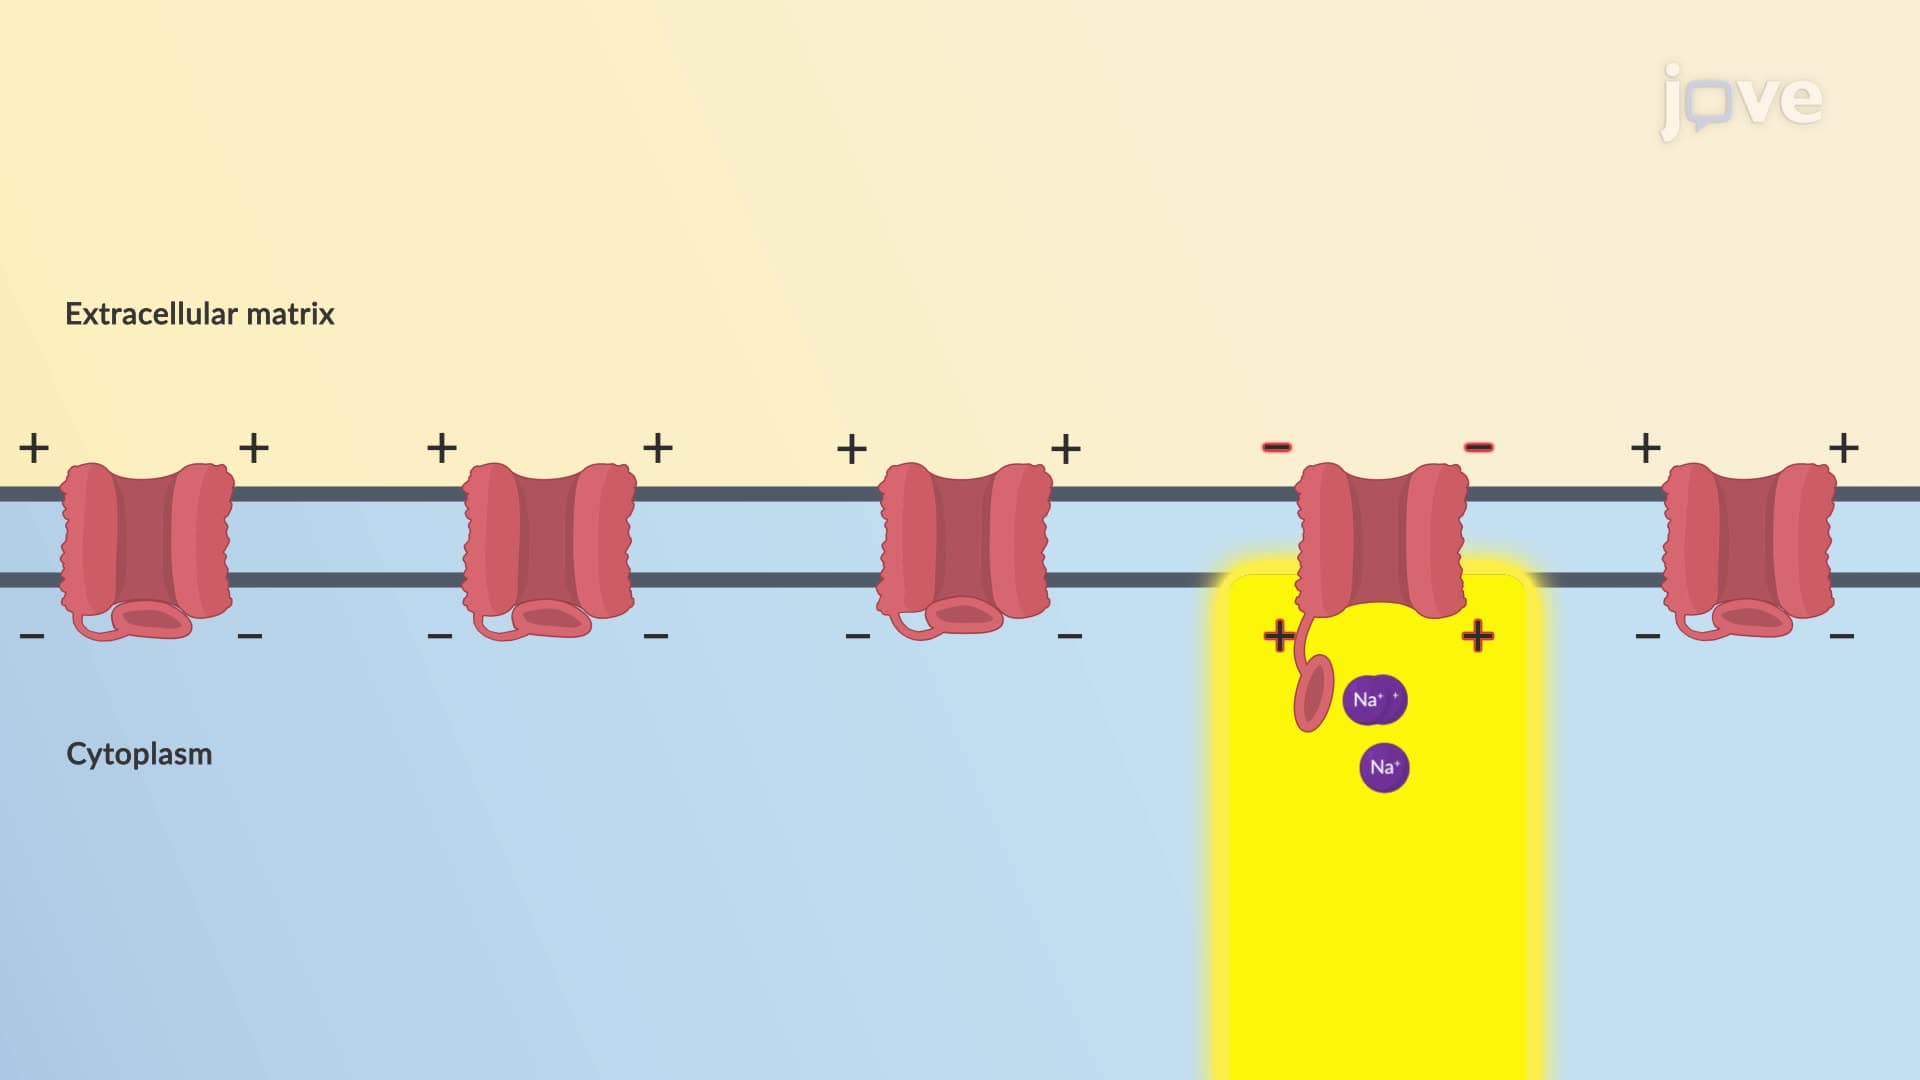
Roles of Electrolytes: Sodium and Potassium
 01:21
Hyperosmolar Hyperglycemic State