Tetanus after anorectal abscess

Insights

Tetanus can complicate anorectal procedures and abscesses. Prompt treatment, including antibiotics and tetanus prophylaxis, is crucial for recovery from this serious infection.

Area of Science:

  • Medical Case Reports
  • Infectious Diseases
  • Surgical Complications

Background:

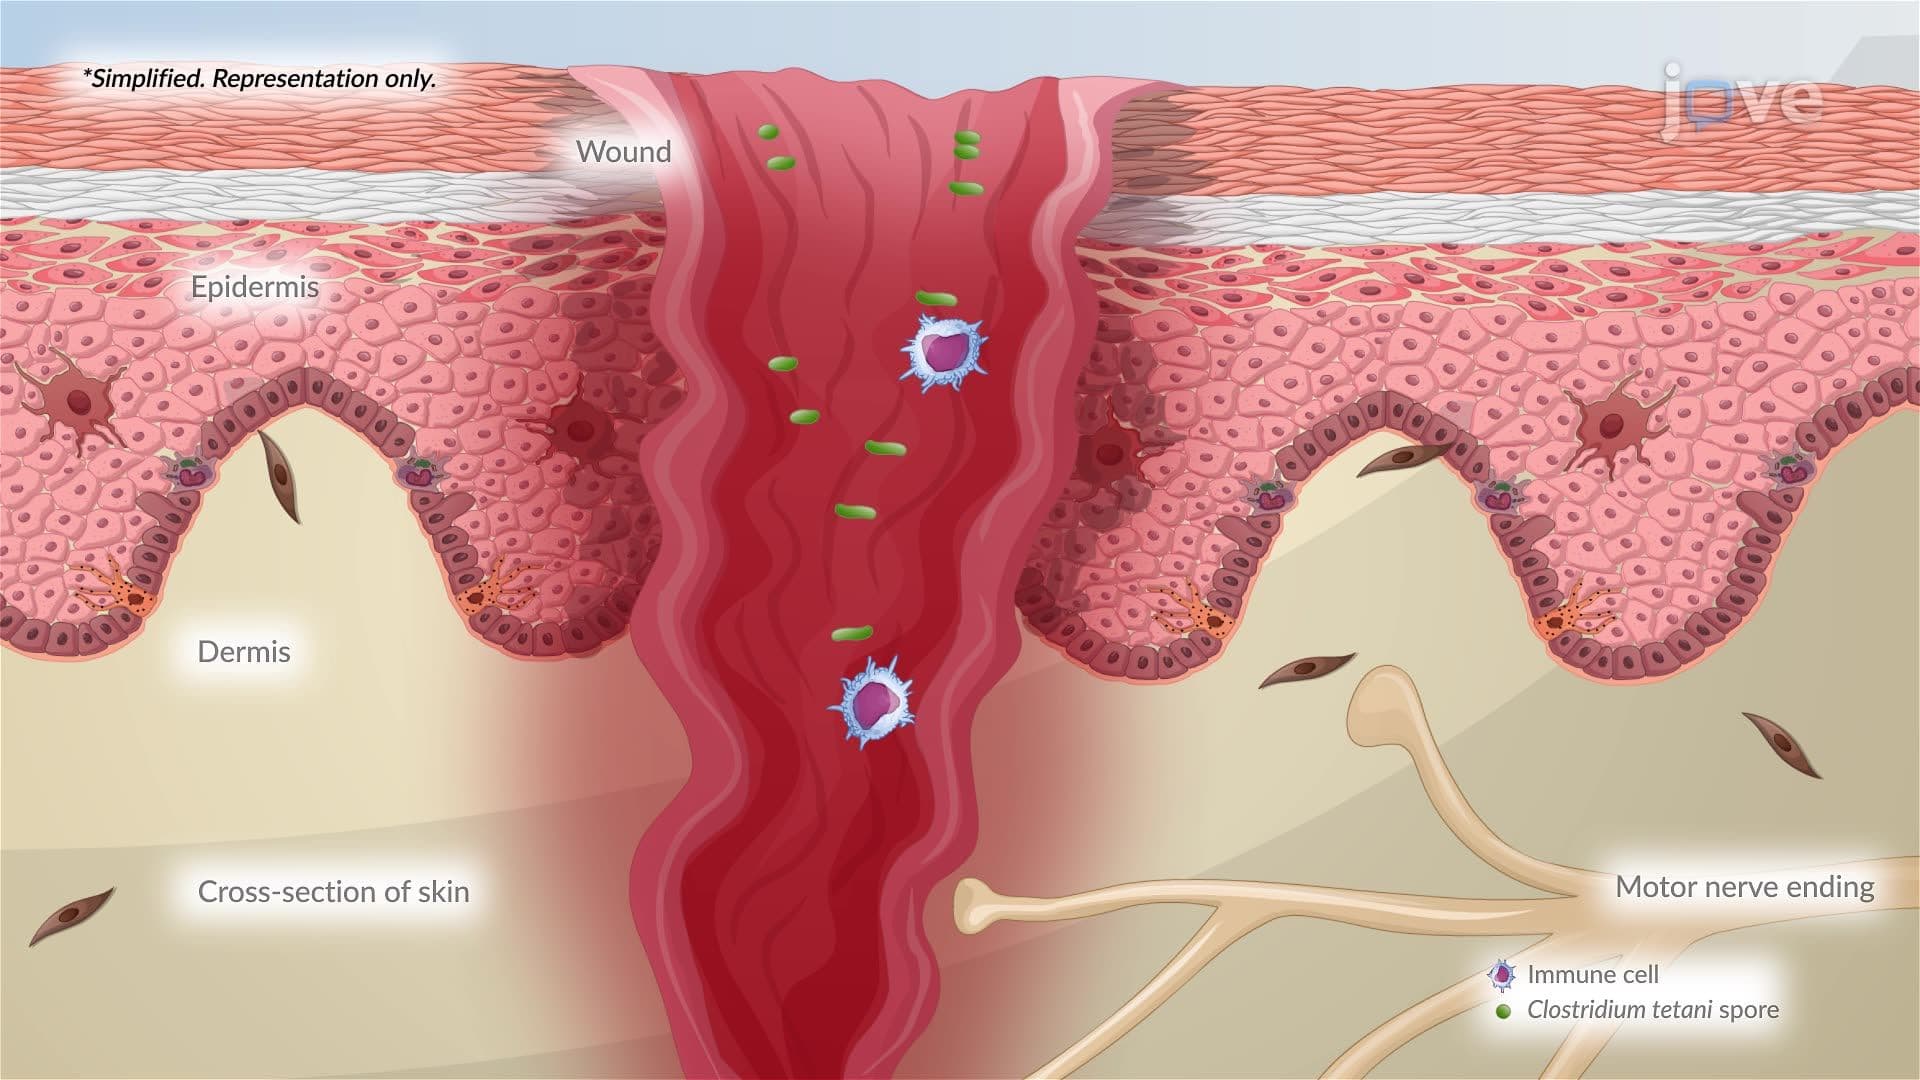
  • Tetanus is a serious bacterial infection caused by Clostridium tetani.
  • Anorectal conditions, including abscesses and surgical sites, can be susceptible to infection.
  • Understanding potential complications is vital for patient management.

Observation:

  • A 62-year-old male developed a synergistic perineal infection 8 days post-anorectal abscess drainage.
  • Despite debridement, antibiotics, and tetanus prophylaxis, tetanus symptoms manifested the following day.
  • The patient required intensive care, including muscle relaxants and ventilatory support.

Findings:

  • This case highlights tetanus as a potential complication following anorectal procedures or abscesses.
  • Early and aggressive treatment, including surgical intervention and supportive care, is essential for managing tetanus.
  • Tetanus prophylaxis may not always prevent disease if an active infection is present.

Implications:

  • Anorectal surgery and abscess management require vigilant monitoring for tetanus.
  • Reinforces the importance of complete wound care and timely tetanus immunization updates.
  • Highlights the need for prompt recognition and aggressive management of tetanus in surgical patients.

Related Concept Videos

Aneurysm III: Interprofessional Care01:26

Aneurysm III: Interprofessional Care

Aneurysm management involves either conservative medical therapy or surgical intervention, depending on the size and symptoms of the aneurysm. Conservative management is generally reserved for smaller, asymptomatic aneurysms, while larger or symptomatic aneurysms often necessitate surgical repair.Conservative Medical TherapyFor small, asymptomatic aneurysms, particularly abdominal aortic aneurysms (AAA) less than 5.5 centimeters in diameter, conservative medical therapy is recommended. This...
Aneurysm IV: Nursing Management01:22

Aneurysm IV: Nursing Management

Vigilant monitoring for aneurysm rupture is essential for patients undergoing aortic surgery.Preoperative Nursing ManagementContinuously monitor the patient for manifestations of aneurysm rupture, such as pallor, weakness, tachycardia, hypotension, abdominal, back, groin, or periumbilical pain, changes in consciousness, and a pulsating abdominal mass. Regularly assess the patient's peripheral pulses.Instruct the patient to consume a clear liquid diet the day before surgery and administer...
Tetanus01:29

Tetanus

Tetanus is a life-threatening neurological disorder characterized by persistent muscle contractions and spastic paralysis. It is caused by Clostridium tetani, a motile, Gram-positive, rod-shaped, obligate anaerobe. These bacteria produce terminal endospores, giving them a distinctive “lollipop” or “tennis-racket” appearance. They thrive in anaerobic environments, such as those found in deep puncture wounds.Once introduced into the body, the spores germinate into vegetative cells. These cells...
Botulism01:22

Botulism

Botulism is a life-threatening neuroparalytic condition caused by botulinum neurotoxin, which is produced by the bacterium Clostridium botulinum, a Gram-positive, spore-forming, obligate anaerobe.In adults, the toxin enters the body in different ways: in foodborne botulism, the preformed toxin is absorbed in the intestine. In wound botulism, spores grow in injured tissue and release the toxin into the blood. Infant botulism differs mechanistically from adult forms. In infants, botulism commonly...
Brain Abscess l: Introduction01:26

Brain Abscess l: Introduction

A brain abscess is a focal, intracerebral infection characterized by a localized collection of pus within the brain parenchyma, resulting from microbial invasion and the body’s inflammatory response. It progresses through stages: early and late cerebritis, followed by early and late capsule formation, reflecting tissue destruction, immune response, and eventual encapsulation.Etiology and PathogenesisCausative organisms vary with source and host factors, often involving polymicrobial infections,...
Intestinal Obstruction II: Pathophysiology01:07

Intestinal Obstruction II: Pathophysiology

Intestinal obstruction triggers a series of physiological responses, starting with gas and fluid accumulation in the bowel segment proximal to the obstruction, leading to distension. This distended intestine compresses the diaphragm, hindering lung expansion and potentially leading to reduced respiratory effort, atelectasis, and pneumonia.To overcome the blockage, the gut intensifies contractions, causing colicky abdominal pain, nausea, and vomiting, which reduces fluid and food intake and...