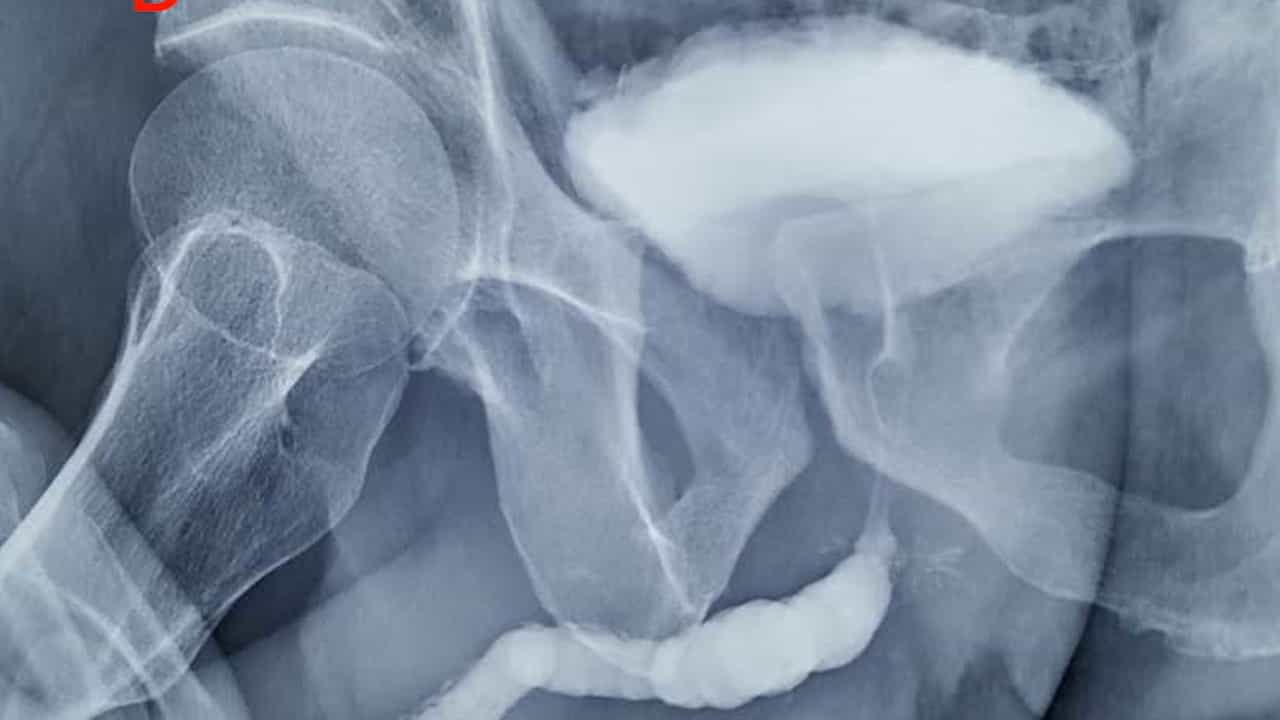
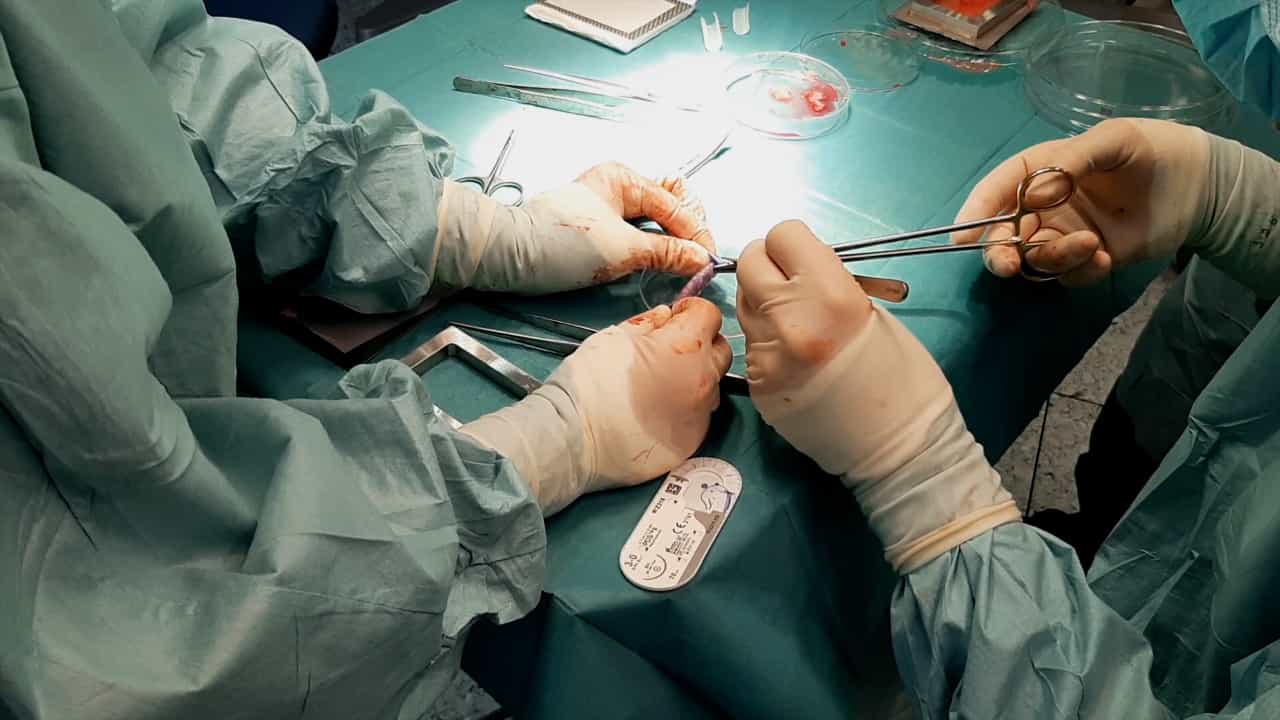
[Vascular supply preserving repair of megaureter with tailoring in two layers]

Abstract:
Since 1976 we have tapered extremely wide obstructive or refluxive megaureters with partial fibrosis by this new technique, sometimes over 2/3 of length with ureterolysis above. In these cases preserving of the mesoureteric vascular supply is important additional to the regular intramural nutrition. The mesoureteric arteries and veins spread into the adventitia and turn around in curves like a network. An exactly linear resection would damage this. Therefore we remove the adventitia from the lateral side, resect beneath the abundant strip of muscularis with mucosa trimming the megaureter downwards to a diameter of 7 to 4 mm, close the inner layer with running and interlocking 5-0 chromic suture over a splint and then readapt the adventitia. The advantages are: better arterial vascular supply, minimal thrombosis, no necrosis and no urinary leakage, less scarring and therefore good peristalsis.