Related Experiment Video
Updated: Aug 15, 2026
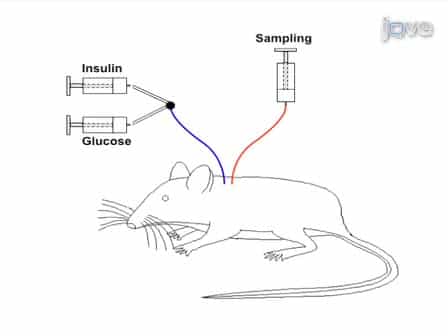

Hyperinsulinemic-Euglycemic Clamp in the Conscious Rat
Published on: February 7, 2011
Glucagon-induced hypocalcemia in the rat: effects of maturation and insulin

Abstract:
In adults of several species including man, a small transient decrease in serum calcium concentration follows glucagon administration in doses of 1 to 10 mg/kg. The effects of maturation and insulin on this phenomenon were assessed by comparing the response of newborn and adult rats to equivalent doses of glucagon with and without prior insulin administration. After injection of 1 microgram/g of glucagon, the decrease in serum calcium concentration at 60 min was significant in the newborn rats (-1.75 mg/dl; P less than 0.001) and not significant in the intact adults (-0.07 mg/dl; P greater than 0.1). In pancreatomized adults, the decrease in serum calcium after the same dose of glucagon became significant (-1.23 mg/dl; P less than or equal to 0.01). This hypocalcemic effect was prevented in the pancreatectomized adult rat if insulin in a dose of 0.01 micron/g was given 15 min before glucagon. In the newborn rats, the same dose of insulin decreased the hypocalcemic effect, but the change was still significant (-0.74 mg/dl; P less than 0.01). Glucagon decreased serum calcium at one hr in newborn rats but not in adults. After pancreatectomy, the adult response to glucagon was significant and similar to that of the newborn. Insulin cancelled this effect of glucagon in the pancreatectomized adults and reduced it in the newborns.


Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:28
Insulin: The Receptor and Signaling Pathways
 01:15
Hypoglycemia and Glucagon
 01:19
Type I Diabetes III: Clinical Manifestations
 01:24
Type II Diabetes II: Pathophysiology