Pathogenesis of nitrogen dioxide-induced respiratory lesions in reference to respiratory clearance of inhaled particulates
Related Experiment Video
Updated: Aug 11, 2026
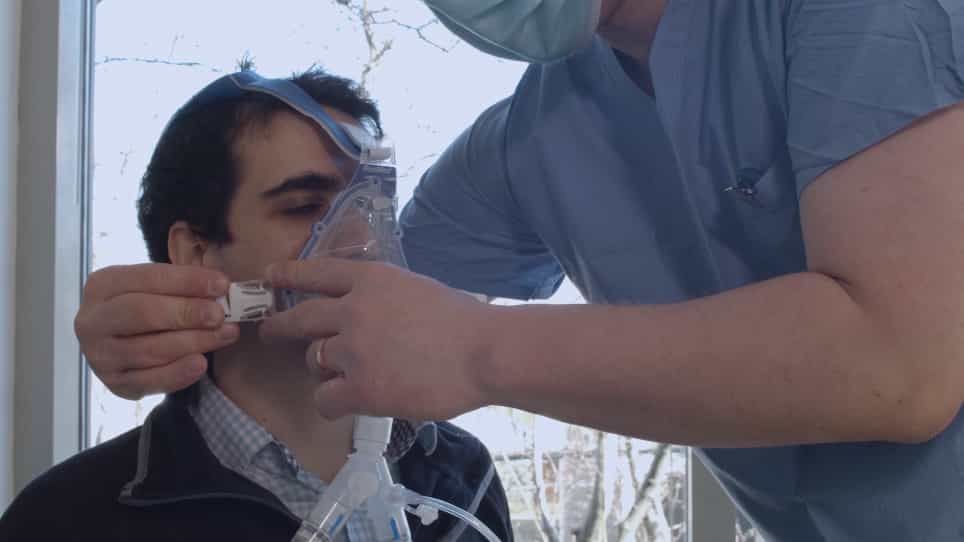
A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021

Abstract:
The pathogenesis of NO2-induced respiratory disease and the effect of NO2 on respiratory clearance of 51Cr2O3 were studied. Young adult female mice were exposed to a 51Cr2O3 aerosol, followed by a daily exposure to either 30 ppm NO2 for 2 wk or 60 ppm NO2 for 2 wk or a single exposure to 170 ppm NO2. Exposure to 30 ppm NO2 had a minimal histopathologic effect on respiratory tract tissue. Exposure to 60 ppm NO2 produced marked histopathologic effects, which were subsequently resolved. Exposure to 170 ppm NO2 produced permanent histopathologic lesions. In mice exposed to concentrations of NO2 that produced minimal histopathologic effects, respiratory clearance of 51Cr2O3 was similar to that in unexposed mice. When mice were exposed to concentrations of NO2 that produced permanent tissue damage, prolonged impairment of respiratory clearance of 51Cr2O3 was observed, despite resolution of edema produced by inhalation of NO2. At concentrations of NO2 that produced marked edema and histopathologic effects that were resolved despite repeated NO2 exposure, there was an initial marked impairment of respiratory clearance, then an accelerated rate of clearance, and finally a clearance rate similar to that of unexposed mice. The time during which accelerated clearance occurred was well correlated with the time at which the histopathologic lesions was observed to regress.
Insights
Nitrogen dioxide (NO2) exposure can impair respiratory clearance of particles. While mild NO2 exposure shows minimal effects, high concentrations causing permanent lung damage lead to prolonged clearance issues.
Area of Science:
- Environmental Toxicology
- Respiratory Medicine
Background:
- Nitrogen dioxide (NO2) is a common air pollutant.
- Understanding NO2's impact on respiratory health and particle clearance is crucial.
Purpose of the Study:
- To investigate the pathogenesis of NO2-induced respiratory disease.
- To determine the effect of NO2 on the respiratory clearance of 51Cr2O3 particles.
Main Methods:
- Mice were exposed to 51Cr2O3 aerosol followed by varying concentrations of NO2 (30 ppm, 60 ppm, or 170 ppm).
- Histopathological changes and respiratory clearance of 51Cr2O3 were assessed.
Main Results:
- Low-level NO2 (30 ppm) had minimal histopathological effects.
- High-level NO2 (60 ppm) caused reversible lesions, while 170 ppm caused permanent damage.
- Impaired respiratory clearance correlated with permanent tissue damage, even after edema resolved.
Conclusions:
- NO2-induced respiratory damage affects particle clearance.
- Permanent lung lesions from high NO2 concentrations result in prolonged clearance impairment.
- Reversible lesions show initial clearance impairment followed by accelerated clearance during lesion regression.


Related Concept Videos
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:29
Pneumonia II: Pathophysiology
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:29
Pneumonia I: Introduction