Related Experiment Video
Updated: Aug 11, 2026


Standardized Model of Ventricular Fibrillation and Advanced Cardiac Life Support in Swine
Published on: January 30, 2020
In-hospital mortality after out-of-hospital cardiac arrest
N R Grubb1, R A Elton, K A Fox
1Cardiovascular Research, Units University of Edinburgh, Royal Infirmary of Edinburgh, UK.

Insights
Predicting in-hospital death after out-of-hospital cardiac arrest (OHCA) is crucial. Factors like arrest rhythm and conscious level on admission accurately predict mortality, suggesting resuscitation training can improve outcomes.
Area of Science:
- Emergency Medicine
- Cardiology
- Critical Care Medicine
Background:
- In-hospital management of out-of-hospital cardiac arrest (OHCA) survivors faces challenges in prognostic uncertainty.
- Identifying markers for adverse outcomes is essential for guiding patient care.
Purpose of the Study:
- To identify factors predicting in-hospital death in patients surviving initial OHCA resuscitation.
- To develop a prognostic scoring system for OHCA survivors.
Main Methods:
- Retrospective and prospective analysis of 346 consecutive OHCA cases at a single UK center.
- Investigated pre-arrest, resuscitation, and admission variables, including arrest rhythm, witnessed status, and Glasgow Coma Score.
Main Results:
- Crew-witnessed arrests were associated with lower mortality.
- Arrest rhythm, health professional resuscitation, admission conscious level, and ventilation independently predicted in-hospital mortality.
- A prognostic score based on these factors accurately predicted death in a prospective group; persistent coma >72 hours indicated a poor prognosis.
Conclusions:
- Accurate prognostic assessment of OHCA survivors is feasible upon admission.
- Resuscitator skill is a modifiable factor, suggesting public resuscitation training could reduce mortality rates.
Abstract:
In-hospital management of out-of-hospital cardiac arrest is complicated by uncertainty about prognosis and the need to identify markers of adverse outcome in individuals surviving initial resuscitation. We sought to identify factors that predict in-hospital death among patients who initially survive out-of-hospital cardiac arrest. We investigated 346 consecutive cases of out-of-hospital cardiac arrest received by a single centre in Edinburgh, UK (270 cases examined retrospectively, 76 prospectively). Of the retrospective cohort, 246 cases were thought to be of cardiac origin. There were associations between in-hospital mortality and pre-arrest variables, resuscitation variables, and factors measured during admission. Crew-witnessed arrests were associated with low mortality; arrest rhythm (p < 0.001), resuscitation by a health professional (p < 0.05), conscious level on admission (p < 0.001), and requirement for ventilation (p < 0.05) independently predicted in-hospital mortality. A weighted prognostic scoring system based on three of these variables accurately predicted the likelihood of in-hospital death in the prospective test group. Further assessment of conscious level during admission with the Glasgow coma score predicted mortality rates in the study population, but coma did not predict a hopeless prognosis in individual cases unless it persisted for 72 h or more. Accurate prognostic assessment of out-of-hospital cardiac arrest survivors can be made from information available on admission. Of factors that independently predicted outcome, the skill of the resuscitator is most readily modified. This suggests that public training in resuscitation may reduce mortality rates.
More Related Videos
 08:19
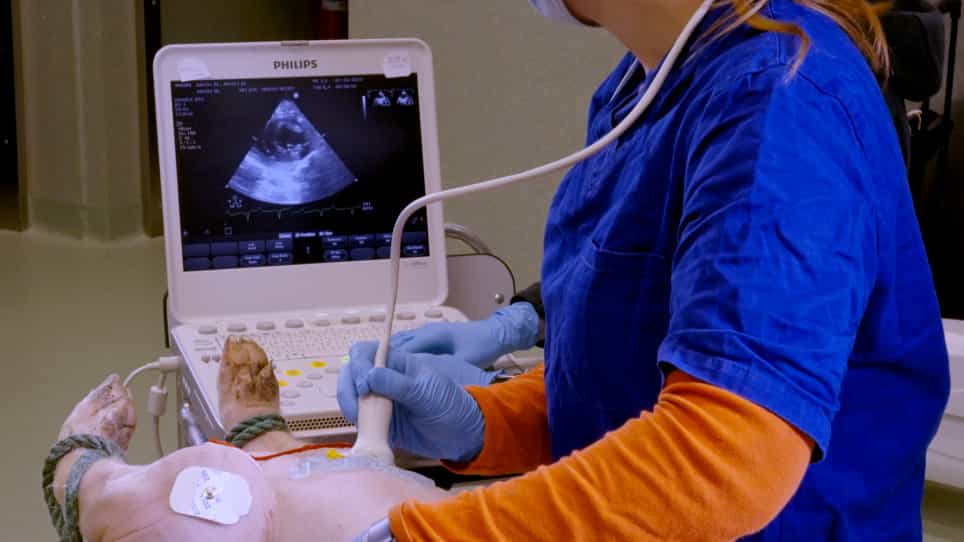
Transthoracic Echocardiography to Assess Post-Resuscitation Left Ventricular Dysfunction After Acute Myocardial Infarction and Cardiac Arrest in Pigs
Published on: July 12, 2022
 03:13
Technical Refinement of a Bilateral Renal Ischemia-Reperfusion Mouse Model for Acute Kidney Injury Research
Published on: November 3, 2023
Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:30
Introduction Cardiac Emergencies
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management