Related Experiment Video
Updated: Jul 24, 2026

Invasive Hemodynamic Characterization of the Portal-hypertensive Syndrome in Cirrhotic Rats
Published on: August 1, 2018
A study of the endocrine manifestations of hepatic cirrhosis

Abstract:
The clinical features and hormonal abnormalities were surveyed in 117 men with cirrhosis of the liver. Compared with healthy men of similar ages, the patients had significantly lower metabolic clearance rates, plasma production rates and total and free levels of testosterone, reduced testosterone responses to human chorionic gonadotrophin stimulation, higher oestradiol, luteinizing hormone and follicle stimulating hormone levels and higher binding capacities of sex steroid binding globulin. The peripheral conversion of testosterone to oestradiol was also found to be significantly increased. However, the metabolic clearance and plasma production rates of oestradiol were not significantly different from those of healthy men. Patients who were severely ill with liver failure and one with haemochromatosis had low levels of luteinizing hormone and follicle stimulating hormone and sub-normal responses to clomiphene and luteinizing hormone-releasing hormone. Higher plasma oestradiol levels were found in patients with gynaecomastia and spider naevi than in those without these signs. However, the clinical features of androgen deficiency--that is, testicular atrophy, impotence and loss of secondary sex hair--were only poorly related to the low testosterone levels, and production rates and longtitudinal studies indicated that the hormonal levels, endocrine features and severity of the liver disease could change independently. It is concluded that the clearance of oestradiol from plasma is not limited by liver disease in all patients, and that reduced degradation of oestrogens is not the initial event in the sequence leading to the hormonal abnormalities of cirrhosis. While gonadotrophin deficiency occurs with liver failure and in some patients with haemochromatosis, the more usual findings are of elevated gonadotrophin levels and a poor Leydig cell response to chorionic gonadotrophin. These suggest that the hypogonadism is primary in most patients with cirrhosis. The causes of the high oestradiol levels were not discovered. Increased peripheral conversion of precursors to oestradiol or increased testicular secretion of oestradiol are possibilities. The high binding capacities of sex steroid binding globulin were not significantly correlated with either the low testosterone or high oestradiol level and the cause of this abnormality remains uncertain. The low metabolic clearance rates of testosterone appeared to result from the increased plasma protein binding of testosterone. The discrepancies in the expected relationships between the hormone and clinical changes suggest that factors other than those studied are also involved in the genesis of the endocrine features of hepatic cirrhosis.
More Related Videos
 12:24
A Three-Dimensional Spheroid Model to Investigate the Tumor-Stromal Interaction in Hepatocellular Carcinoma
Published on: September 30, 2021
 07:56
A Comprehensive Rat Model For Assessing Hepatic Transport Pathways Through Simultaneous Lymphatic And Blood Vascular Sampling
Published on: May 15, 2026
Related Concept Videos
 01:30
Liver Physiology
Metabolic Regulation:
The liver is the central organ involved in regulating blood composition. It stabilizes blood glucose levels, maintaining them within the range of 70–110 mg/dL. When these levels drop, the liver breaks down glycogen reserves and releases glucose into the bloodstream. It can also...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:14
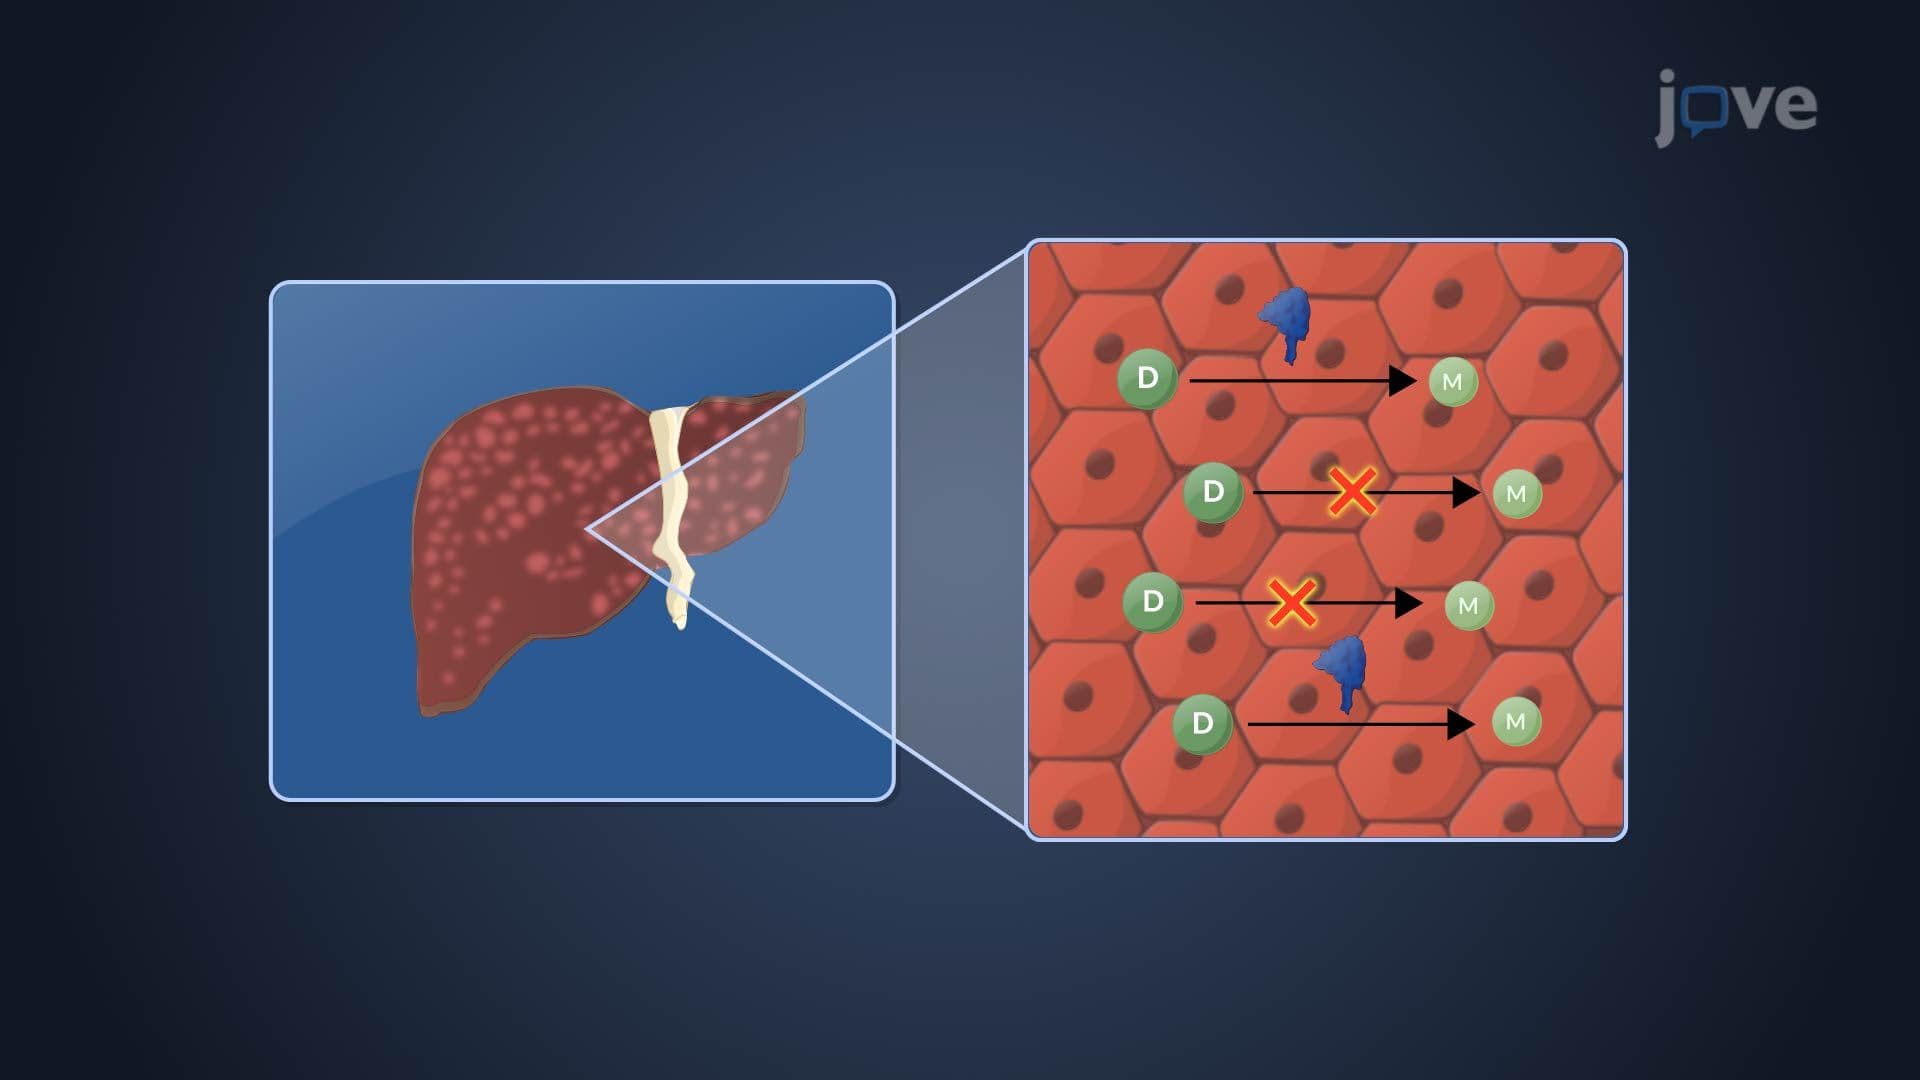
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:23
Cirrhosis I: Introduction
 01:24
Cirrhosis II: Pathophysiology