Related Experiment Video
Updated: Sep 15, 2026


Subcutaneous Infection of Methicillin Resistant Staphylococcus Aureus (MRSA)
Published on: February 9, 2011
Lung abscess in infants and children
1Department of Pediatrics, Children's Memorial Hospital, Northwestern University Medical School, Chicago, Illinois 60614, USA.

Insights
This study reviewed pediatric lung abscess cases, finding that prompt antibiotic therapy is crucial for recovery. Effective treatment for lung abscesses requires parenteral antibiotics targeting Staphylococcus aureus and anaerobes for at least three weeks.
Area of Science:
- Pediatric Pulmonology
- Infectious Diseases
- Thoracic Surgery
Background:
- Lung abscesses are uncommon in children, with primary and secondary forms presenting distinct clinical characteristics.
- Understanding the epidemiology and treatment outcomes of pediatric lung abscesses is essential for effective management.
Purpose of the Study:
- To analyze the clinical features, treatment, and outcomes of primary and secondary lung abscesses in pediatric patients.
- To provide evidence-based recommendations for the optimal management of pediatric lung abscesses.
Main Methods:
- Retrospective review of 28 pediatric patients (18 primary, 10 secondary lung abscesses) over a 6-year period.
- Analysis of patient demographics, abscess characteristics, causative pathogens, treatment strategies, and surgical interventions.
Main Results:
- Primary lung abscesses occurred in children aged 9 months to 20 years, predominantly in older children, while secondary abscesses were seen in younger infants.
- All patients with primary abscesses recovered with treatment, though five required consideration for lobectomy; three secondary abscess patients underwent lobectomy.
- Recommended therapy includes parenteral antibiotics with gram-positive activity against Staphylococcus aureus and anaerobes for a minimum of 3 weeks.
Conclusions:
- Prompt and appropriate antibiotic therapy is key to successful management of pediatric lung abscesses.
- Surgical intervention, such as lobectomy, may be necessary in refractory cases or those with inadequate response to medical management.
- A minimum 3-week course of parenteral antibiotics targeting specific pathogens is recommended for optimal outcomes in pediatric lung abscess treatment.
Abstract:
We retrospectively reviewed 18 cases of primary lung abscess and 10 cases of secondary lung abscess in infants and children during a 6-year period. Among 18 patients with primary abscesses, nine were boys and nine girls, from 9 months to 20 years old, but only two of 18 were less than 5 years old. Each had a solitary abscess. Location of abscesses included the right lower lobe (8), the right upper lobe (3), the left upper lobe (1), and the left lower lobe (6). One patient had Streptococcus pneumoniae bacteremia. Other bacterial isolates were from the upper respiratory tract and of uncertain significance. All patients recovered, although lobectomy was considered necessary in five patients because of failure to respond to intravenous antibiotic therapy. Secondary lung abscesses occurred in six boys and four girls who were from 2 1/2 months to 13 years old. All 10 had solitary, right-sided lesions, seven in the right lower lobe and three in the right upper lobe. Bacteria of unclear significance were recovered from three of 10 patients, while two had documented gram-negative bacteremia. Three secondary abscess patients underwent lobectomy because of perceived inadequate response to medical therapy, including intravenous antibiotics. Based upon the literature and our experience, therapy for pulmonary abscess should include a parenteral antibiotic with gram-positive activity against both penicillinase-producing Staphylococcus aureus and anaerobes for a minimum of 3 weeks.(ABSTRACT TRUNCATED AT 250 WORDS)
More Related Videos


Related Concept Videos
 01:17
Pulmonary Cycle: Exhalation
 01:26
Tonsillitis II: Management
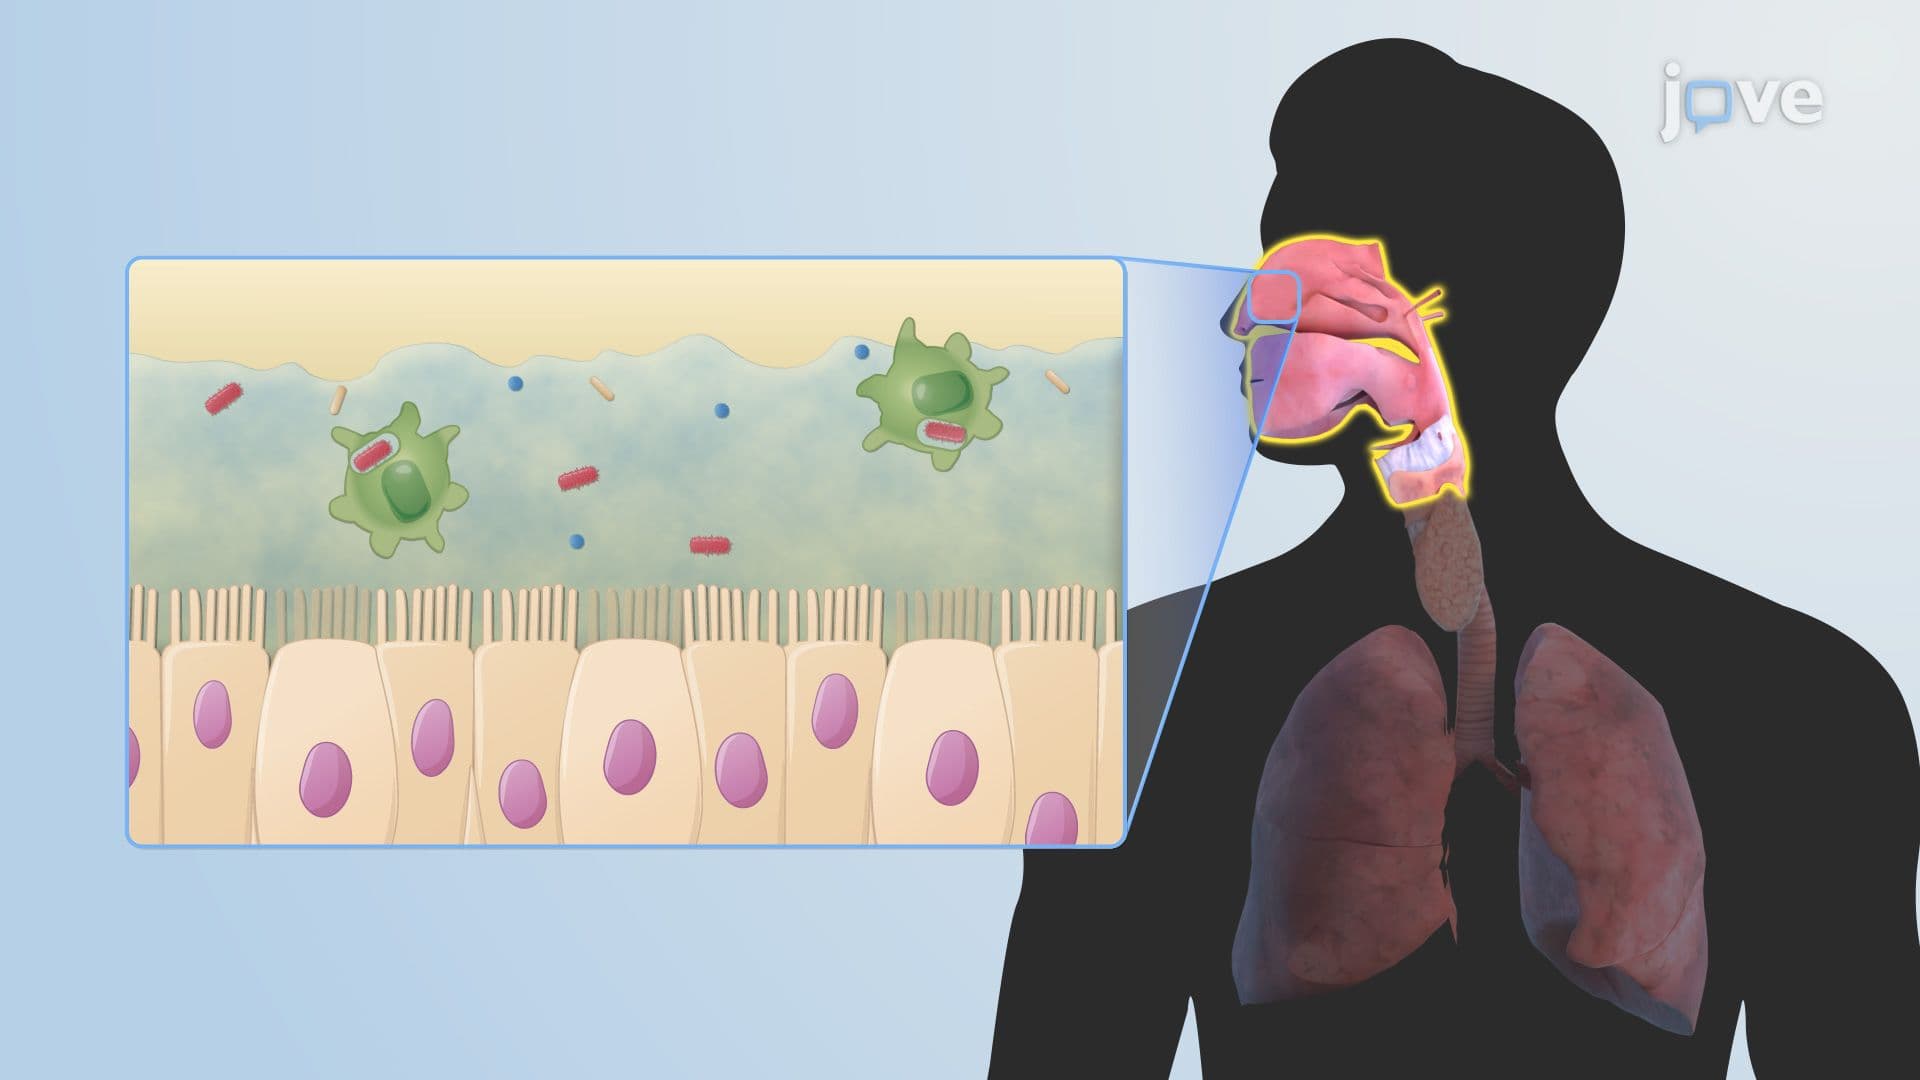 01:29
Microbiota of the Respiratory Tract
 01:26
Brain Abscess l: Introduction
 01:29
Pneumonia I: Introduction
 01:19
Appendicitis