[Growth in children with impairment of thyroid gland function]
Related Experiment Video
Updated: Aug 5, 2026

An Ex vivo Culture System to Study Thyroid Development
Published on: June 6, 2014
1Klinika dĕtí a dorostu FNKV a 3. LF UK, Praha.

Insights
Congenital hypothyroidism (CH) in infants significantly lowers insulin growth factor-1 (IGF-1) levels. Early L-thyroxine treatment normalizes IGF-1, crucial for normal growth and development.
Area of Science:
- Pediatric Endocrinology
- Neonatal Screening
- Growth Factor Research
Context:
- Thyroid function critically impacts growth and bone maturation in children.
- Congenital hypothyroidism (CH) during infancy can cause irreversible central nervous system (CNS) disorders and significant growth impairment.
- Thyroid hormones influence cellular metabolism and growth cartilage activity.
Purpose:
- To investigate the relationship between thyroxine levels and somatomedin C (insulin growth factor-1) production in infants with CH detected via neonatal screening.
- To assess IGF-1 levels in neonates with CH compared to healthy controls.
Summary:
- Thirteen neonates with CH (10-23 days old) showed significantly lower somatomedin (SMA) activity compared to 10 healthy controls (8-20 days old).
- SMA levels were measured using a biological assay before and one month after initiating L-thyroxine treatment.
- Following treatment, SMA levels in the CH group normalized and became comparable to controls.
Impact:
- Early diagnosis and treatment of CH through neonatal screening are vital for normal CNS and physical growth.
- Prompt L-thyroxine substitution therapy is essential for normalizing growth factor production and preventing developmental deficits.
Background:
Changes of thyroid function affect beyond doubt the growth rate and bone maturation. In particular thyroid hypofunction during the first months of life leads not only to irreversible disorders of the development of the CNS but causes also a significant impairment of growth. In older children and adolescents with a more long-lasting thyroid dysfunction milder growth disorders without mental retardation were observed. The effect on growth by thyroid hormones takes place at the level of metabolic processes of every single cell and in particular at the level of growth cartilage. The purpose of our investigation was to test the relationship between the production of the growth factor somatomedin C (insulin growth factor-1) and the thyroxine level in children with congenital hypothyroidism revealed during neonatal screening.
Methods And Results:
The somatomedin (SMA) activity was examined in 13 neonates aged 10-23 days with confirmed CH. Total thyroxine (T4) and thyroid stimulating hormone (TSH) were estimated using commercial RIA kits. SMA was assessed by Hall's biological method in Schimpff and Donnadie's modification. The control group comprised 10 healthy children aged 8-20 days and 10 children aged 29-94 days. SMA was examined before and then one month after the onset of L-thyroxine treatment. Before treatment the author found in 10-23 old infants with congenital hypothyroidism significantly lower SMA values than in controls (p < 0.01 at the 1% level of significance). During treatment the SMA values in both groups were equal.
Conclusions:
Early hormonal substitution therapy, i.e. as soon as possible after delivery, is essential in children with congenital hypothyroidism not only for normal growth of the CNS but also for normal continuous growth.


Related Concept Videos
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:25
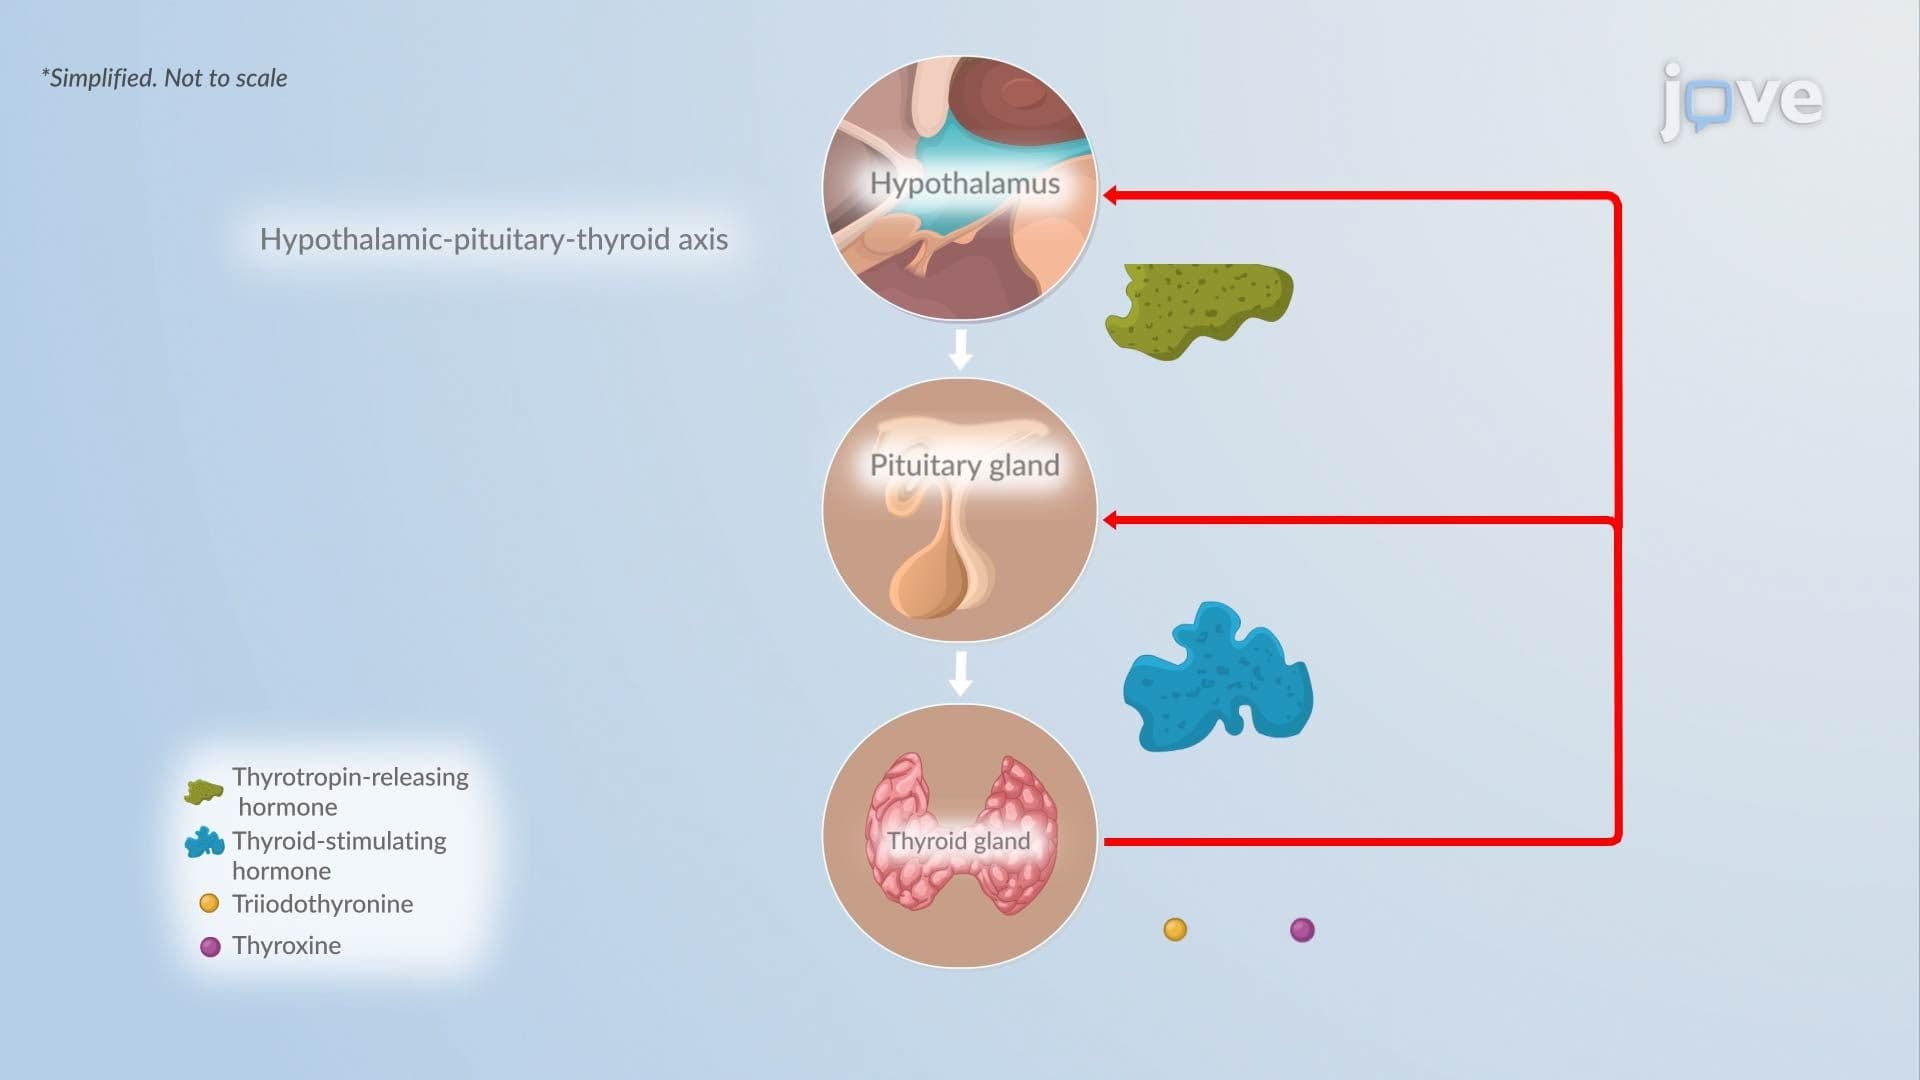
Hyperthyroidism I: Introduction
 01:24
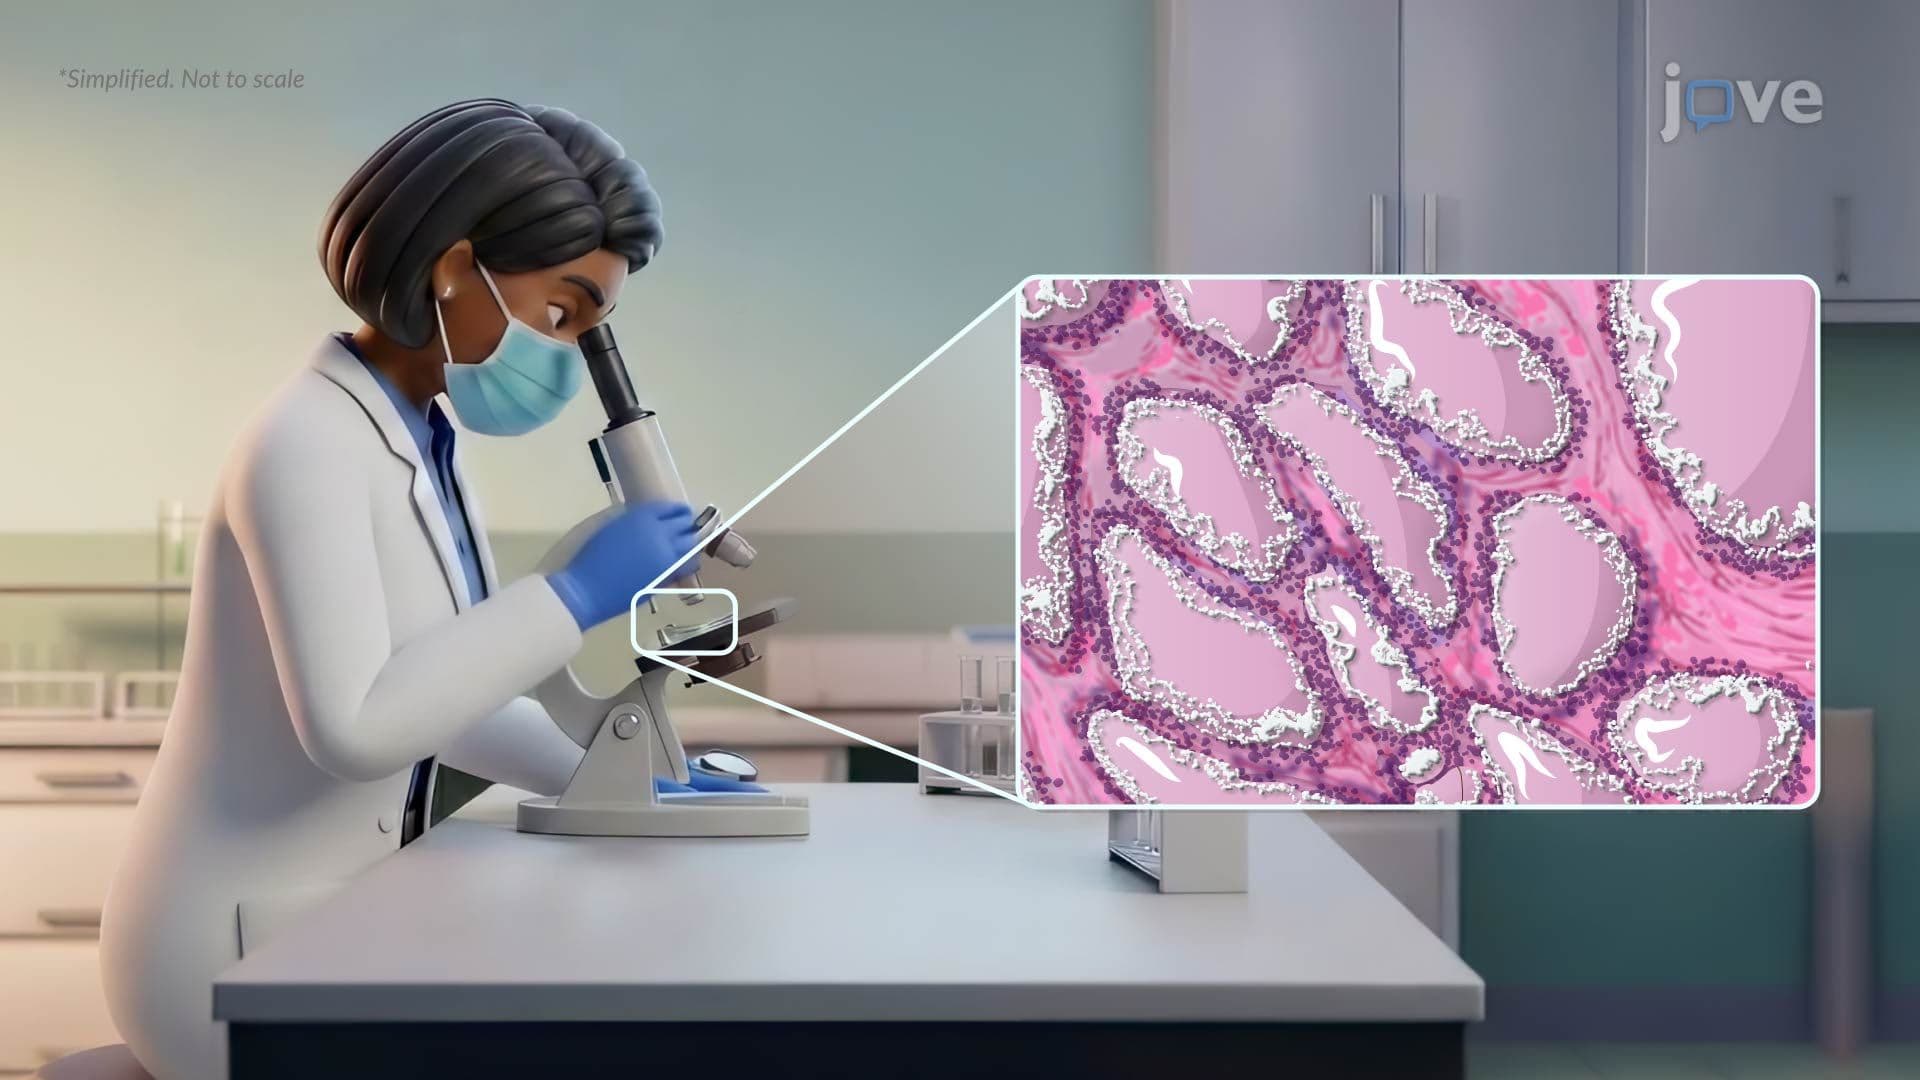
Graves Disease II: Pathophysiology
 01:27
Goiter
 01:23
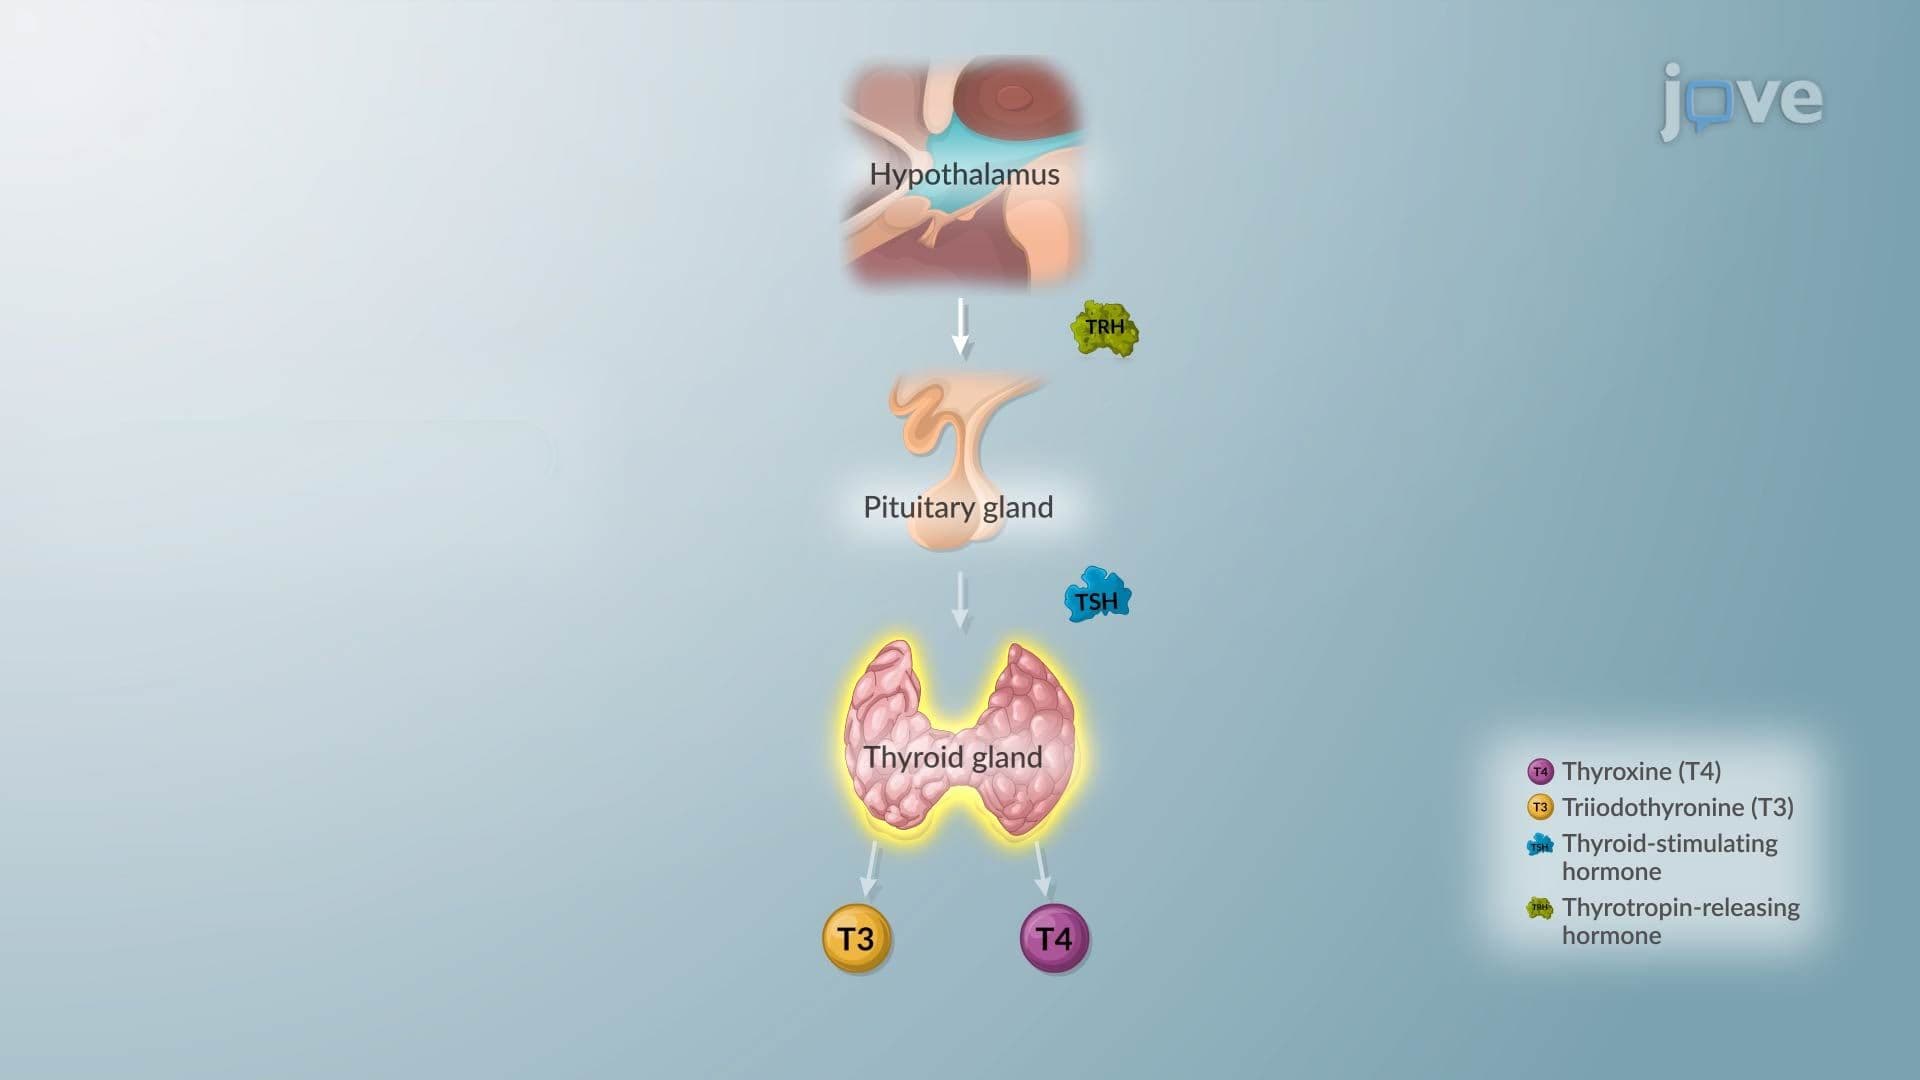
Hypothyroidism II: Pathophysiology