Related Experiment Video
Updated: Aug 17, 2026


A Semi-High-Throughput Adaptation of the NADH-Coupled ATPase Assay for Screening Small Molecule Inhibitors
Published on: August 17, 2019
Lipophilic beta-blockers inhibit rat skeletal muscle mitochondrial respiration
A W Dreisbach1, R L Greif, B J Lorenzo
1Department of Pharmacology and Medicine, Cornell University Medical College, New York, NY 10021.

Abstract:
Propranolol, metoprolol, acebutolol, nadolol and atenolol were incubated with isolated rat skeletal muscle mitochondria at 30 degrees C, and the rate of oxygen consumption was measured with an oxygen microelectrode. The potency of these drugs to inhibit state III respiration was correlated with lipid solubility as measured by the octanol/water partition coefficient. The most lipid-soluble beta-blocker, propranolol, had an ED50 of 0.6 mmol/l. The most water-soluble one, atenolol, showed no inhibition at concentrations up to 16 mmol/l. Inhibition of respiratory control ratio, state IV respiration and ADP/O ratio occurred at 2 mmol/l for propranolol, 16 mmol/l for metoprolol and was not consistently observed for the other beta-blockers at the concentrations tested. The inhibition of state III respiration of skeletal muscle mitochondria by lipid-soluble beta-blockers may be one of the causes of the fatigue observed in some patients receiving these drugs.


Related Concept Videos
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:17
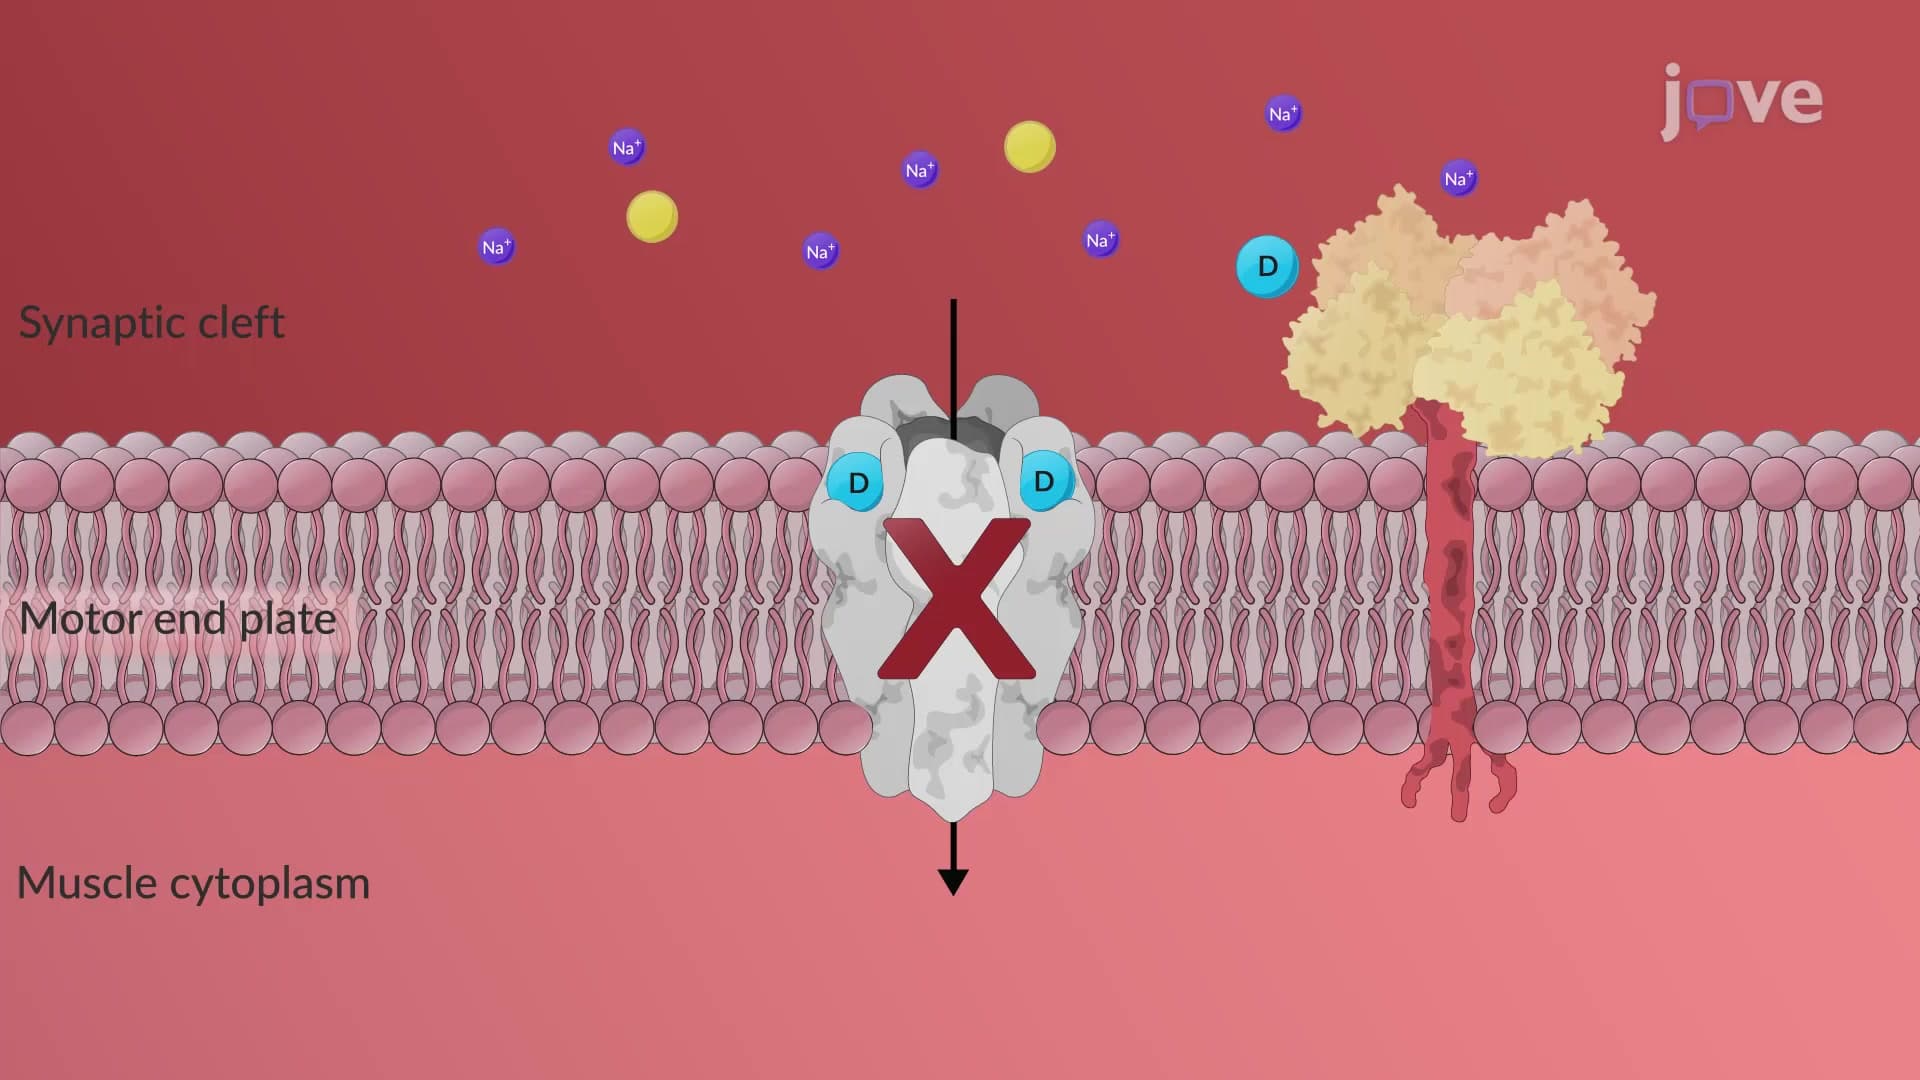
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:18
Antihypertensive Drugs: Action of Calcium Channel Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers