Related Experiment Video
Updated: Aug 16, 2026
Mouse Model of Surgically-induced Endometriosis by Auto-transplantation of Uterine Tissue
Published on: January 6, 2012
Endometriosis: the host response
1University of North Carolina at Chapel Hill 27599.

There is abundant evidence of altered immune function in endometriosis. The task that remains is to attempt a synthesis from the accumulated data, to try to make some sense of the observed phenomena and to fit them into a conceptual framework; this might permit the formulation and testing of hypotheses. Evidently, eutopic endometrium does not engender an immune response in normal subjects, otherwise the endometrium would be subject to autoimmune destruction. It has also been established that the overwhelming majority of women regurgitate menstrual debris into the peritoneal cavity. Why does this lead to endometriosis in some, but not in others? There are several possible explanations. The uterus might act as a privileged site, i.e. be exempt from immune effector mechanisms. This would certainly be conducive to the reproductive goal, the survival of the fetal allograft. Endometrium would then not enjoy the immunologic tolerance of most other tissues, and upon leaving the uterus and entering an immunocompetent environment would be subject to immune attack. In normal subjects, this could consist of elimination of menstrual debris without further sequelae. An altered response, characterized by the production of antibody that could mask receptors for cytotoxic or phagocytic effector cells, would permit persistence of ectopic endometrium. The alternative to this hypothesis is that the uterus is not a privileged site, and that the organism is normally tolerant to endometrial antigens. Menstrual debris would be eliminated intraperitoneally without loss of tolerance due to the presence of homeostatic mechanisms including suppressor T cells and suppressive cytokines. In endometriosis, this tolerance breaks down, as is the case in several autoimmune disorders, causing a chronic inflammatory response with the release of toxic factors and, eventually, peritoneal scarring. Finally, the role of cell adhesion molecules, including the integrins, is only just being explored. The behaviour of these molecules in ectopic endometrium differs from that in eutopic endometrium, and it remains to be seen whether regurgitated endometrial debris from normal subjects is different from that of endometriosis sufferers. It seems that this will be an area of intense investigation in the immediate future.
There is abundant evidence of altered immune function in endometriosis. The task that remains is to attempt a synthesis from the accumulated data, to try to make some sense of the observed phenomena and to fit them into a conceptual framework; this might permit the formulation and testing of hypotheses. Evidently, eutopic endometrium does not engender an immune response in normal subjects, otherwise the endometrium would be subject to autoimmune destruction. It has also been established that the overwhelming majority of women regurgitate menstrual debris into the peritoneal cavity. Why does this lead to endometriosis in some, but not in others? There are several possible explanations. The uterus might act as a privileged site, i.e. be exempt from immune effector mechanisms. This would certainly be conducive to the reproductive goal, the survival of the fetal allograft. Endometrium would then not enjoy the immunologic tolerance of most other tissues, and upon leaving the uterus and entering an immunocompetent environment would be subject to immune attack. In normal subjects, this could consist of elimination of menstrual debris without further sequelae. An altered response, characterized by the production of antibody that could mask receptors for cytotoxic or phagocytic effector cells, would permit persistence of ectopic endometrium. The alternative to this hypothesis is that the uterus is not a privileged site, and that the organism is normally tolerant to endometrial antigens. Menstrual debris would be eliminated intraperitoneally without loss of tolerance due to the presence of homeostatic mechanisms including suppressor T cells and suppressive cytokines. In endometriosis, this tolerance breaks down, as is the case in several autoimmune disorders, causing a chronic inflammatory response with the release of toxic factors and, eventually, peritoneal scarring. Finally, the role of cell adhesion molecules, including the integrins, is only just being explored. The behaviour of these molecules in ectopic endometrium differs from that in eutopic endometrium, and it remains to be seen whether regurgitated endometrial debris from normal subjects is different from that of endometriosis sufferers. It seems that this will be an area of intense investigation in the immediate future.
More Related Videos
 07:20
Intraoperative Detection of Subtle Endometriosis: A Novel Paradigm for Detection and Treatment of Pelvic Pain Associated with the Loss of Peritoneal Integrity
Published on: December 21, 2012
 07:12
A Syngeneic Murine Model of Endometriosis using Naturally Cycling Mice
Published on: November 24, 2020
Related Concept Videos
 02:07
Oogenesis
 01:22
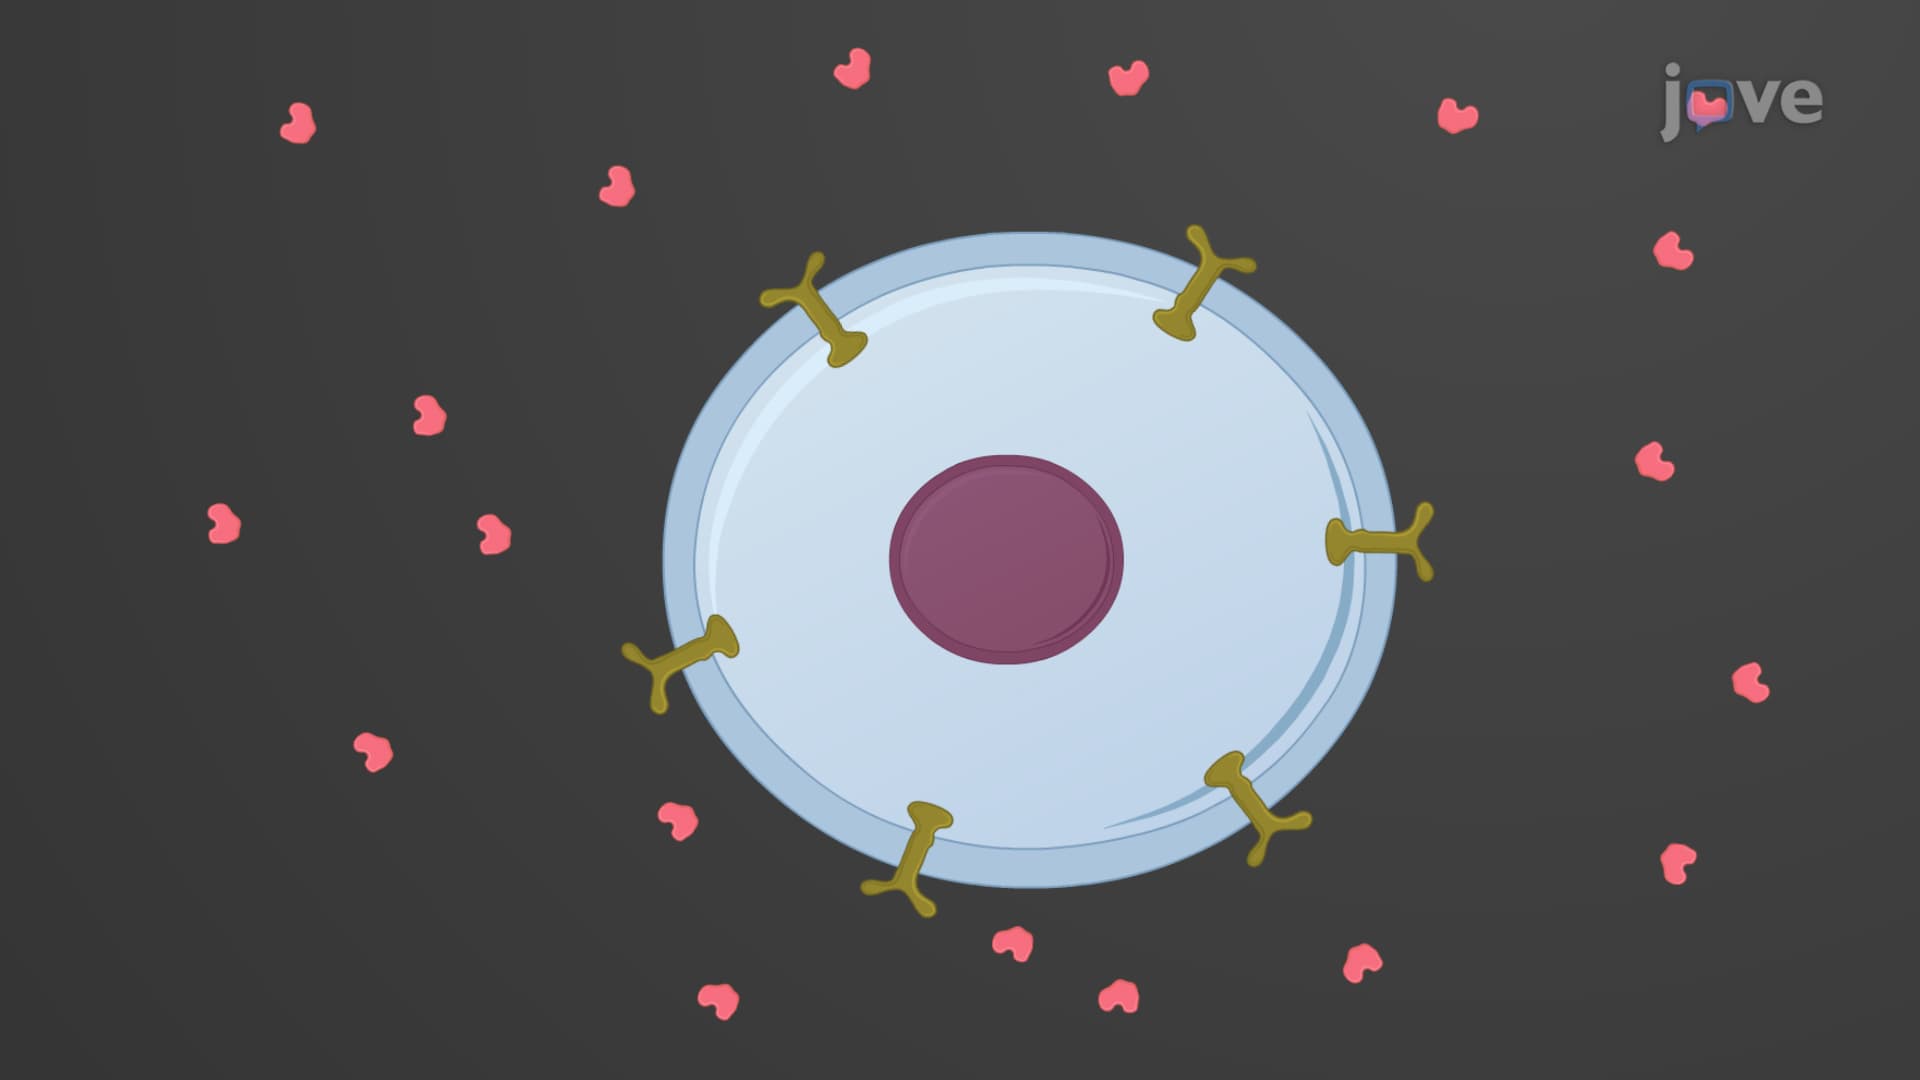
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:27
Ovarian Cycle
 01:28
Amebiasis
 01:18
Trichomoniasis