Related Experiment Video
Updated: Aug 13, 2026

Anticancer Metal Complexes: Synthesis and Cytotoxicity Evaluation by the MTT Assay
Published on: November 10, 2013
Platinum complexes in cancer medicine: pharmacokinetics and pharmacodynamics in relation to toxicity and therapeutic
H Calvert1, I Judson, W J van der Vijgh
1Cancer Research Unit, University of Newcastle upon Tyne, Medical School.

Abstract:
The study of the pharmacokinetics and pharmacodynamics of platinum based anti-cancer drugs has done much to direct their development, at both preclinical and clinical levels. The clinical development of cisplatin depended on an understanding of its mechanism of action. The amelioration of the renal toxicity of cisplatin with sodium chloride infusion and forced diuresis is thought to rely on a common ion effect to suppress the formation of aquated species in the renal tubule. Studies of the modulation of cisplatin toxicity with other agents have followed, although none has yet achieved widespread acceptance. Following the demonstration of the important clinical role for cisplatin, studies of the relationship between toxicity and the reactivity of the leaving groups led to the development of the less toxic but equally effective analogue, carboplatin. The clinical development of carboplatin has in turn been strongly influenced by the studies of its pharmacokinetics, with pharmacokinetically guided dosing now being standard in many cancer centres and also being widely used in current clinical trials. Pharmacokinetic studies in animals have demonstrated that it is possible to make analogues that have good oral bioavailability. Apart from the convenience of oral administration, there is also the suggestion that these molecules may possess activity against certain cisplatin resistant cell lines. For the future, the development of sensitive methodologies whereby the exact types of platinum-DNA adducts formed can be characterized may allow the reason for the remarkable anti-tumour activity of these complexes to be elucidated and further, more selective compounds to be designed. The history of the development of platinum compounds emphasizes the importance of performing intensive pharmacokinetic, pharmacodynamic and mechanistic studies in concert with the clinical development of any class of agents.


Related Concept Videos
 02:50
Combination Therapies and Personalized Medicine
The combination of the drug acetazolamide and sulforaphane is a good example of combination therapy to treat cancer. The cells in the interior of a large tumor often die due to the hypoxic and...
 01:14
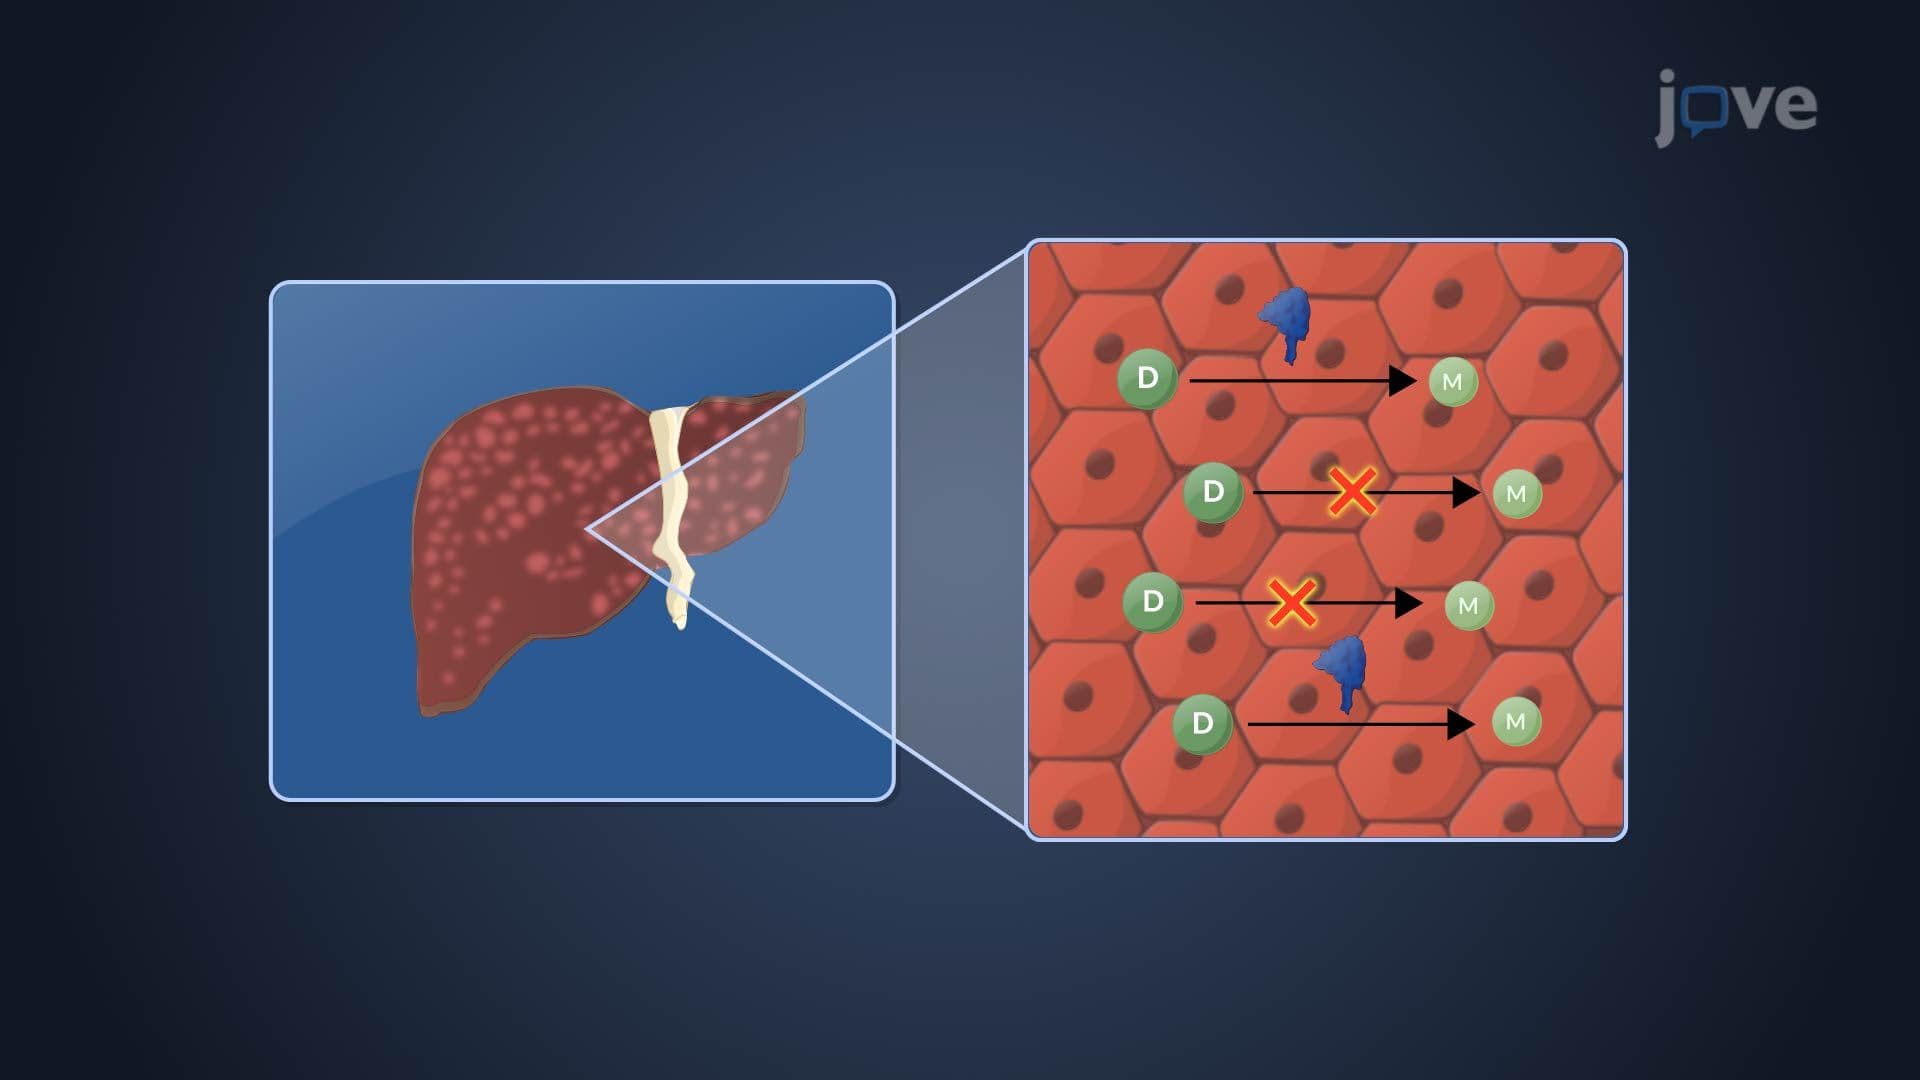
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase
 01:24
Drug Toxicity: Dose-Dependent Reactions
 01:30
Drug toxicity: Drug–Drug Interaction
 01:21
Toxicokinetics: Overview