Related Experiment Video
Updated: Sep 29, 2026
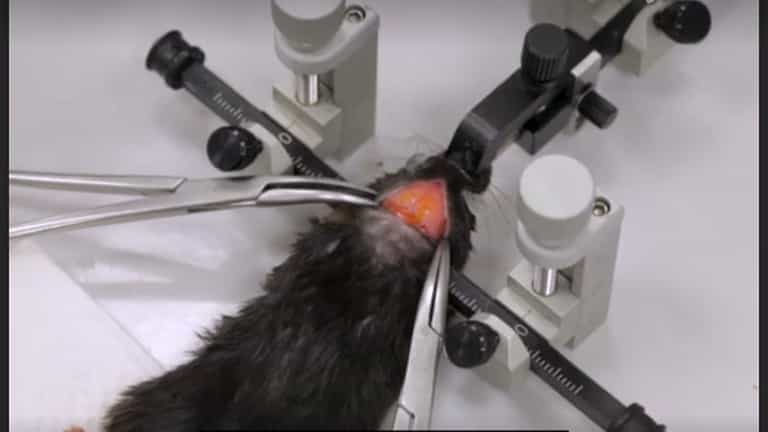

Studying the Hypothalamic Insulin Signal to Peripheral Glucose Intolerance with a Continuous Drug Infusion System into the Mouse Brain
Published on: January 4, 2018
[Hyperinsulinemia in obesity and diseases of internal medicine]

Abstract:
We analysed fasting serum insulin levels and its correlation with common internal medical diseases in 91 cases with obesity (BMI > 24) and that in 76 nonobese cases. The mean fasting serum insulin level in obese group was higher significantly than that in nonobese group (P < 0.001). The incidences of hypertension, coronary heart disease, cerebrovascular disease, non-insulin-dependent diabetes mellitus, hypercholesterolemia, hypertriglyceridemia, combined hyperlipidemia and serum low level of HDL-C in obese group were also higher significantly than that in nonobese group (P < 0.05 and < 0.01 respectively). The main cause of many medical diseases coexisted with obesity is hyperinsulinemia. We think that the first choice of therapy to this kind of diseases should be to reduce the body weight and to decrease the insulin resistance.

Related Concept Videos
 01:24
Obesity
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:26
Type I Diabetes II: Pathophysiology
 01:19
Type I Diabetes III: Clinical Manifestations
 01:24
Type II Diabetes II: Pathophysiology