
Prediction of isolated first diagonal branch occlusion by 12-lead electrocardiography: ST segment shift in leads I

Insights
Electrocardiogram (ECG) abnormalities in leads I and aVL, with a normal V1 lead, can help differentiate first diagonal branch occlusion from left anterior descending coronary artery occlusion.
Area of Science:
- Cardiology
- Diagnostic Electrocardiography
Background:
- ECG findings for first diagonal branch obstruction are not well-defined.
- Comparison with left anterior descending coronary artery obstruction is lacking.
Purpose of the Study:
- To identify specific ECG features distinguishing first diagonal branch occlusion from left anterior descending coronary artery occlusion.
- To enhance diagnostic accuracy for coronary artery occlusions.
Main Methods:
- Compared ECG findings in 34 patients with isolated diagonal branch occlusion (group 9) against 20 patients with left anterior descending occlusion at site 6 (group 6) and 20 at site 7 (group 7).
- Utilized American Heart Association classification for occlusion sites.
- Statistical analysis with >80% power to detect a 50% difference.
Main Results:
- Group 9 showed ST elevation in leads I and aVL (100%), abnormal Q waves, and inverted T waves more frequently than groups 6 and 7.
- Group 9 had significantly less ST elevation, abnormal Q waves, and inverted T waves in lead V1 compared to groups 6 and 7.
- Multivariate analysis identified leads I, aVL, and V1 abnormalities as key discriminators.
Conclusions:
- Isolated diagonal branch occlusion causes distinct ECG changes in leads I and aVL.
- Precordial lead changes are less common in diagonal branch occlusion compared to LAD occlusion.
- Leads I and aVL reflect the myocardial territory supplied by the diagonal branch.
Objectives:
This study was performed to determine electrocardiographic (ECG) features that could distinguish first diagonal branch occlusion from left anterior descending coronary artery occlusion.
Background:
The ECG findings associated with first diagonal branch obstruction have not previously been compared with those of left anterior descending coronary artery obstruction.
Methods:
The ECG findings in 34 patients with isolated diagonal branch occlusion (group 9) were compared with those in 20 patients with occlusion at site 6 (group 6) and 20 with occlusion at site 7 (group 7), according to American Heart Association classification. This study had a power > 80% to detect a 50% difference between groups at a probability value of 0.05.
Results:
ST segment elevation was observed in leads I and aVL for all group 9 patients, in 80% (p < 0.05) of group 6 patients for lead I and 90% for lead aVL and in 50% (p < 0.01) of group 7 patients for lead I and 55% (p < 0.01) for lead aVL. Similarly, there was a higher incidence of abnormal Q waves and inverted T waves in leads I and aVL in group 9 than in groups 6 and 7. In contrast, group 9 showed a significantly lower incidence of ST segment elevation (3.4%), abnormal Q waves (3.0%) and inverted T waves (0%) in lead V1 than group 6 (80%, 40% and 90%, respectively) and group 7 (75%, 60% and 70%, respectively) (p < 0.01 for each). Multivariate analysis revealed that abnormalities in leads I and aVL, combined with a normal lead V1 (and V6), provided good criteria for distinguishing isolated diagonal branch occlusion from left anterior descending coronary artery occlusion.
Conclusions:
Isolated diagonal branch occlusion more frequently caused ECG abnormalities in leads I and aVL and less frequently caused changes in the precordial leads compared with left anterior descending coronary artery obstruction, indicating that leads I and aVL represent myocardium perfused by the diagonal branch.
More Related Videos
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
 10:17
Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Related Concept Videos
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:30
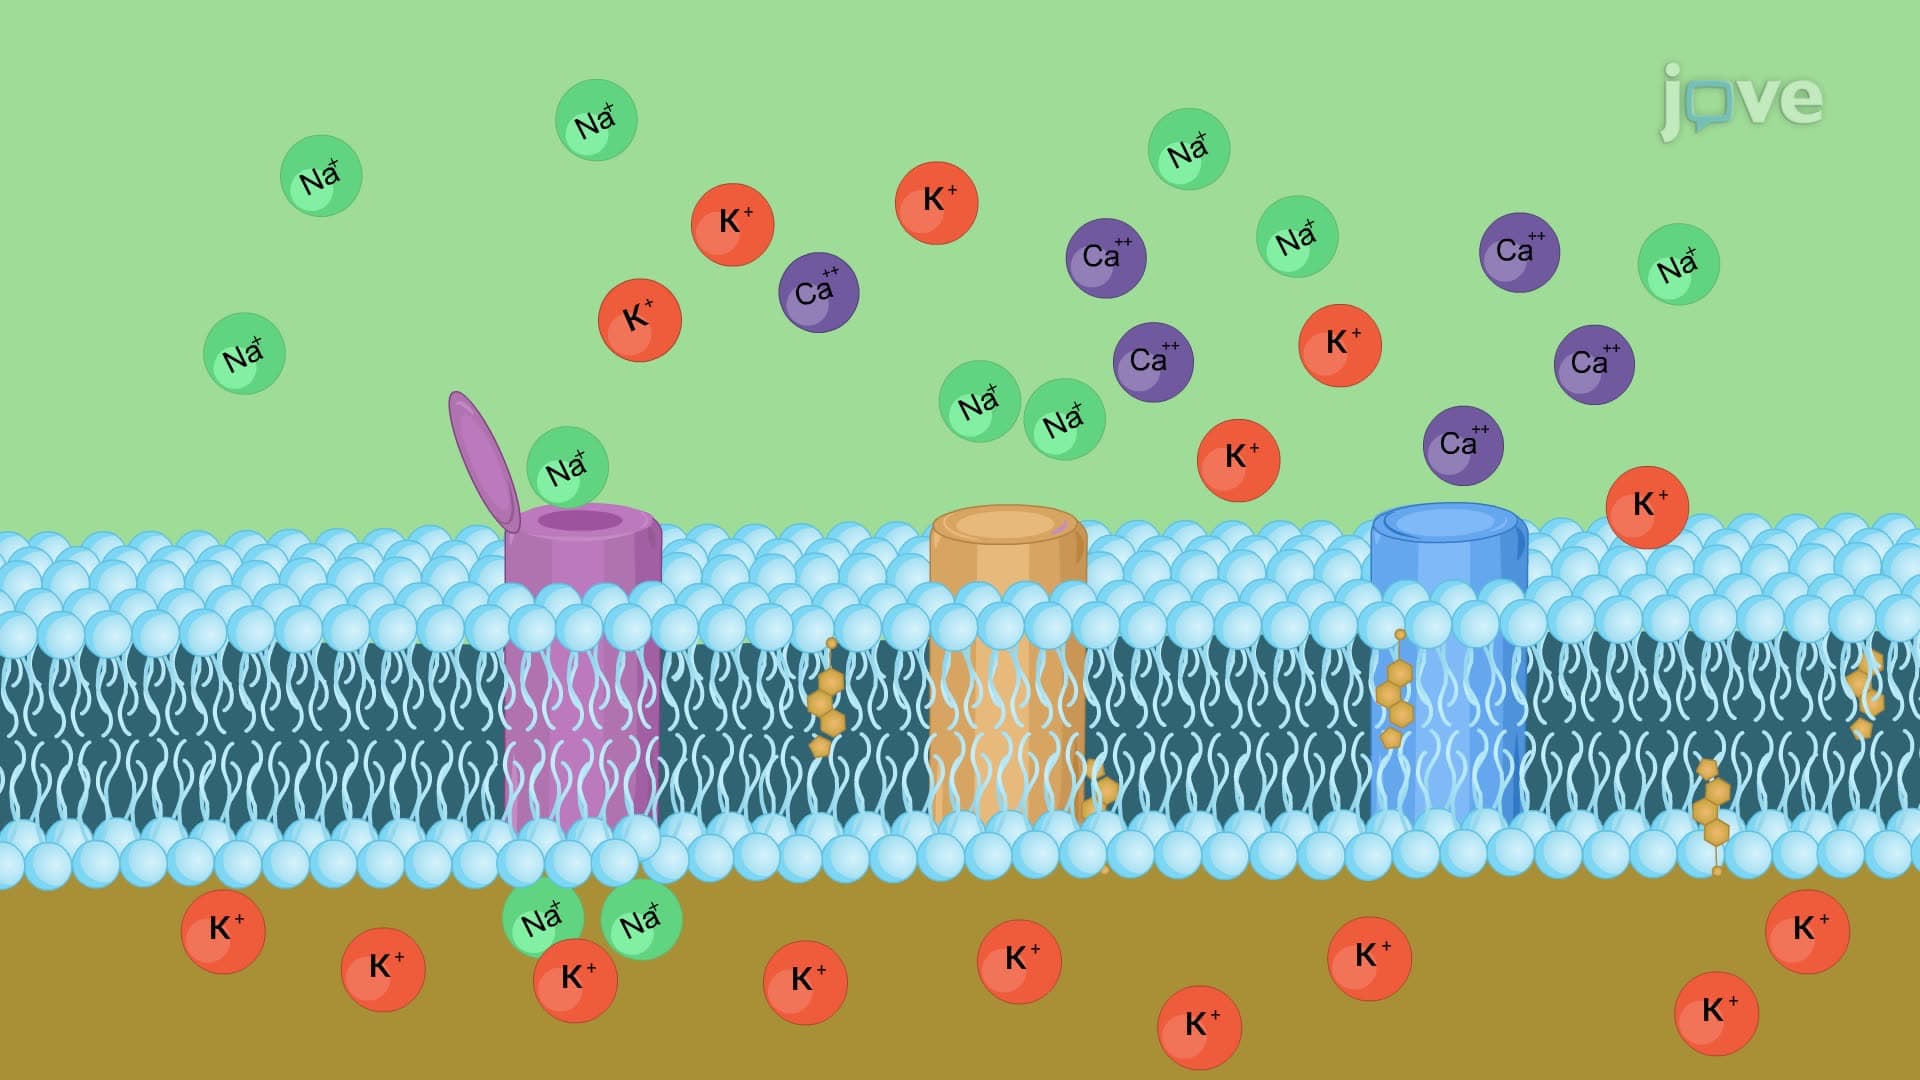
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:28
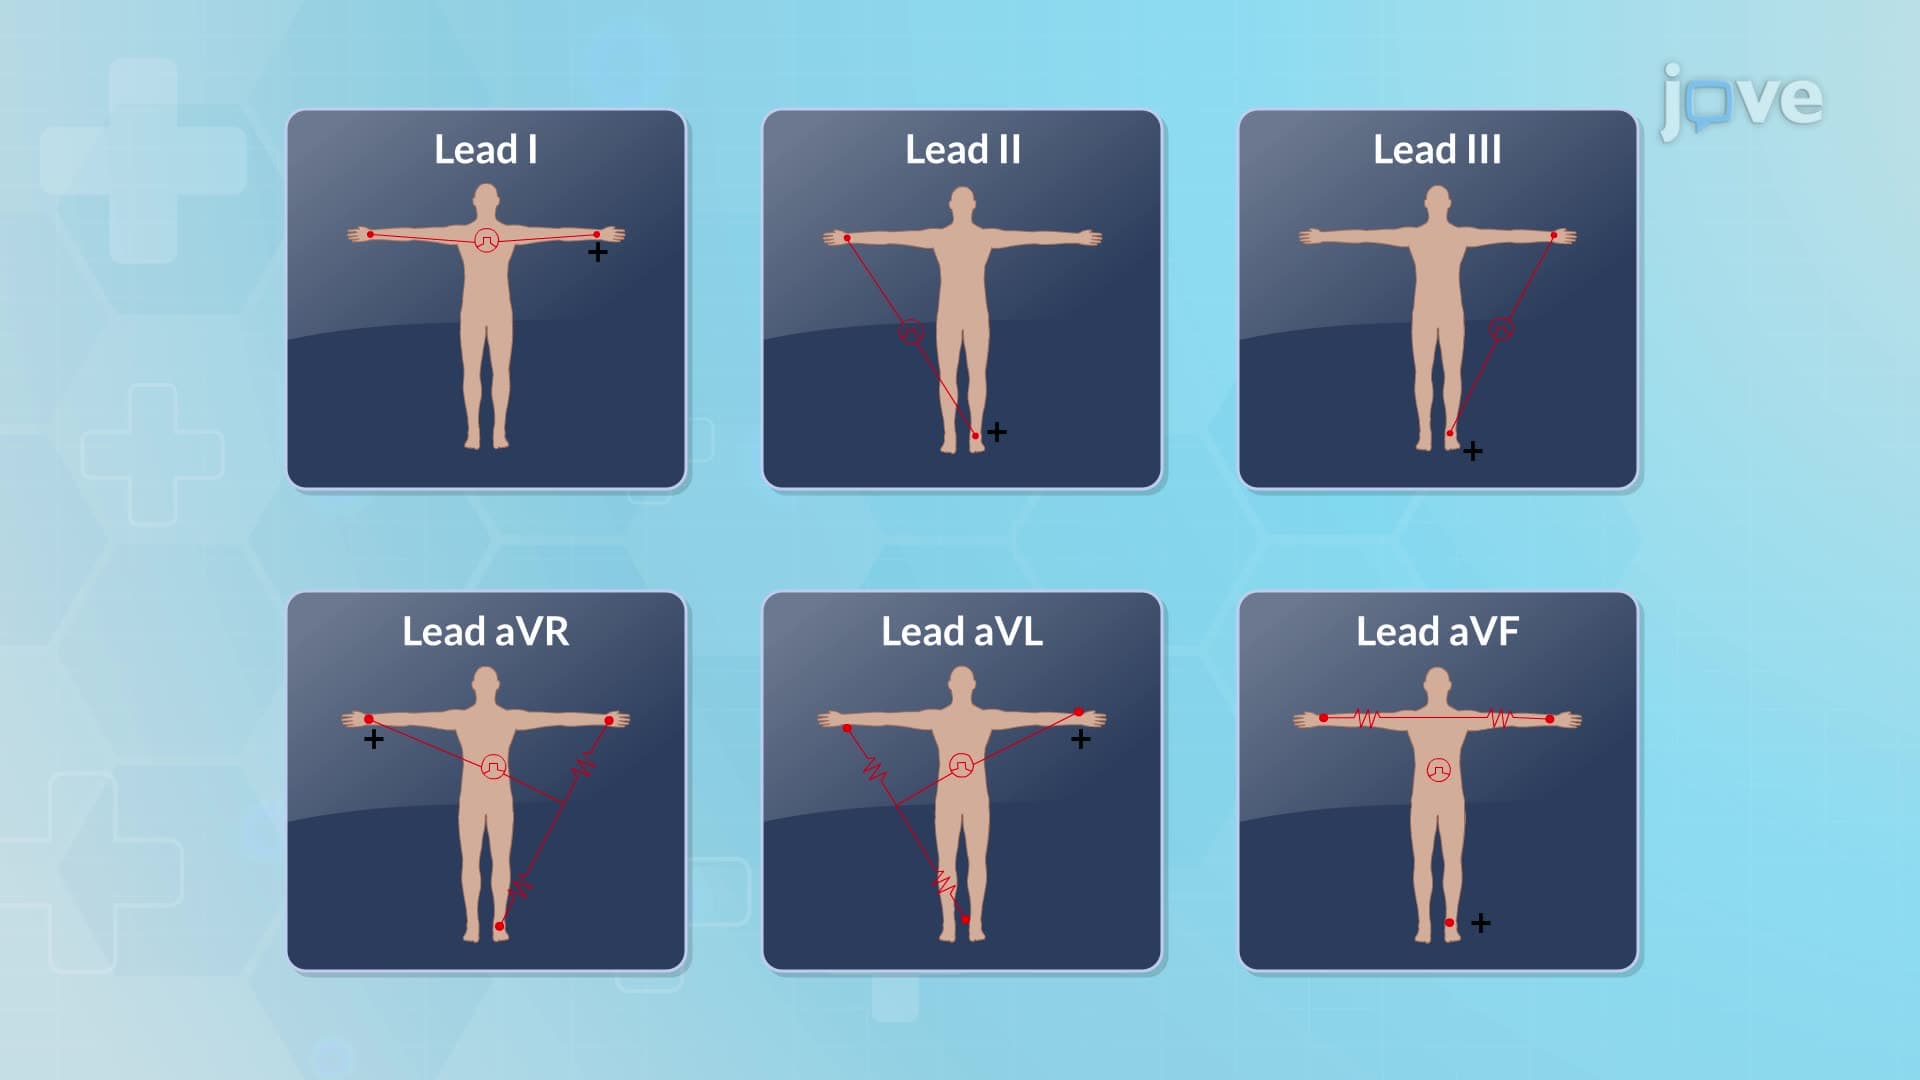
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias