[Loop diuretics. Rational pharmacotherapy]
Related Experiment Video
Updated: Oct 14, 2026
Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
1Rigshospitalet, anaestesiafdelingen, København.

Unlabelled:
The pharmacodynamics and -kinetics as well as rational pharmacotherapy of furosemide and bumetanide is reviewed. In renal insufficiency, a reduced response to diuretics is due to altered pharmacokinetics. The optimum dose can be determined within three to four hours by titration and the effect is measured by the amount of excreted sodium. In nephrotic syndrome, both pharmaco-kinetics and--dynamics are altered. The optimum dose is established as above. Starting and ceiling doses are given in tables for both drugs in renal insufficiency and nephrotic syndrome. In congestive heart failure, the difference is greater between oral and intravenous doses than apparent from the bioavailability of the drugs. If potent diuretics are without effect, the heart failure must be treated more vigorously or a combination with thiazides tried out. Potent diuretics are seldom used in the treatment of liver cirrhosis, but, if used, large doses are necessary. Non-steroidal antiinflammatory drugs are usually considered contra-indicated in patients with severe renal insufficiency, since the pharmacodynamics of the diuretics are altered.
Conclusion:
The general strategy when using potent diuretics is titration to an effective dose and then using this dose as frequently as needed in order to obtain the desired response.
Related Concept Videos
 01:16
Antihypertensive Drugs: Action of Diuretics
 01:15
Antihypertensive Drugs: Thiazide-Class Diuretics
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:22
Heart Failure Drugs: Diuretics
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:25
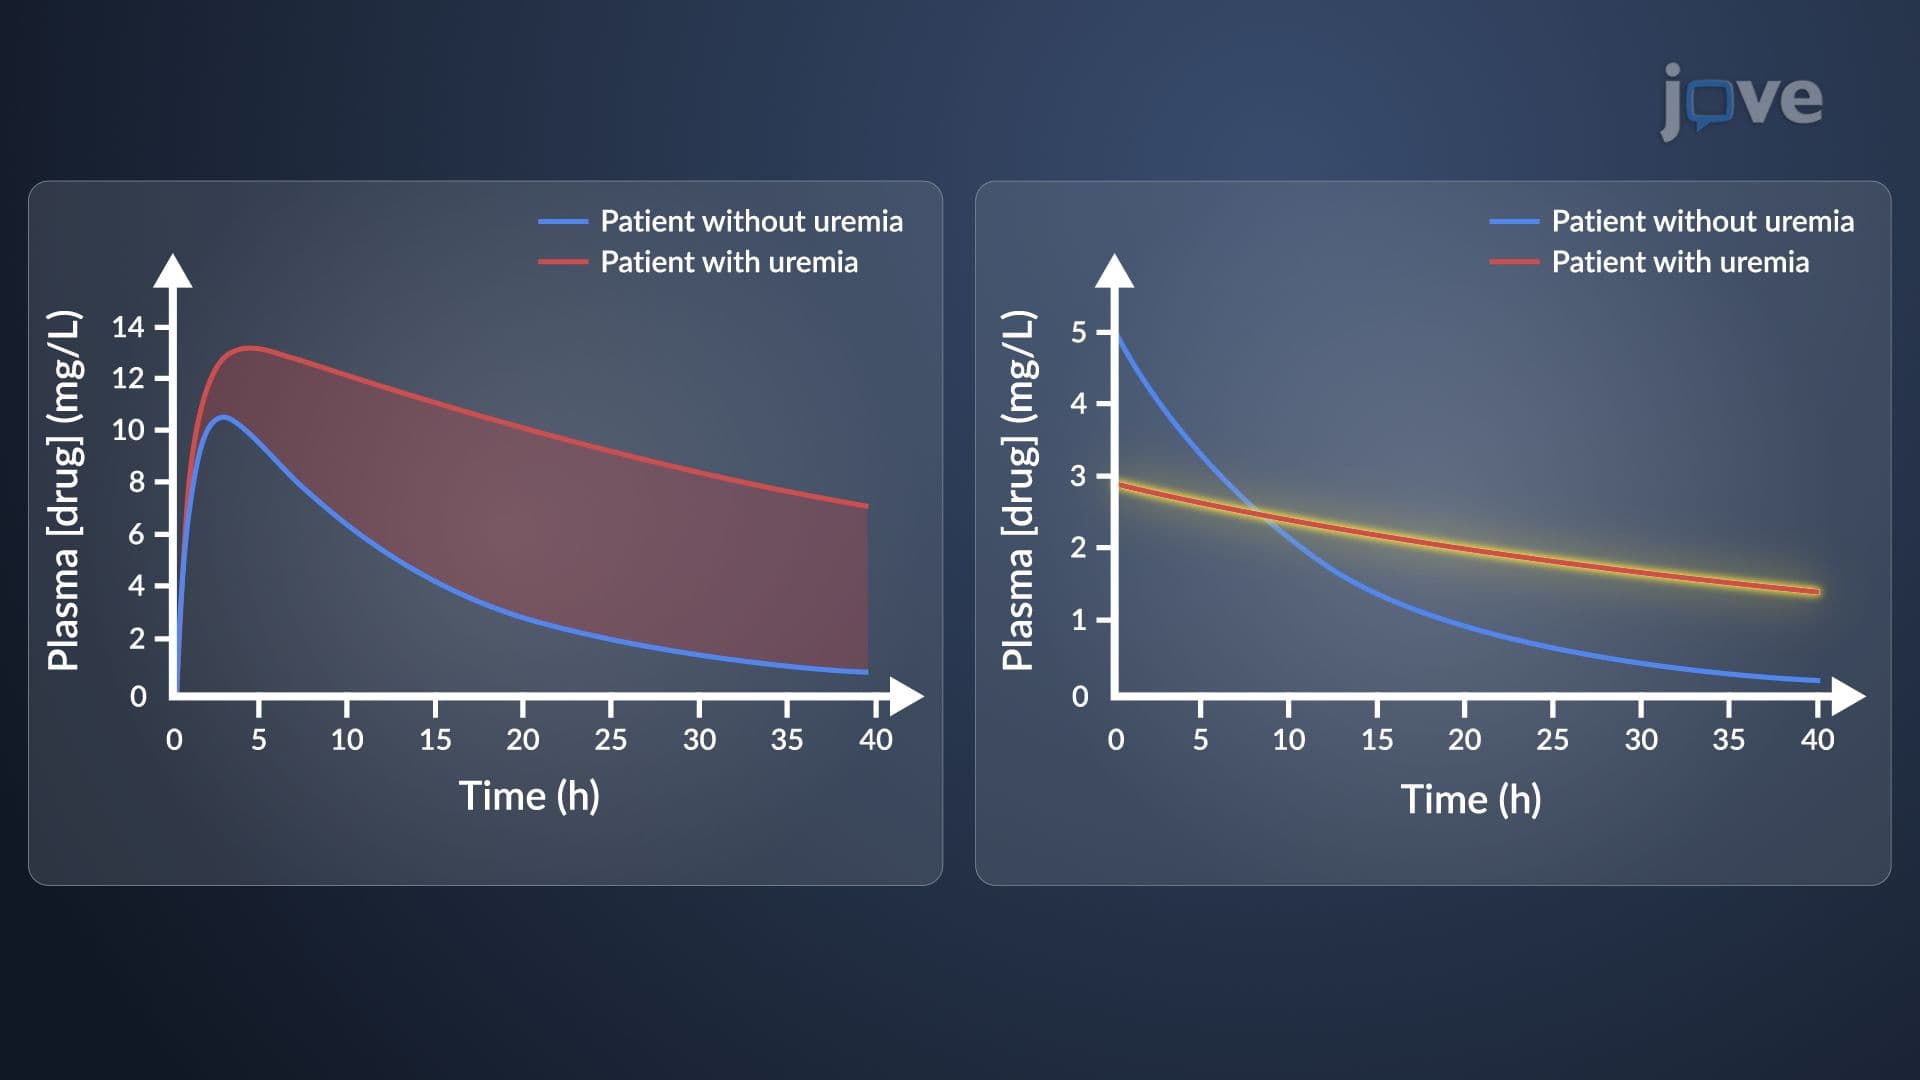
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant