Acquired antithrombin III deficiency: replacement with antithrombin III concentrates in a patient with protein S

J E Humphries1

  • 1Department of Internal Medicine, University of Virginia Health Sciences Center, Charlottesville 22908.

Acta Haematologica
|January 1, 1993
PubMed

A 33-year-old man with inherited protein S deficiency and a 20-year history of deep and superficial venous thrombosis was admitted for treatment of extensive, acute, superficial venous thrombosis of the left lower extremity. Clinical response to intravenous heparin was very slow. After discovery of acquired antithrombin III deficiency superimposed on the protein S deficiency, he was given antithrombin III concentrates with the intravenous heparin. His response to therapy was accelerated. The development of acquired antithrombin III deficiency in patients with venous thrombosis may slow the response to standard anticoagulant therapy. Therapy of the thrombosis may be improved with administration of antithrombin III concentrates.


Related Concept Videos

Anticoagulant Drugs: Low-Molecular-Weight Heparins01:30

Anticoagulant Drugs: Low-Molecular-Weight Heparins

Hemostasis is a crucial process that prevents excessive blood loss from damaged blood vessels. It involves various mechanisms such as vasoconstriction, platelet adhesion and activation, and fibrin formation. The importance of each mechanism depends on the type of vessel injury. In contrast, thrombosis is the abnormal formation of a blood clot within the blood vessels, leading to potential complications if the clot obstructs blood flow. Thrombosis can be caused by increased coagulability of the...
Myocarditis III: Medical Management01:14

Myocarditis III: Medical Management

Myocarditis: Comprehensive Medical ManagementMyocarditis, the heart muscle inflammation, requires a comprehensive medical management strategy that addresses the underlying cause, provides supportive care, manages symptoms, and reduces cardiac workload.Infections and Autoimmune CausesAdminister appropriate antimicrobial therapy when an infectious agent causes myocarditis. For instance, penicillin treats infections caused by Group A Streptococcus. In cases where autoimmune processes are...
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies01:20

Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies

The key difference between Superficial Vein Thrombosis (SVT) and Deep Vein Thrombosis (DVT) lies in their location and severity.Clinical ManifestationsSVT typically presents with localized pain, tenderness, and redness along the course of a superficial vein, often accompanied by a palpable, cord-like structure under the skin. This condition is usually less dangerous than DVT but can be uncomfortable and may lead to complications such as cellulitis or, rarely, a clot extension into the deep...
Venous Thrombosis III: Interprofessional Care01:29

Venous Thrombosis III: Interprofessional Care

Venous thrombosis requires effective prevention and treatment strategies to improve patient outcomes and reduce potential complications.Prevention StrategiesHealthcare providers must prioritize preventing venous thromboembolism (VTE) for all adult patients upon admission. Interventions depend on bleeding and thrombosis risk, medical history, current medications, diagnoses, planned procedures, and patient preferences. Patients on bed rest should change positions every two hours and, if not...
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care01:29

Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
Diagnosing Pulmonary EmbolismDiagnosing pulmonary embolism (PE) involves clinical assessment and advanced imaging tests. The preferred diagnostic tool is the spiral (helical) CT scan or CT angiography (CTA), which uses intravenous contrast media to visualize the pulmonary vasculature and identify emboli.A ventilation-perfusion (V/Q) scan is an alternative for patients unable to receive contrast media. This scan includes both perfusion and ventilation scanning. Perfusion scanning involves...
Hypersensitivity Reactions: Immune-Complex Reactions01:19

Hypersensitivity Reactions: Immune-Complex Reactions

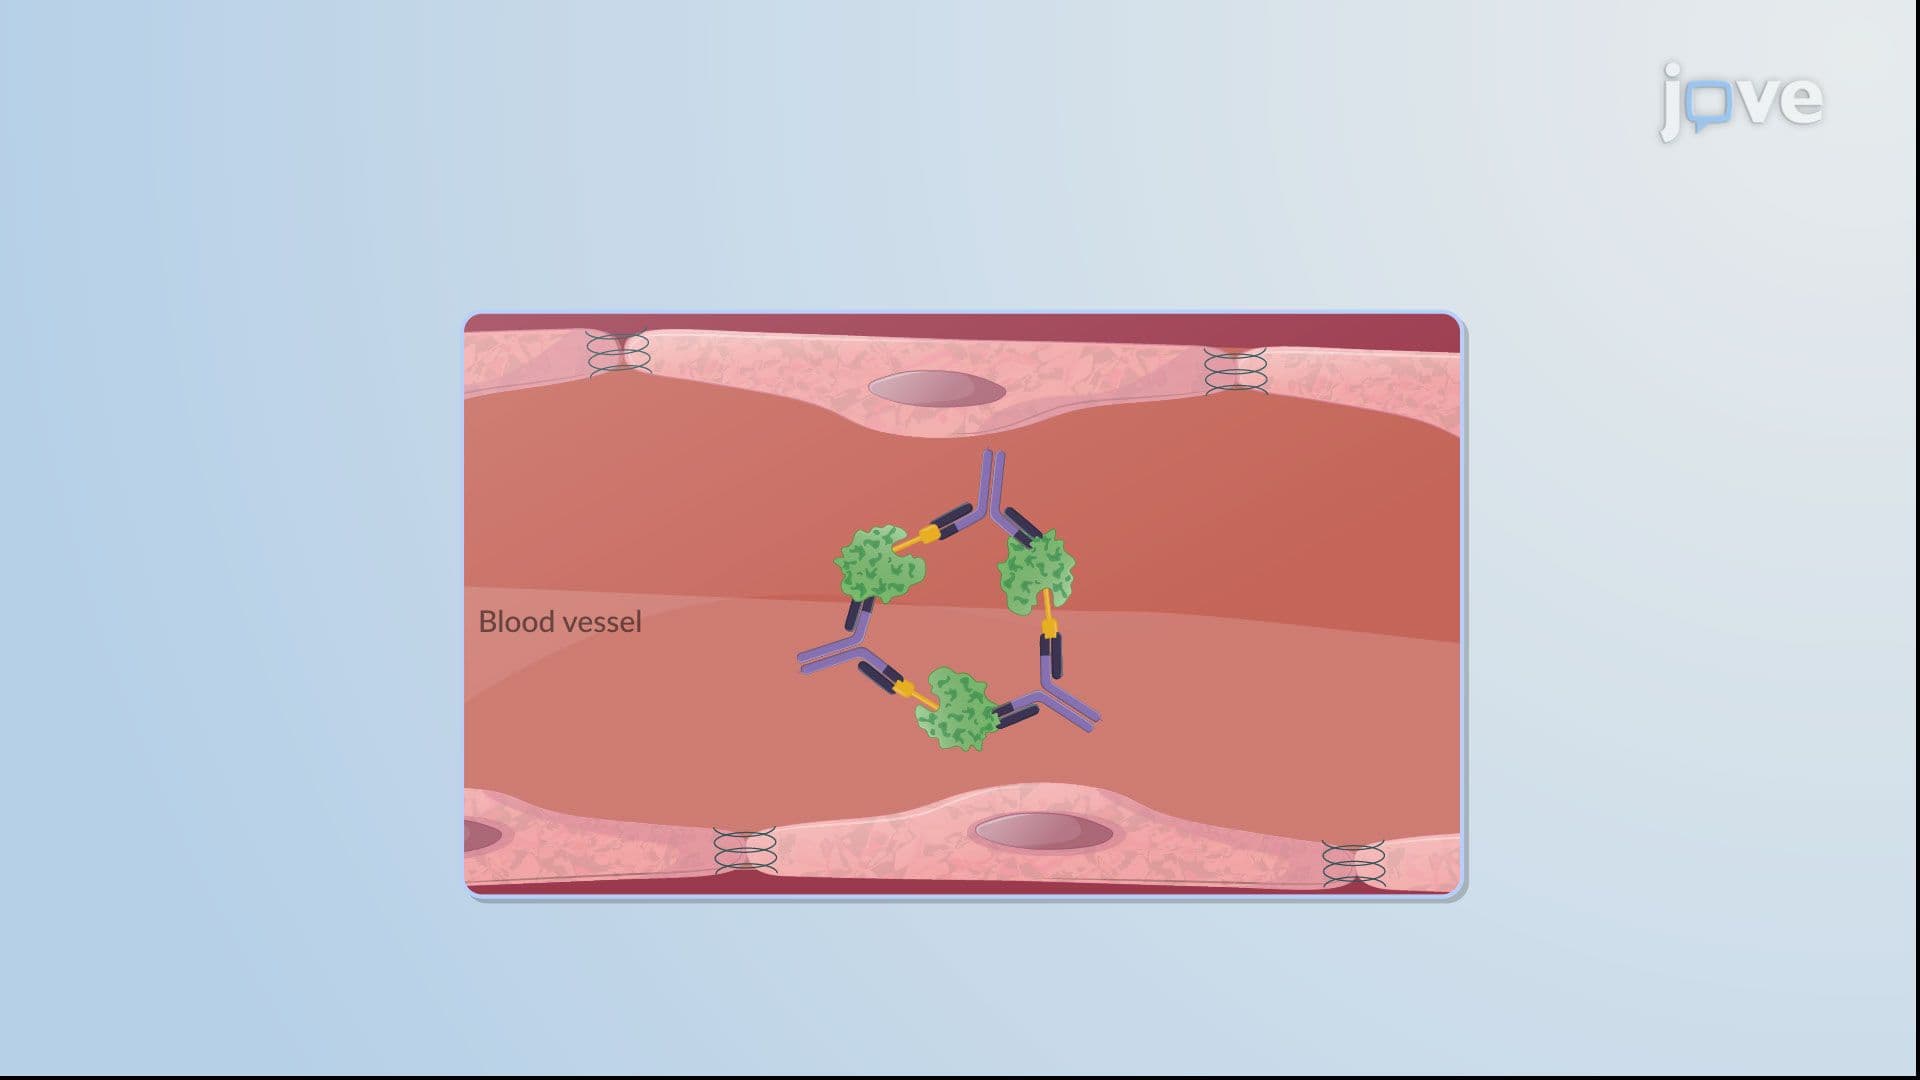
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum sickness, a systemic...
