Related Experiment Video
Updated: Aug 9, 2026


Endothelialized Microfluidics for Studying Microvascular Interactions in Hematologic Diseases
Published on: June 22, 2012
Sickle cell disease pathophysiology
C T Noguchi1, A N Schechter, G P Rodgers
1Department of Health and Human Services, National Institutes of Health, Bethesda, Maryland 20892.

The primary pathophysiological event in the erythrocytes of individuals with the various sickle syndromes is the intracellular aggregation or polymerization of sickle haemoglobin (HbS). The extent of polymerization is determined by the intracellular haemoglobin composition (% HbS and % HbS A, A2 and F), concentration (MCHC and % of dense cells) and oxygen saturation, as well as minor factors such as intracellular pH and DPG concentration. Intracellular HbS polymerization leads to a marked decrease in the flexibility or rheological properties of the sickle erythrocytes and obstruction in various microcirculatory beds, as well as chronic anaemia. Other abnormalities in the properties of the sickle erythrocytes, including membrane abnormalities, changes in ion fluxes and volume and endothelial adhesion, result from acute and chronic oxygen-linked polymerization events and may, in turn, modify polymerization. However, within a good approximation, many aspects of sickle cell disease pathophysiology--for example variations in anaemia among the different sickle syndromes--can be explained in terms of differences in polymerization tendency. Thus, the effects of alpha-thalassaemia can be explained with reference to changes in MCHC and syndromes with high HbF are understandable in terms of the sparing effect of HbF on polymerization. Recent therapeutic approaches to sickle cell disease focus on attempts to reduce intracellular HbS polymerization by altering the haemoglobin molecules, erythrocyte properties, or the distribution of intracellular haemoglobin species. The last, through pharmacological elevation of HbF, has become the central focus of much laboratory and clinical research in recent years. Agents such as hydroxyurea (with or without recombinant erythropoietin) and butyrate compounds elevate HbF (and reduce HbS) in a majority of sickle erythrocytes, thus decreasing intracellular polymerization. Current prospective protocols are designed to see if these changes cause clinical improvement at acceptable doses. Other treatment strategies, including bone marrow transplantation and possible gene replacement therapies, are also under active clinical or laboratory investigation.
The primary pathophysiological event in the erythrocytes of individuals with the various sickle syndromes is the intracellular aggregation or polymerization of sickle haemoglobin (HbS). The extent of polymerization is determined by the intracellular haemoglobin composition (% HbS and % HbS A, A2 and F), concentration (MCHC and % of dense cells) and oxygen saturation, as well as minor factors such as intracellular pH and DPG concentration. Intracellular HbS polymerization leads to a marked decrease in the flexibility or rheological properties of the sickle erythrocytes and obstruction in various microcirculatory beds, as well as chronic anaemia. Other abnormalities in the properties of the sickle erythrocytes, including membrane abnormalities, changes in ion fluxes and volume and endothelial adhesion, result from acute and chronic oxygen-linked polymerization events and may, in turn, modify polymerization. However, within a good approximation, many aspects of sickle cell disease pathophysiology--for example variations in anaemia among the different sickle syndromes--can be explained in terms of differences in polymerization tendency. Thus, the effects of alpha-thalassaemia can be explained with reference to changes in MCHC and syndromes with high HbF are understandable in terms of the sparing effect of HbF on polymerization. Recent therapeutic approaches to sickle cell disease focus on attempts to reduce intracellular HbS polymerization by altering the haemoglobin molecules, erythrocyte properties, or the distribution of intracellular haemoglobin species. The last, through pharmacological elevation of HbF, has become the central focus of much laboratory and clinical research in recent years. Agents such as hydroxyurea (with or without recombinant erythropoietin) and butyrate compounds elevate HbF (and reduce HbS) in a majority of sickle erythrocytes, thus decreasing intracellular polymerization. Current prospective protocols are designed to see if these changes cause clinical improvement at acceptable doses. Other treatment strategies, including bone marrow transplantation and possible gene replacement therapies, are also under active clinical or laboratory investigation.
More Related Videos


Related Concept Videos
 02:15
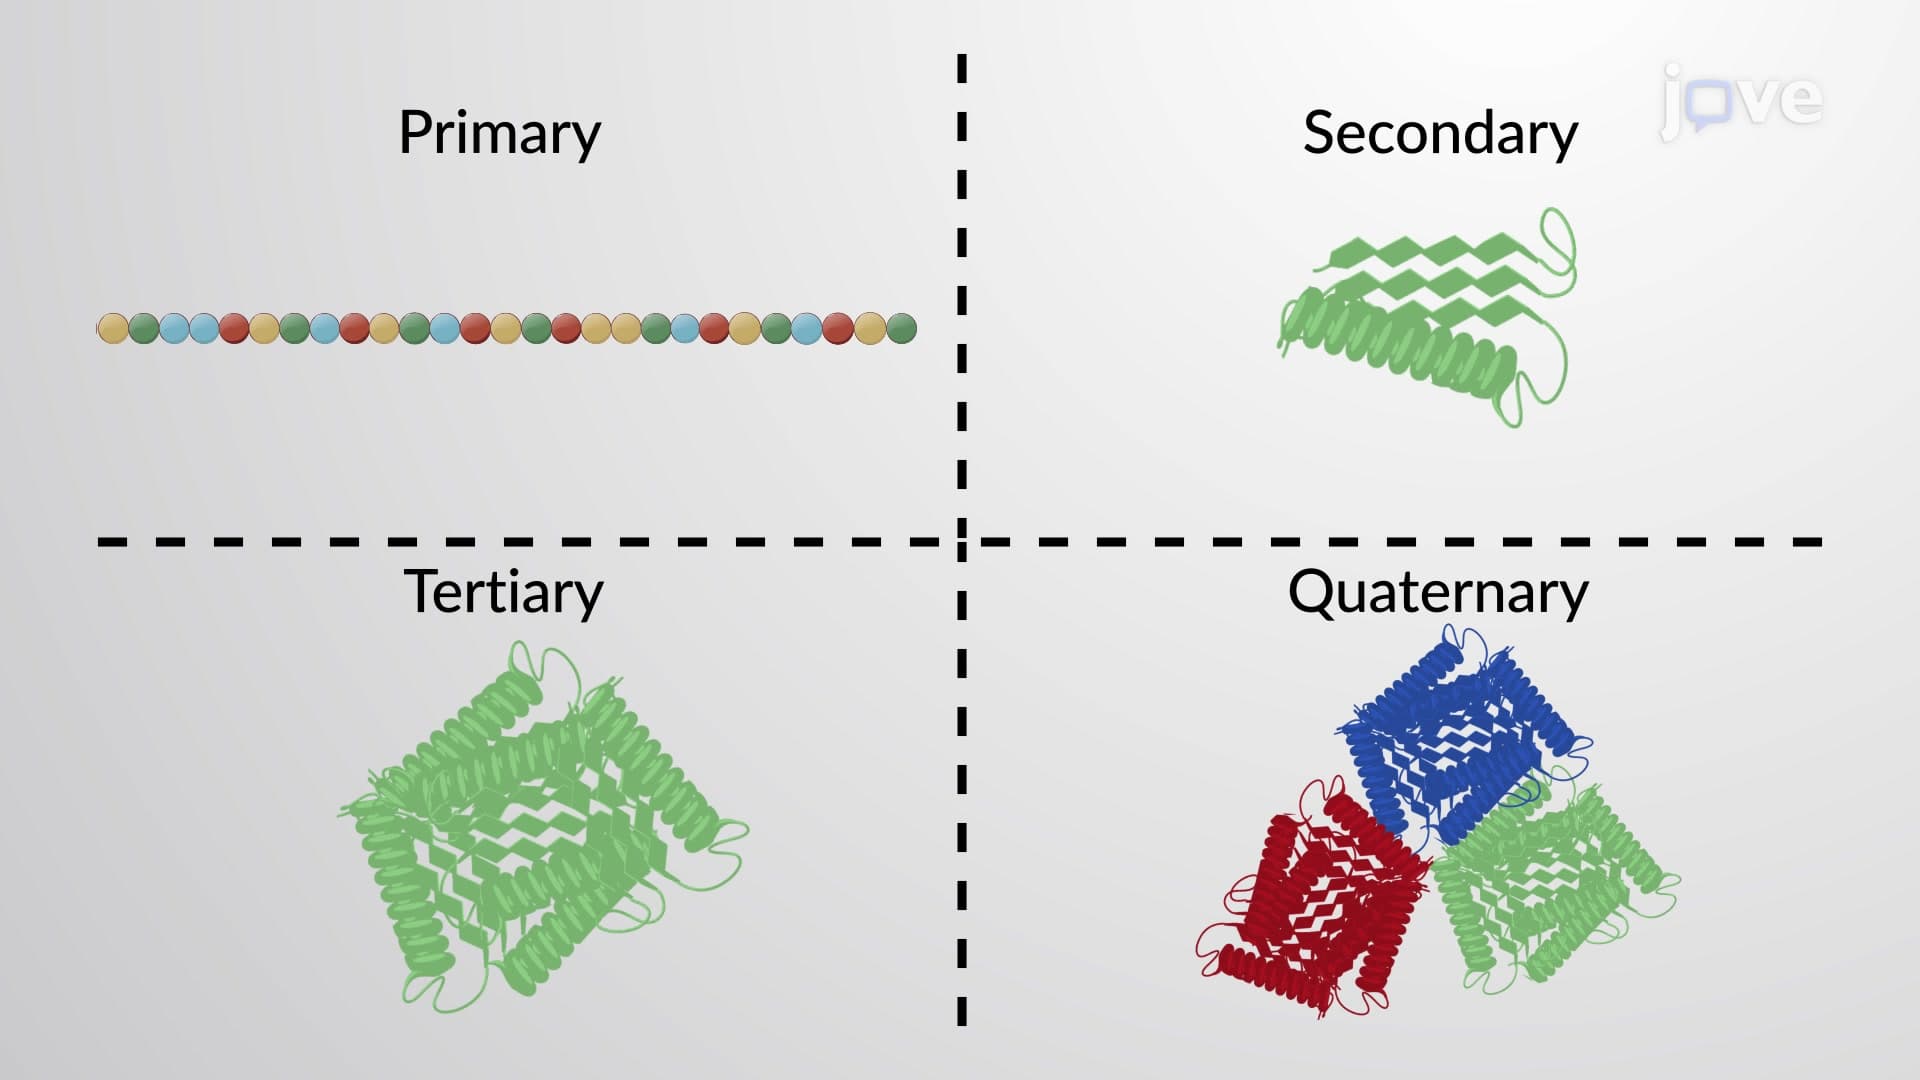
Protein and Protein Structure
A protein's shape is critical to its function. For example, an enzyme can...
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...
 01:29
Malaria
 01:26
Type I Diabetes II: Pathophysiology
 01:24
Parkinson Disease ll: Pathophysiology