Laparoscopic cholecystectomy in patients admitted with acute biliary symptoms
Related Experiment Video
Updated: Nov 7, 2026
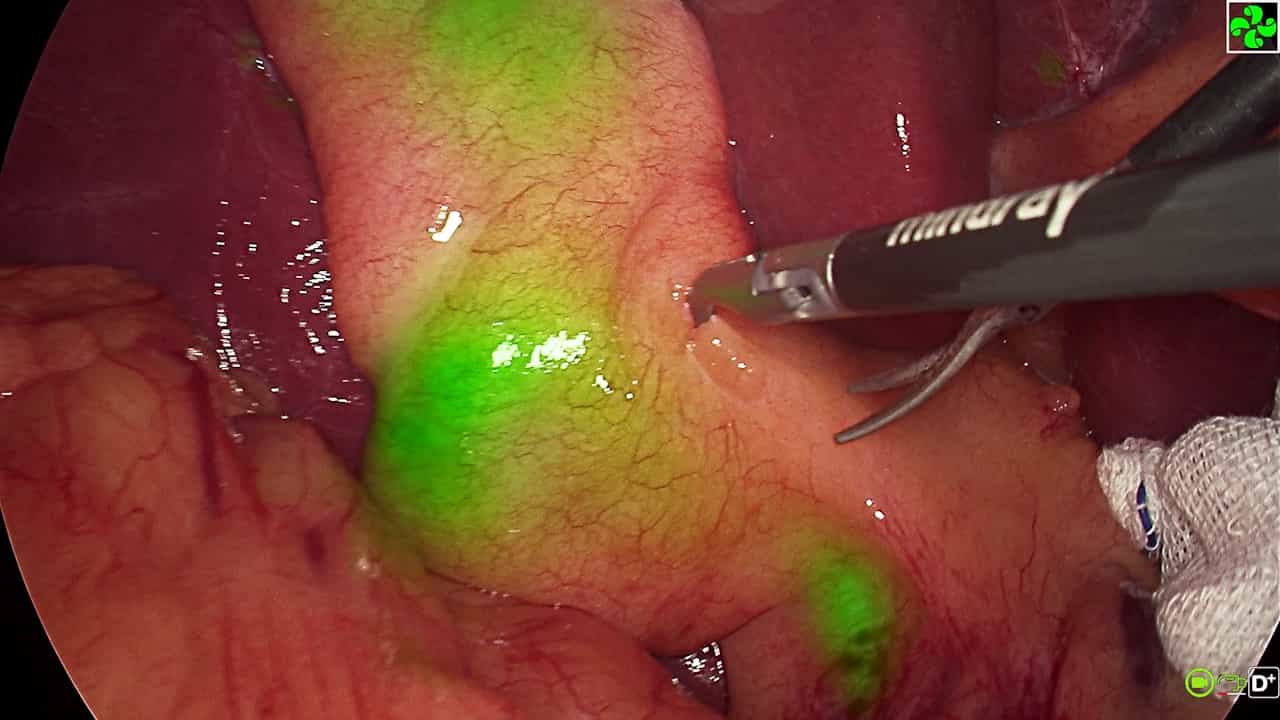
Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
J H Peters1, J Miller, K E Nichols
1Department of Surgery, University of Southern California, Los Angeles 90033.

Abstract:
Laparoscopic cholecystectomy has become the standard of care for the elective management of cholelithiasis. Little information exists, however, regarding the appropriateness of this procedure in the setting of acute symptomatology. We retrospectively reviewed our experience with 516 laparoscopic cholecystectomies performed at a single institution from May 1990 to May 1991. Seventy-five (14.5%) of these patients were admitted from the emergency department with acute abdominal pain (100%), fever (4 of 75, 5%), and/or an elevated white blood cell count (22 of 75, 29%). There were 54 females and 21 males, with a mean age of 50.0 +/- 2.4 years (range: 17 to 89 years). Laparoscopic cholecystectomy was attempted in all patients, and was successful in 68 of 75 patients (91%). Seven procedures were converted to open cholecystectomy because of the difficulty in dissection precluding safe laparoscopic cholecystectomy. The time from admission to surgery (mean: 3.4 +/- 0.3 days), as well as the total hospital stay (mean: 5.5 +/- 0.6 days), was much longer than in the elective circumstance. Mean laboratory values for the group as a whole were as follows: white blood cell count (mean: 9.6 IU/L +/- 0.4 IU/L, range: 4.1 IU/L to 19.5 IU/L), alkaline phosphatase (mean: 97.0 IU/L +/- 13.7 IU/L, range: 27 IU/L to 375 IU/L), and alanine aminotransferase (mean: 78.3 IU/L +/- 13.7 IU/L, range: 15 IU/L to 701 IU/L). Patients requiring open cholecystectomy were older (mean: 61.4 +/- 4.4 versus 48.8 +/- 2.6), were more likely to be febrile (3 of 7, 42%, versus 1 of 68, 1%), and were more likely to have a significant leukocytosis (mean: white blood cell count 12.9 +/- 1.8 x 10(3) cells/mm3 versus 9.2 +/- 0.4 x 10(3) cells/mm3) than were those undergoing successful laparoscopic cholecystectomy. Laparoscopic cholecystectomy can be performed safely in the majority of patients presenting with acute biliary symptoms. Patients with a triad of acute abdominal pain, fever, and elevated white blood cell count, particularly elderly patients, are more likely to require conversion to open cholecystectomy, however.
Related Concept Videos
 01:20
Cholecystitis
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...