Related Experiment Video
Updated: Oct 21, 2026
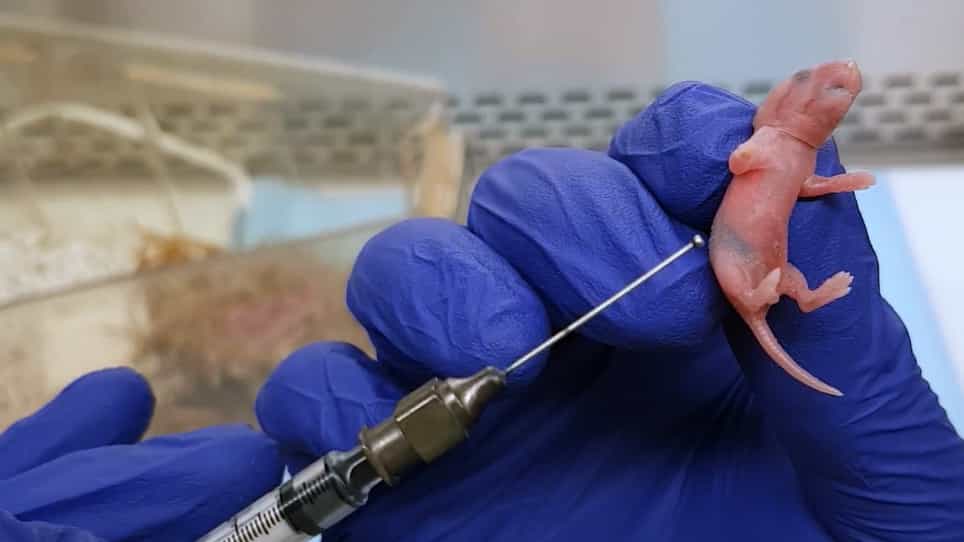
Probiotic Studies in Neonatal Mice Using Gavage
Published on: January 27, 2019
Oral prostaglandin E2 prevents gut atrophy during intravenous feeding but not bacterial translocation
1Department of Surgery, University of Washington Medical School, Seattle 98195.

Abstract:
The pathophysiologic changes in gut physiology that result in bacterial translocation during intravenous feeding are poorly defined, though believed to be related in part to intestinal atrophy, decreased mesenteric blood flow, and lack of intestinal secretions. This study investigated the hypothesis that pharmacologic preservation of intestinal structure and function by orally administered 16,16-dimethyl-prostaglandin E2 would prevent bacterial translocation in intravenously fed rats. Thirty-five rats were randomized to three groups: group 1 was fed rat chow ad libitum, group 2 received standard parenteral nutrition, and group 3 received parenteral nutrition plus oral 16,16-dimethyl-prostaglandin E2 (150 micrograms/kg twice a day). Rats were fed there respective diets for 5 days and killed. Mesenteric lymph nodes were procured for culture, and the intestine was assessed for weight, DNA, protein values, and histologic character. Results demonstrate that orally administered 16,16-dimethyl-prostaglandin E2 potently attenuates the intestinal atrophy associated with parenteral feeding but does not prevent bacterial translocation. Intestinal barrier dysfunction and bacterial translocation during intravenous feeding is related to factors other than the development of gut atrophy.

Related Concept Videos
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:24
Peptic Ulcer Disease II: Pathophysiology