Related Experiment Video
Updated: Oct 24, 2026

Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
[Surgical anatomy of the lymphatic drainage of the bladder]
V Ravery1, D K Chopin, C C Abbou
1Service d'Urologie, Hôpital Henri Mondor, Creteil.

Descriptive anatomy teaches us that the lymphatic drainage of the bladder converges directly on to the middle and internal chains of the external iliac nodes, but never on to the external chain, sometimes on a sacral common iliac node and widely on internal iliac nodes. Surgical observations confirm this: no lymph node metastasis in the external chain of external iliac nodes is noticed, nor common iliac adenopathy without upstream invasion. On the basis of these descriptions, lymphadenectomy was performed from inguinal ligament to iliac bifurcation. Anatomical data largely explain pelvic recurrences due to the existence of unremoved common iliac nodes or unrecognized hypogastric nodes because of difficult access without sacrificing efferent branches of internal iliac artery.
Descriptive anatomy teaches us that the lymphatic drainage of the bladder converges directly on to the middle and internal chains of the external iliac nodes, but never on to the external chain, sometimes on a sacral common iliac node and widely on internal iliac nodes. Surgical observations confirm this: no lymph node metastasis in the external chain of external iliac nodes is noticed, nor common iliac adenopathy without upstream invasion. On the basis of these descriptions, lymphadenectomy was performed from inguinal ligament to iliac bifurcation. Anatomical data largely explain pelvic recurrences due to the existence of unremoved common iliac nodes or unrecognized hypogastric nodes because of difficult access without sacrificing efferent branches of internal iliac artery.
More Related Videos
 07:27
Murine Mesenteric Lymphadenectomy for Selective Disruption of Lymphatic Communication with Region-Specific Gut
Published on: December 30, 2025
 07:37
Surgical Protocols for Deep Cervical Lymphovenous Anastomosis in a Rat Model: Lymph Node and Lymphatic Vessel Anastomoses
Published on: November 14, 2025
Related Concept Videos
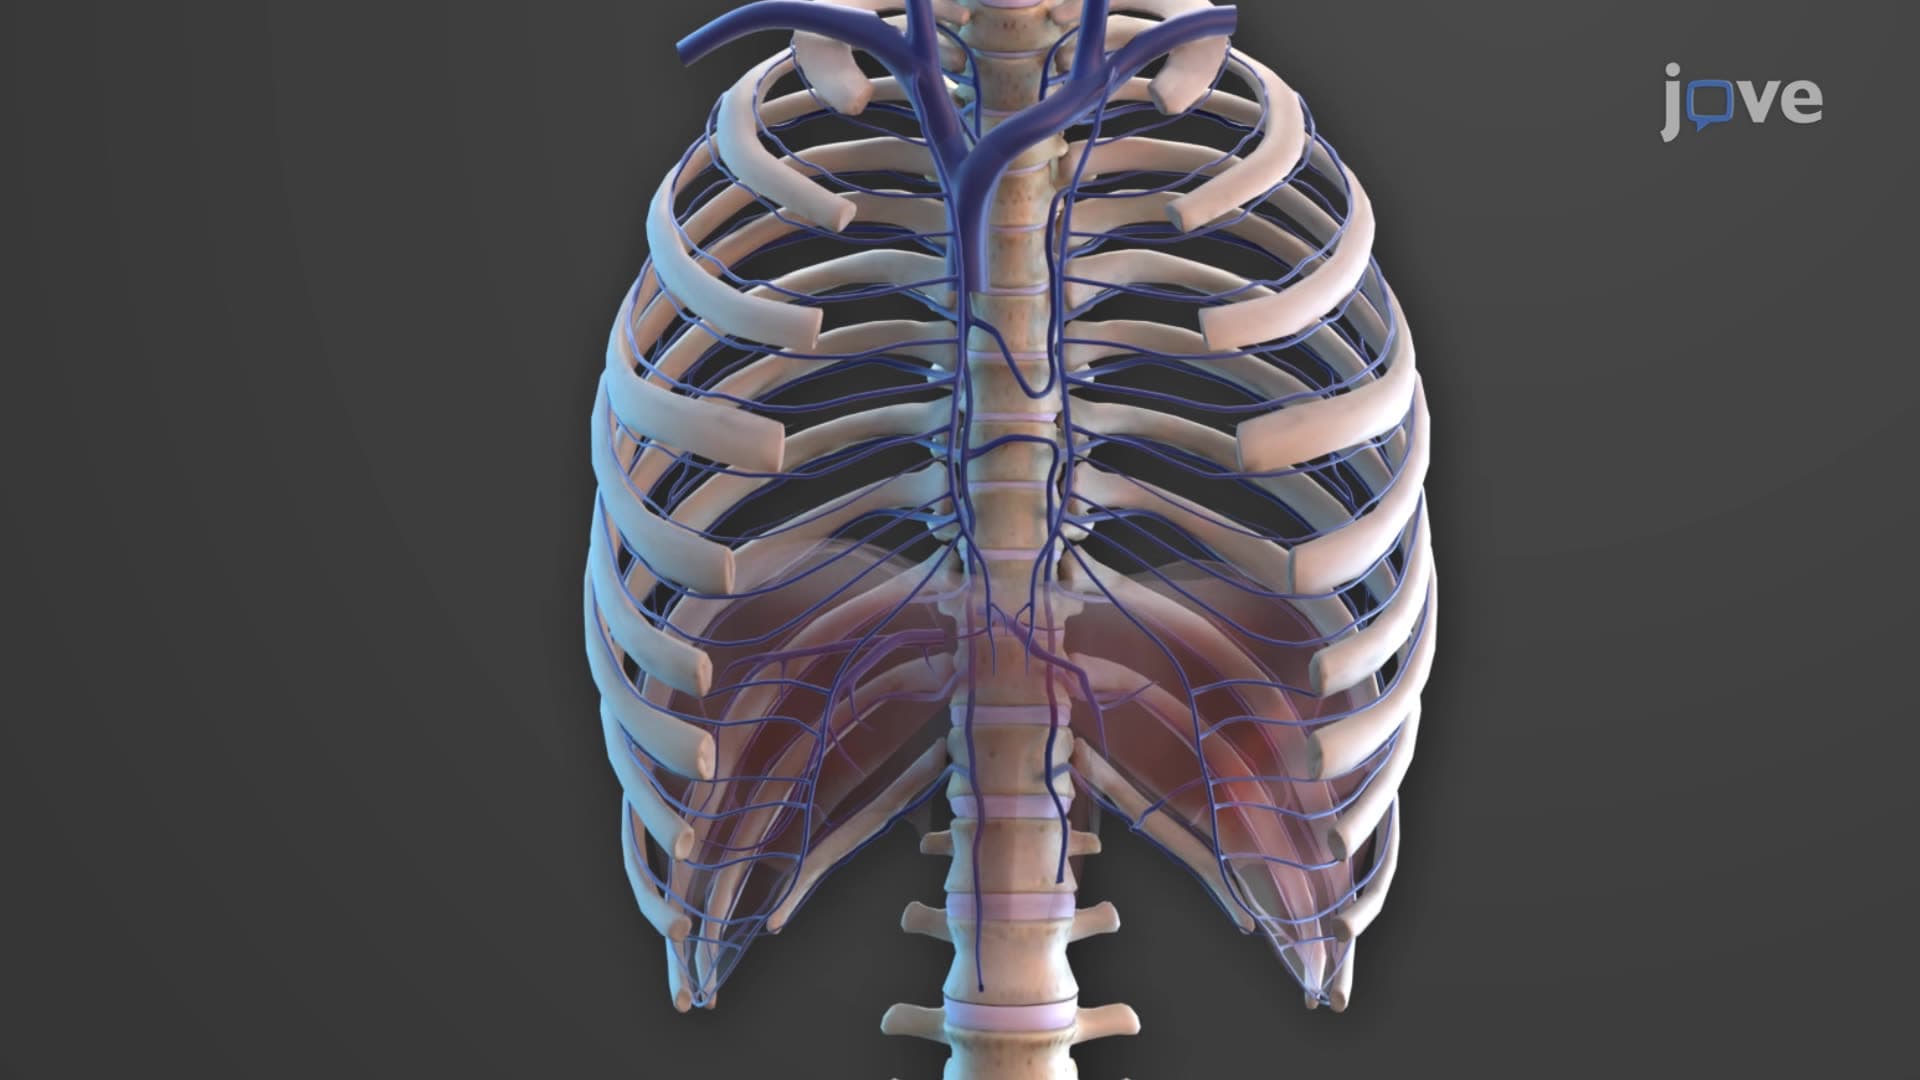 01:19
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular spaces.
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra