Related Experiment Video
Updated: Jul 29, 2026
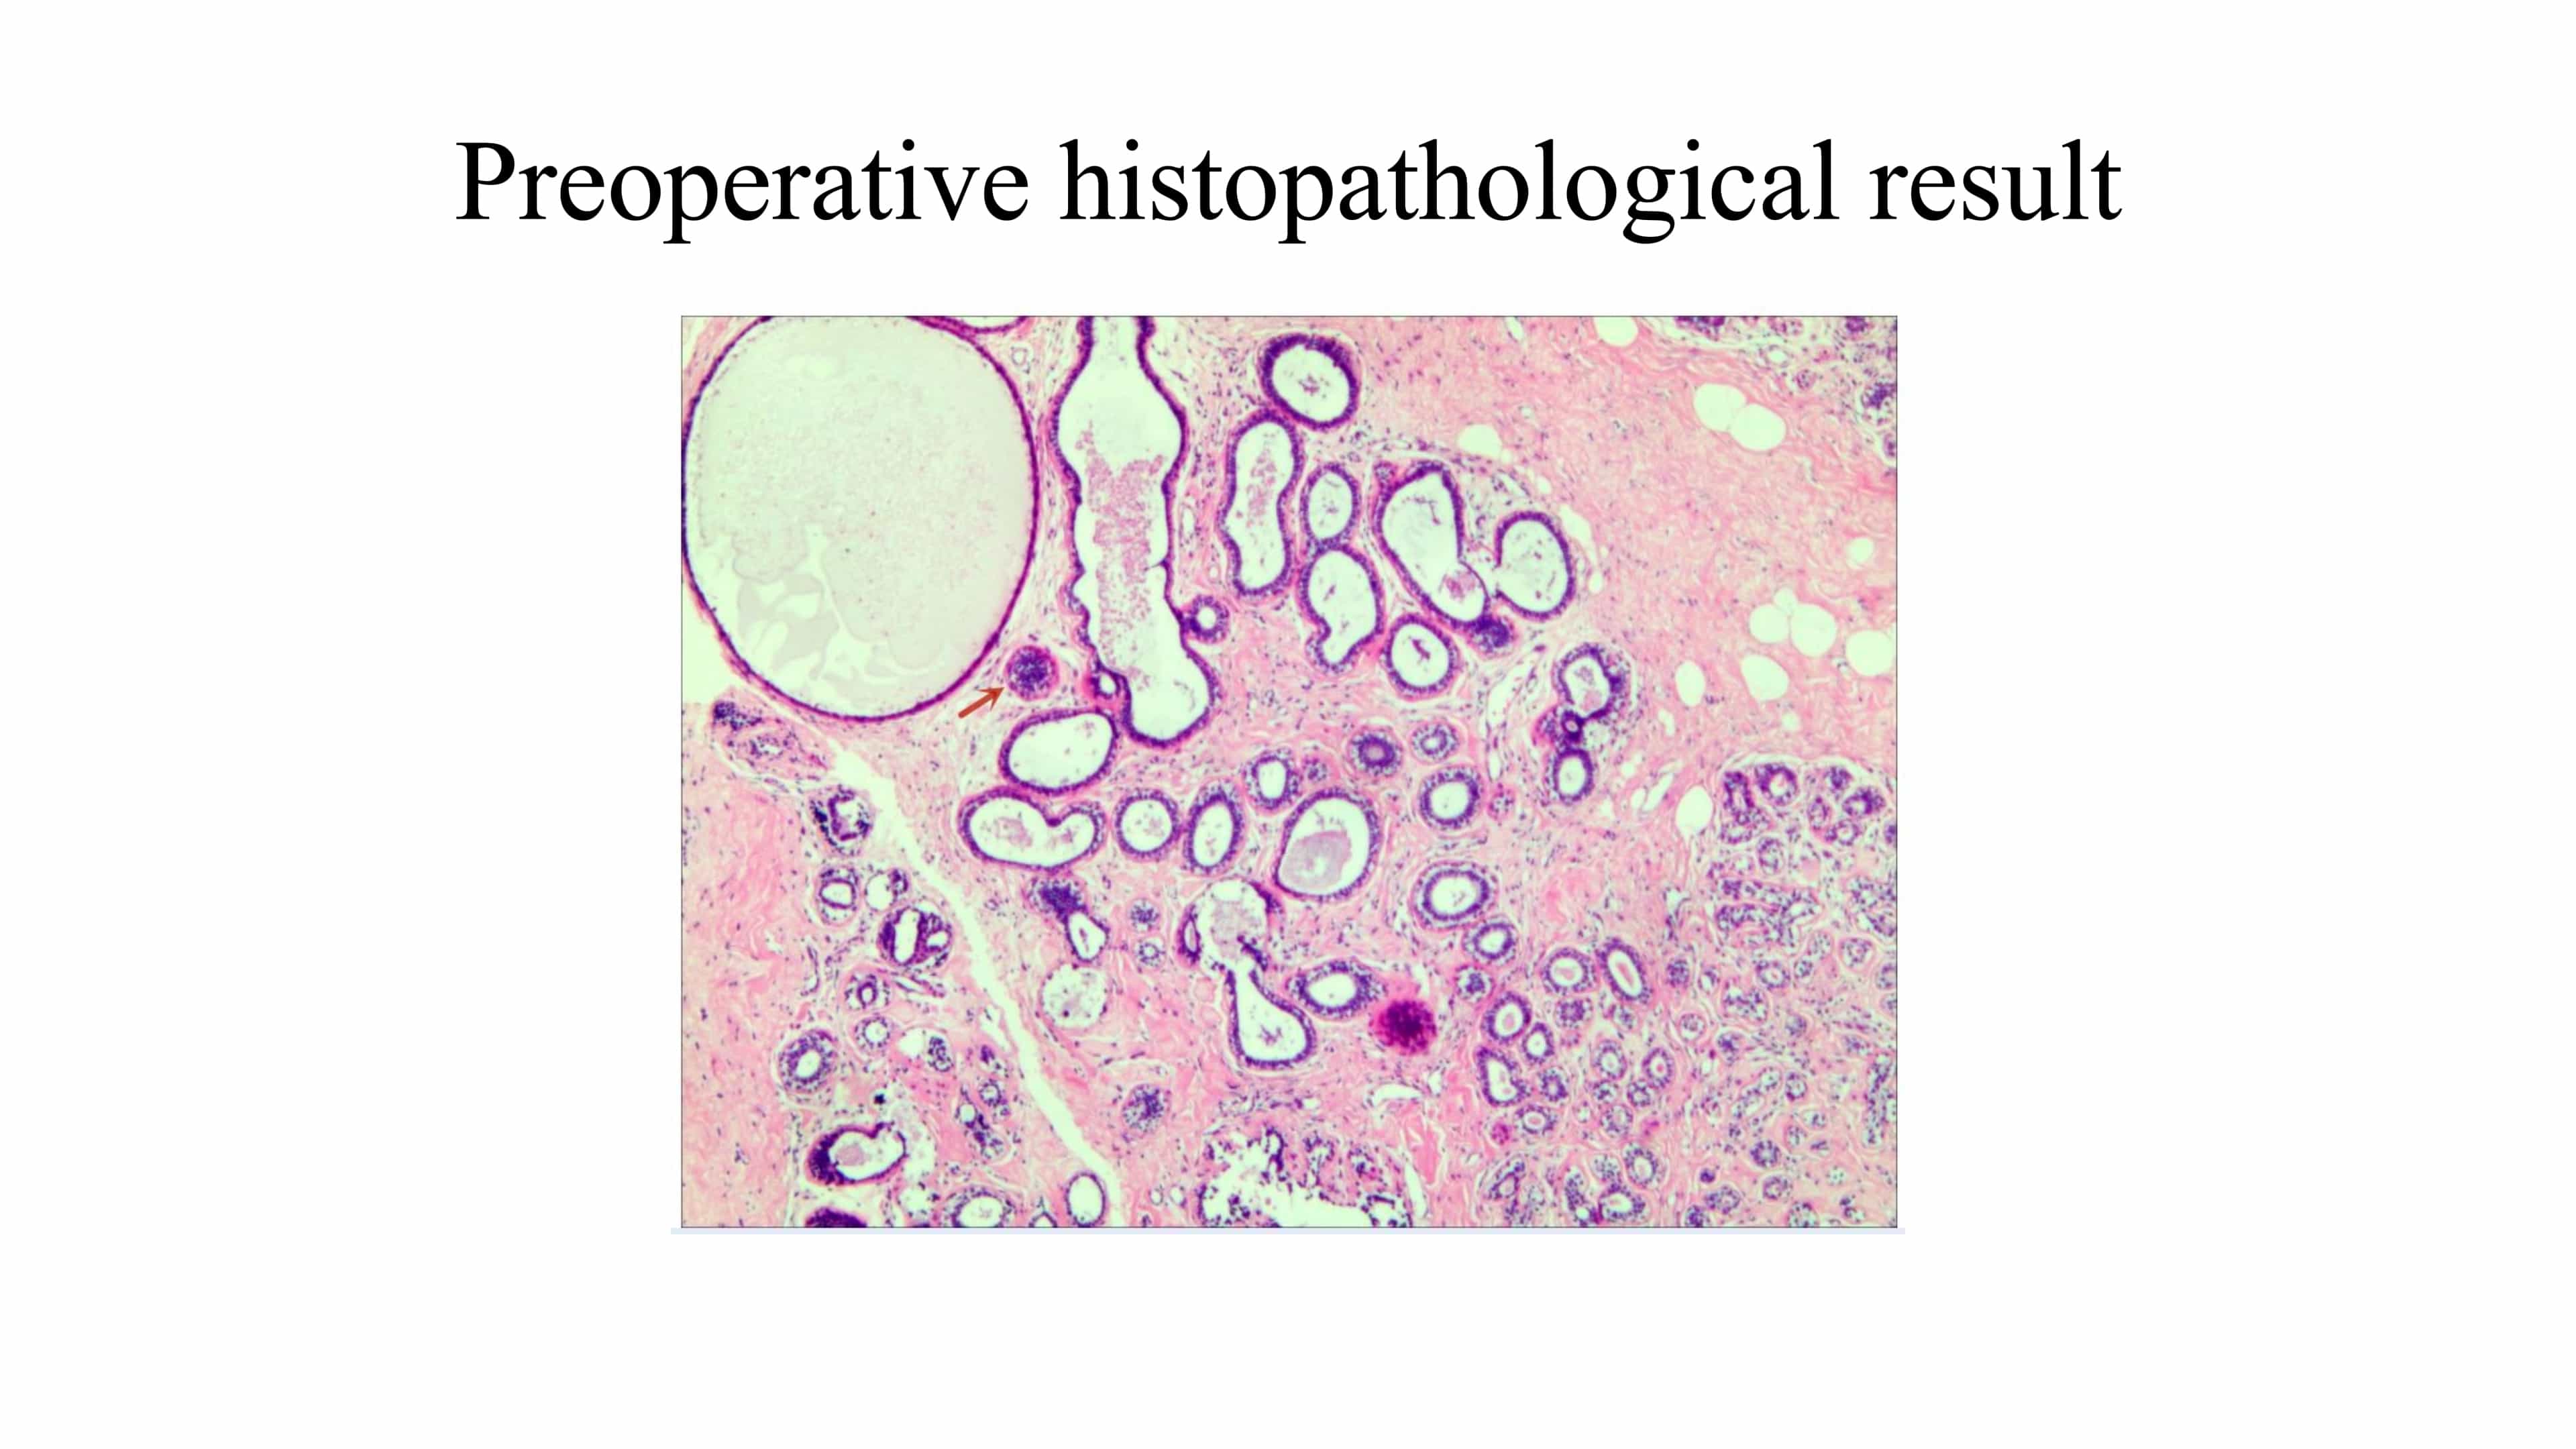

Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Infection of mammary prostheses: a survey and the question of prevention
1University of Minnesota Medical School, Minneapolis.

Seventy-three plastic surgeons reported 60 early and late mammary implant infections among 54,661 implantations. Smooth, textured, and polyurethane-coated implants had similar infections rates (respectively, 0.06%, 0.16%, and 0.12% for augmentations and 0.6%, 0.4%, and 0.3% for reconstructions including revisions and expansions). Insertion routes and implant placements had no influence on infection rates. Causative bacteria included Staphylococcus aureus and S. epidermidis, Streptococci A and B, enterobacteria, Klebsiella, Pseudomonas, and mycobacteria. Most surgeons followed a regimen of topical and/or systemic prophylaxis. Some (approximately 20%) used the Dolsky insertion sleeve. Whereas smoking, obesity, and diabetes did not significantly predispose to infection, the following did: skin atrophy and scarring, corticosteroids in subglandular augmentation, additional simultaneous surgery, pregnancy, preceding lactation, and vigorous exercising, massage, and trauma postsurgically. Few late implant infections were recorded resulting from bacterial milk duct invasion or hematogenously from antecedent infection foci. The need for and the possibilities of preventive measures are critically discussed.
Seventy-three plastic surgeons reported 60 early and late mammary implant infections among 54,661 implantations. Smooth, textured, and polyurethane-coated implants had similar infections rates (respectively, 0.06%, 0.16%, and 0.12% for augmentations and 0.6%, 0.4%, and 0.3% for reconstructions including revisions and expansions). Insertion routes and implant placements had no influence on infection rates. Causative bacteria included Staphylococcus aureus and S. epidermidis, Streptococci A and B, enterobacteria, Klebsiella, Pseudomonas, and mycobacteria. Most surgeons followed a regimen of topical and/or systemic prophylaxis. Some (approximately 20%) used the Dolsky insertion sleeve. Whereas smoking, obesity, and diabetes did not significantly predispose to infection, the following did: skin atrophy and scarring, corticosteroids in subglandular augmentation, additional simultaneous surgery, pregnancy, preceding lactation, and vigorous exercising, massage, and trauma postsurgically. Few late implant infections were recorded resulting from bacterial milk duct invasion or hematogenously from antecedent infection foci. The need for and the possibilities of preventive measures are critically discussed.
Related Concept Videos
 01:30
Bacterial Signaling
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:25
Clinical Significance of Antibiotic Resistance