Related Experiment Video
Updated: Oct 24, 2026

An In Vivo Mouse Model of Total Intravenous Anesthesia During Cancer Resection Surgery
Published on: June 8, 2021
The role of muscle relaxants in total intravenous anaesthesia
1Department of Anaesthesia, Manchester Royal Infirmary, UK.

For total intravenous anaesthesia (TIVA), all drugs that are required as part of the anaesthetic method are administered intravenously. This is usually taken to imply the use of intravenous infusions. It is normal practice to administer muscle relaxants intravenously, although other routes have been used. A muscle relaxant is required firstly to secure paralysis and secondly to maintain paralysis. The rate of onset of all the nondepolarizing neuromuscular blocking agents which are routinely available at present is similar; it takes about 3-6 min for a normal clinical dose to reach maximum effect. Maintenance of an adequate level of block is necessary, and it is usually helpful to the surgeon for the level of block to be relatively constant. The choice of drug is important. It should cause negligible side-effects. For administration by infusion, an agent with an intermediate (e.g., atracurium) or short (e.g., mivacurium) duration of action is essential to ensure a rapid recovery of effect on termination of the infusion. The routine use of neuromuscular monitoring is recommended when a continuous infusion of a relaxant is used.
For total intravenous anaesthesia (TIVA), all drugs that are required as part of the anaesthetic method are administered intravenously. This is usually taken to imply the use of intravenous infusions. It is normal practice to administer muscle relaxants intravenously, although other routes have been used. A muscle relaxant is required firstly to secure paralysis and secondly to maintain paralysis. The rate of onset of all the nondepolarizing neuromuscular blocking agents which are routinely available at present is similar; it takes about 3-6 min for a normal clinical dose to reach maximum effect. Maintenance of an adequate level of block is necessary, and it is usually helpful to the surgeon for the level of block to be relatively constant. The choice of drug is important. It should cause negligible side-effects. For administration by infusion, an agent with an intermediate (e.g., atracurium) or short (e.g., mivacurium) duration of action is essential to ensure a rapid recovery of effect on termination of the infusion. The routine use of neuromuscular monitoring is recommended when a continuous infusion of a relaxant is used.

Related Concept Videos
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic drugs,...
 01:24
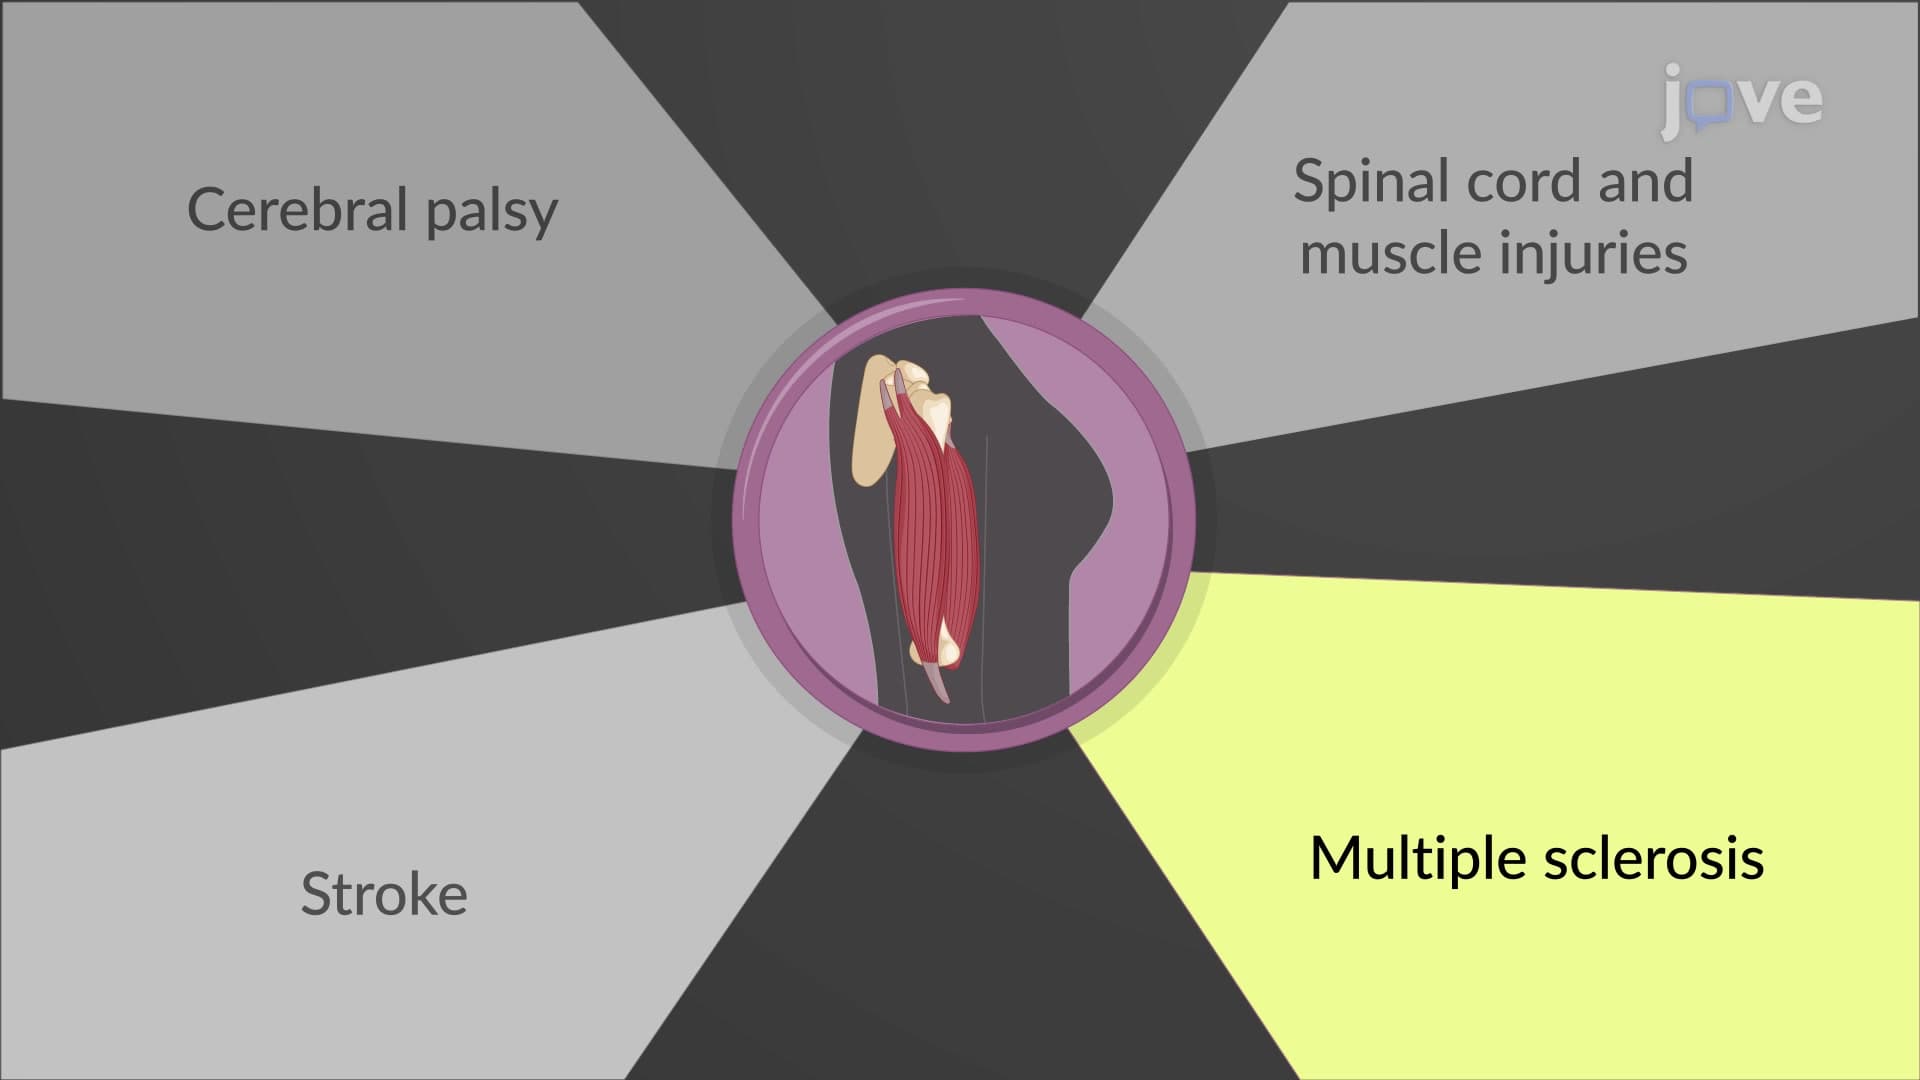
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...