Related Experiment Video
Updated: Oct 20, 2026
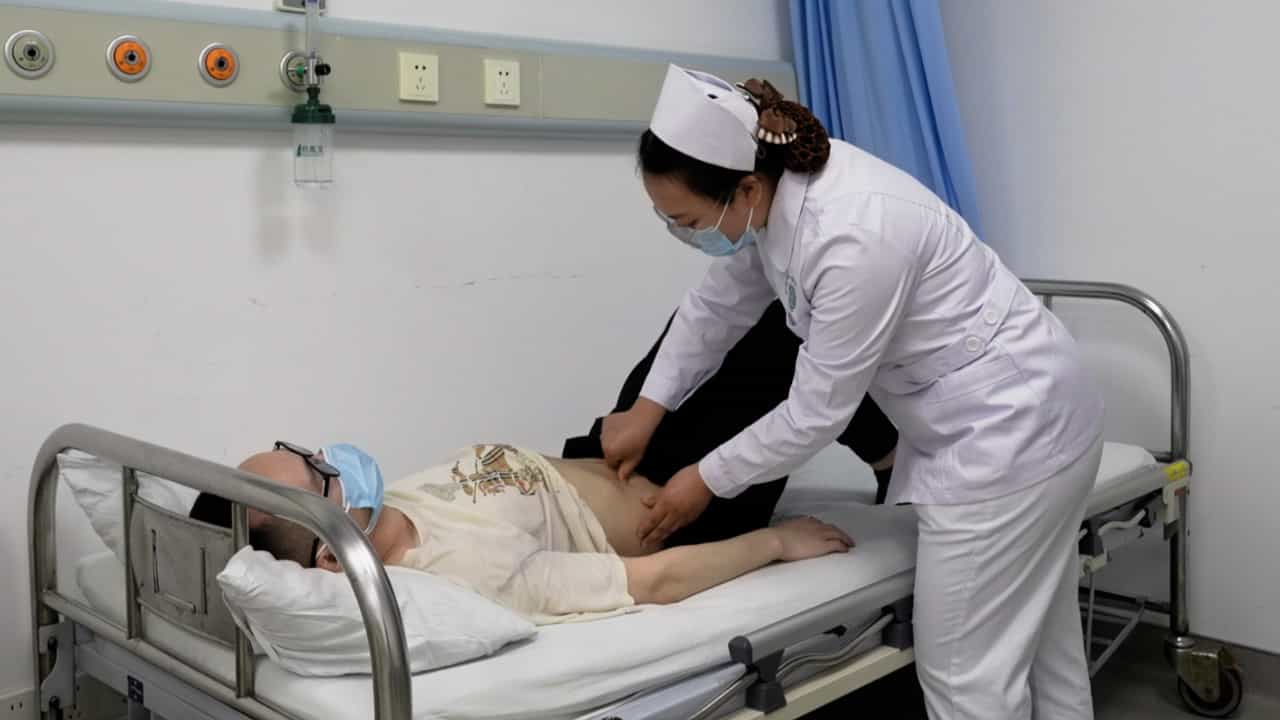
Acupoint Application Combined with Acupoint Massage for Treating Constipation in a Patient with Chronic Obstructive Pulmonary Disease
Published on: August 18, 2023
Constipation and fecal incontinence in the elderly population
Y Romero1, J M Evans, K C Fleming
1Division of Gastroenterology and Internal Medicine, Mayo Clinic Rochester, Minnesota 55905, USA.

Objective:
To describe the assessment and management of constipation and fecal incontinence in elderly patients.
Design:
We reviewed pertinent publications in the recent medical literature and outlined effective management strategies for constipation and fecal incontinence in the geriatric population.
Results:
Constipation can be classified into two syndromes--functional constipation and rectosigmoid outlet delay. Evaluation consists of elicitation of a detailed history, directed physical examination, and selected laboratory tests. Management involves nonpharmacologic (such as exercise and fiber) and pharmacologic measures. Fecal incontinence in elderly patients can be due to stool impaction, medications, dementia, or neuromuscular dysfunction. Management options include modification of contributing disorders, pharmacologic therapy, and behavioral techniques.
Conclusion:
Constipation and fecal incontinence are common and often debilitating conditions in elderly patients. Management should be highly individualized and dependent on cause, coexisting morbidities, and cognitive status.
Related Concept Videos
 01:21
Drugs for Treatment of Constipation-Predominant IBS
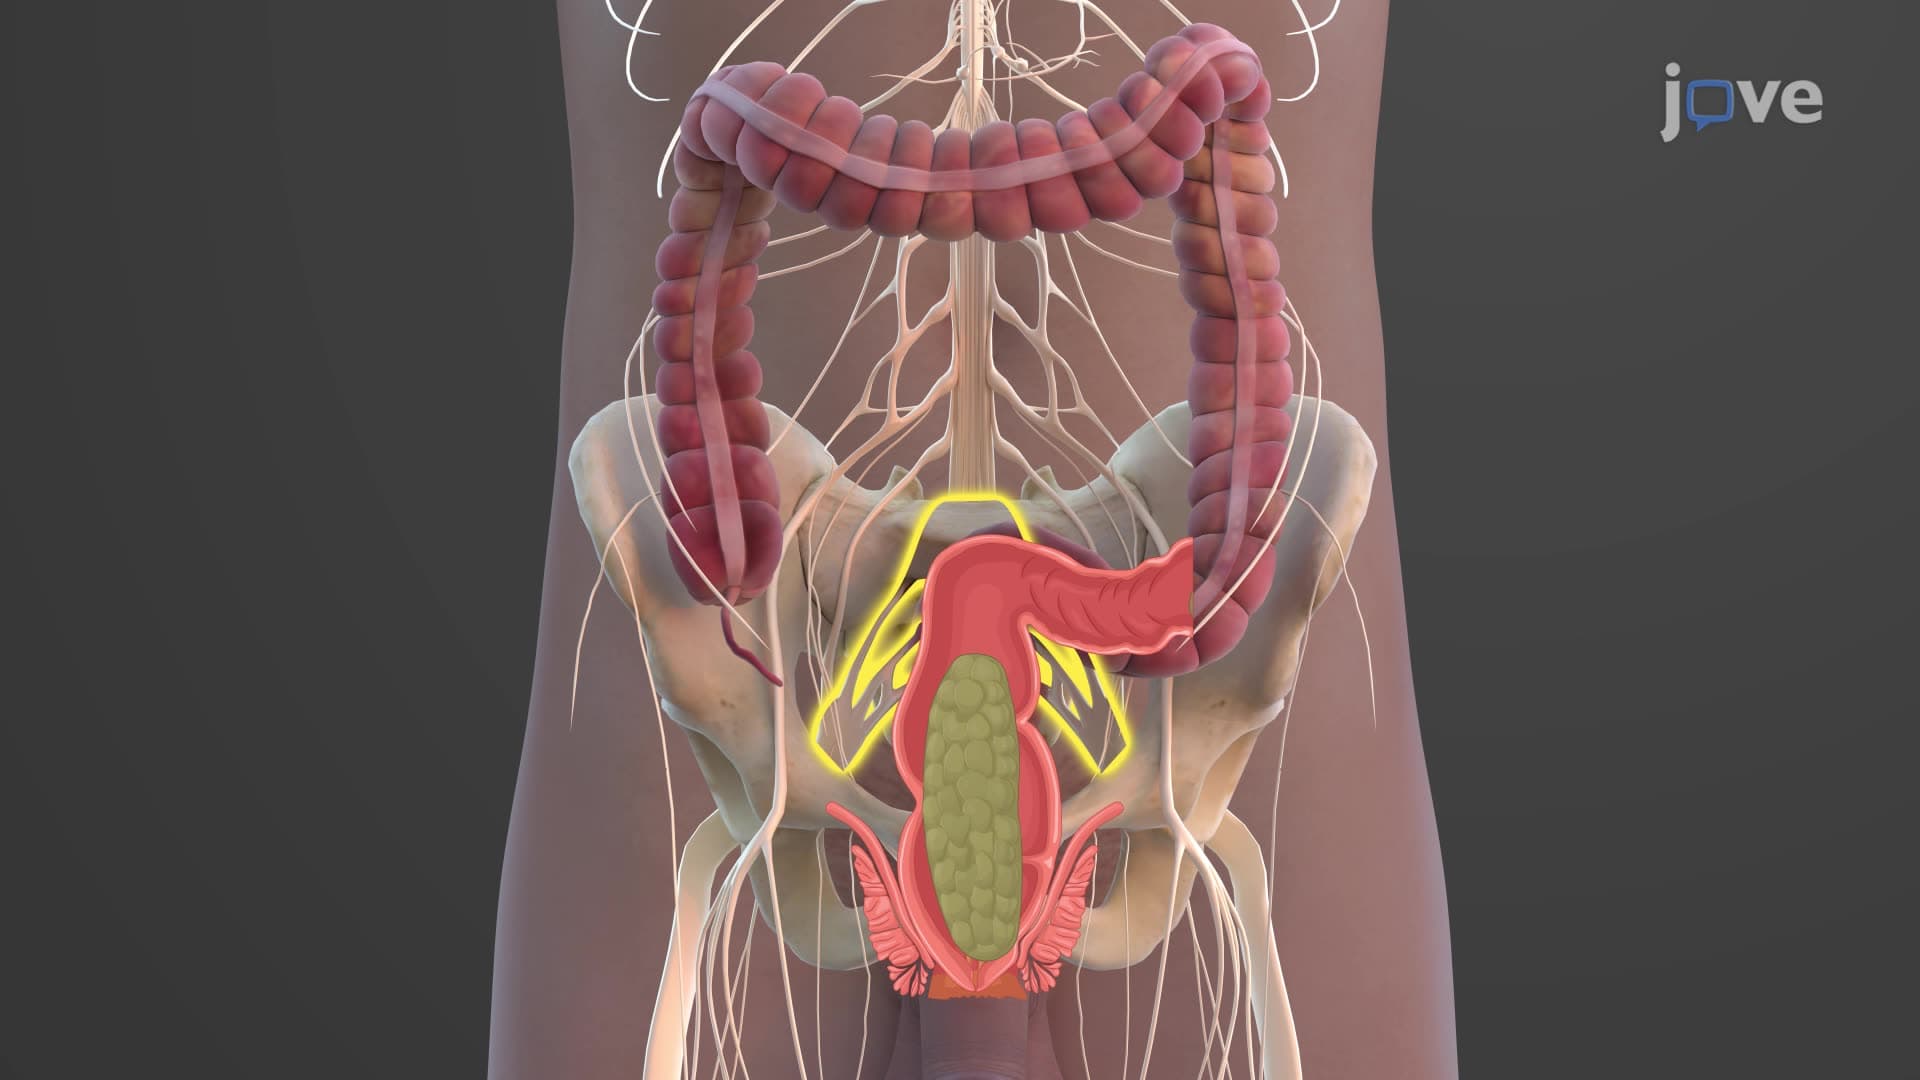 01:26
Feces Formation and Defecation
The mass peristalsis then pushes the feces into the rectum, which stretches the rectal walls to activate...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:15
Drug Dosing: Geriatric Patients
 01:22
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Absorption
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion