Higher Kt/V is needed for adequate dialysis if the treatment time is reduced. Insights from a blood flow distribution model
Related Experiment Video
Updated: Aug 16, 2026
Normothermic Ex Vivo Kidney Perfusion for the Preservation of Kidney Grafts prior to Transplantation
Published on: July 15, 2015
1Department of Nephrology, University of Göteborg, Sweden.

Abstract:
The widely used Kt/V concept for quantitating haemodialysis (HD) and ensuring adequate dialysis is based on several assumptions. In order to simplify the urea kinetic modelling, the body is assumed to be a single well-mixed compartment. Previously, more physiological two-compartment or blood flow distribution models have been used to explain the phenomenon of blood urea rebound after dialysis. This study attempts to evaluate the effects of a multi compartment model on the removal of urea, i.e. on the adequacy of dialysis. Four different tissue compartments of similar size are used, with flow rates between 40 and 3600 ml/min for a bodyweight around 70 kg, allowing for blood flow heterogeneity within and between skeletal muscles. Dialysis is simulated by removing blood containing urea and replacing it with blood free of urea, during isovolumetric conditions and assuming no diffusion barriers for urea. Several important conclusions can be drawn from the model. Firstly the removal of urea is dependent both on the time of dialysis and on the number of HD treatments per week despite constant Kt/V. Secondly the blood urea concentration is increased after dialysis--'urea rebound'--in accordance with clinical data. Thirdly the concept of blood flow distribution can fully explain the difference between haemodialysis and peritoneal dialysis in terms of Kt/V needed for adequate dialysis. Thus a weekly Kt/V of 3.6 for HD 4 h 3 times per week removes the same amount of urea as CAPD and a Kt/V of 2.1. Also, nightly intermittent PD requires similar Kt/Vs (approximately 0.1 higher) as CAPD to obtain equivalent removal of urea. Finally the crucial point is that the Kt/V required for adequate dialysis must be increased if the dialysis treatment time is reduced. If not, the patient with renal insufficiency suffers the risk of being under-dialysed.
Related Concept Videos
 01:09
One-Compartment Model: IV Infusion
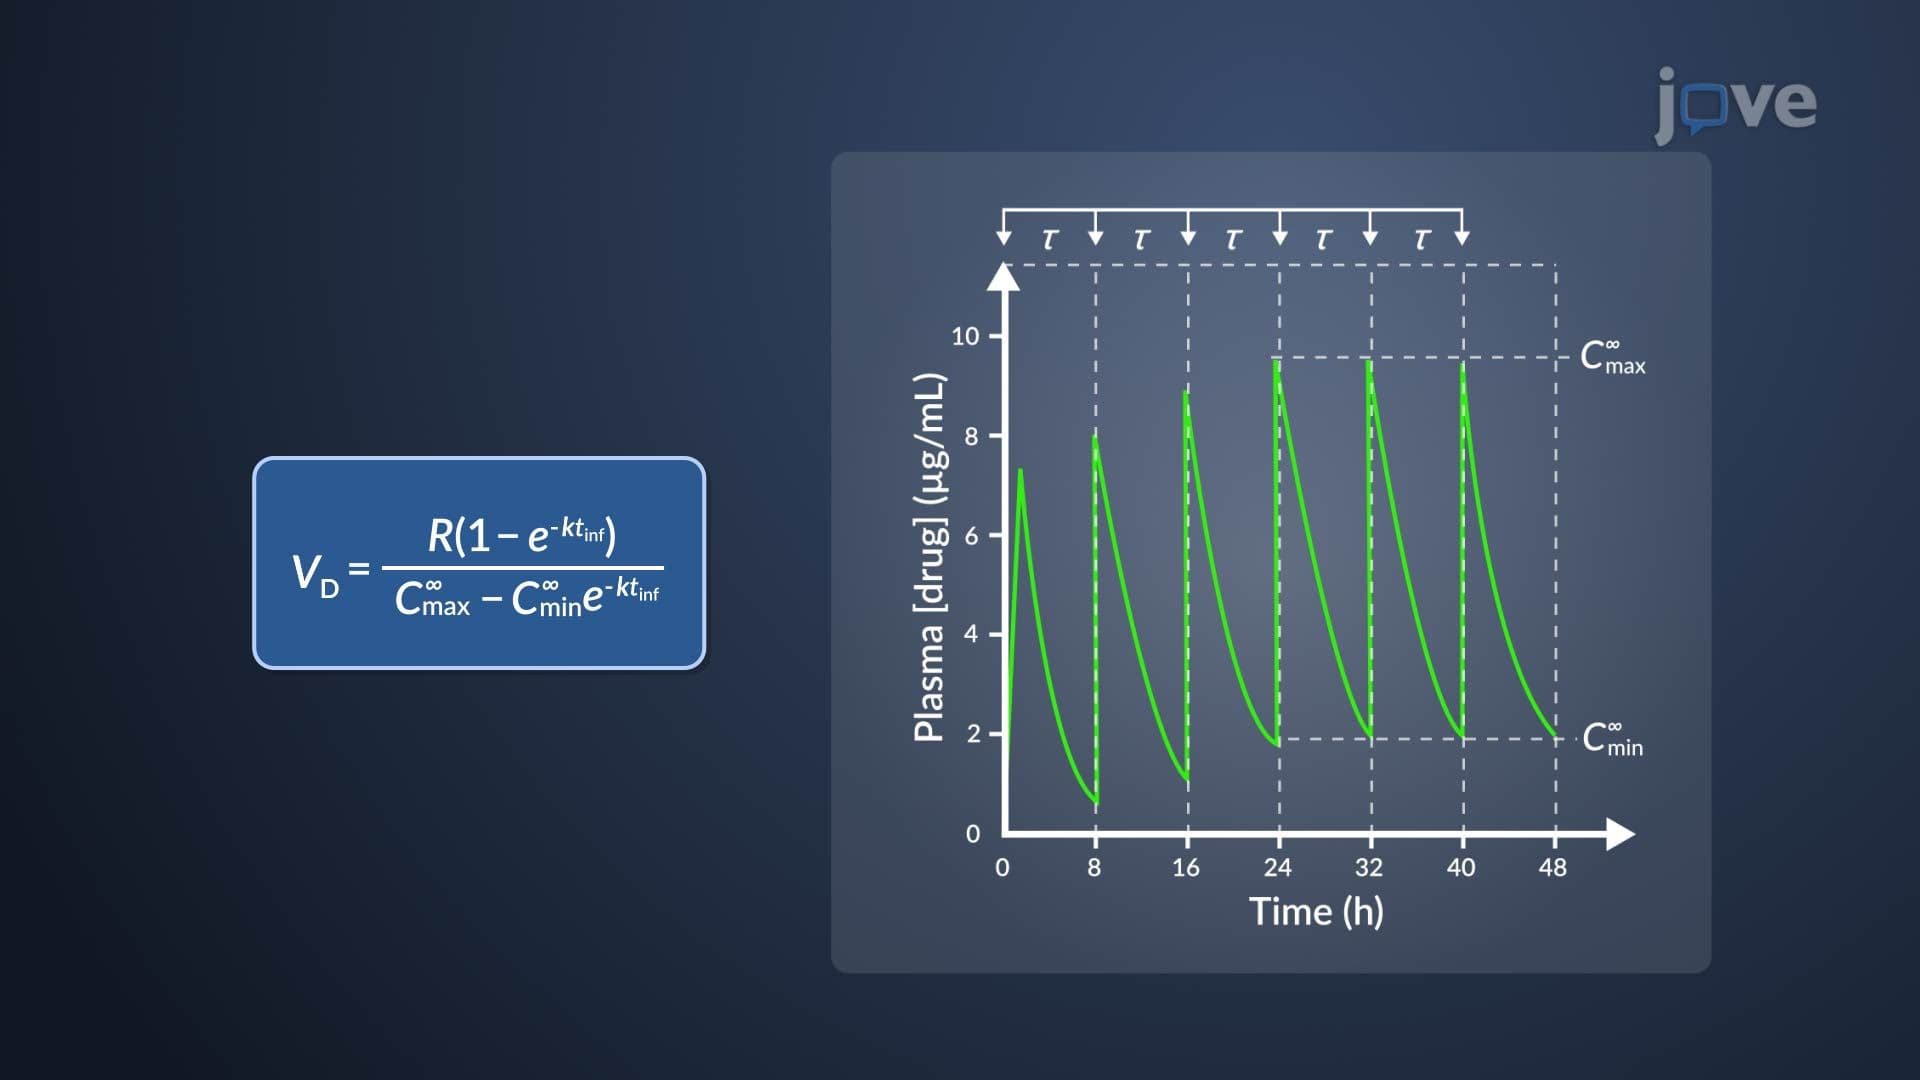
The one-compartment model for IV infusion uses mathematical equations to describe the rate of change in drug quantity in the body. At steady-state or infusion equilibrium, the drug input...
 01:20
Estimation of k and VD of Aminoglycosides
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy
 01:25
Hemodialysis I: Introduction
 01:20
Acute Kidney Injury V: Interprofessional Care