Preoperative valproate administration does not increase blood loss during temporal lobectomy
Related Experiment Video
Updated: Nov 6, 2026
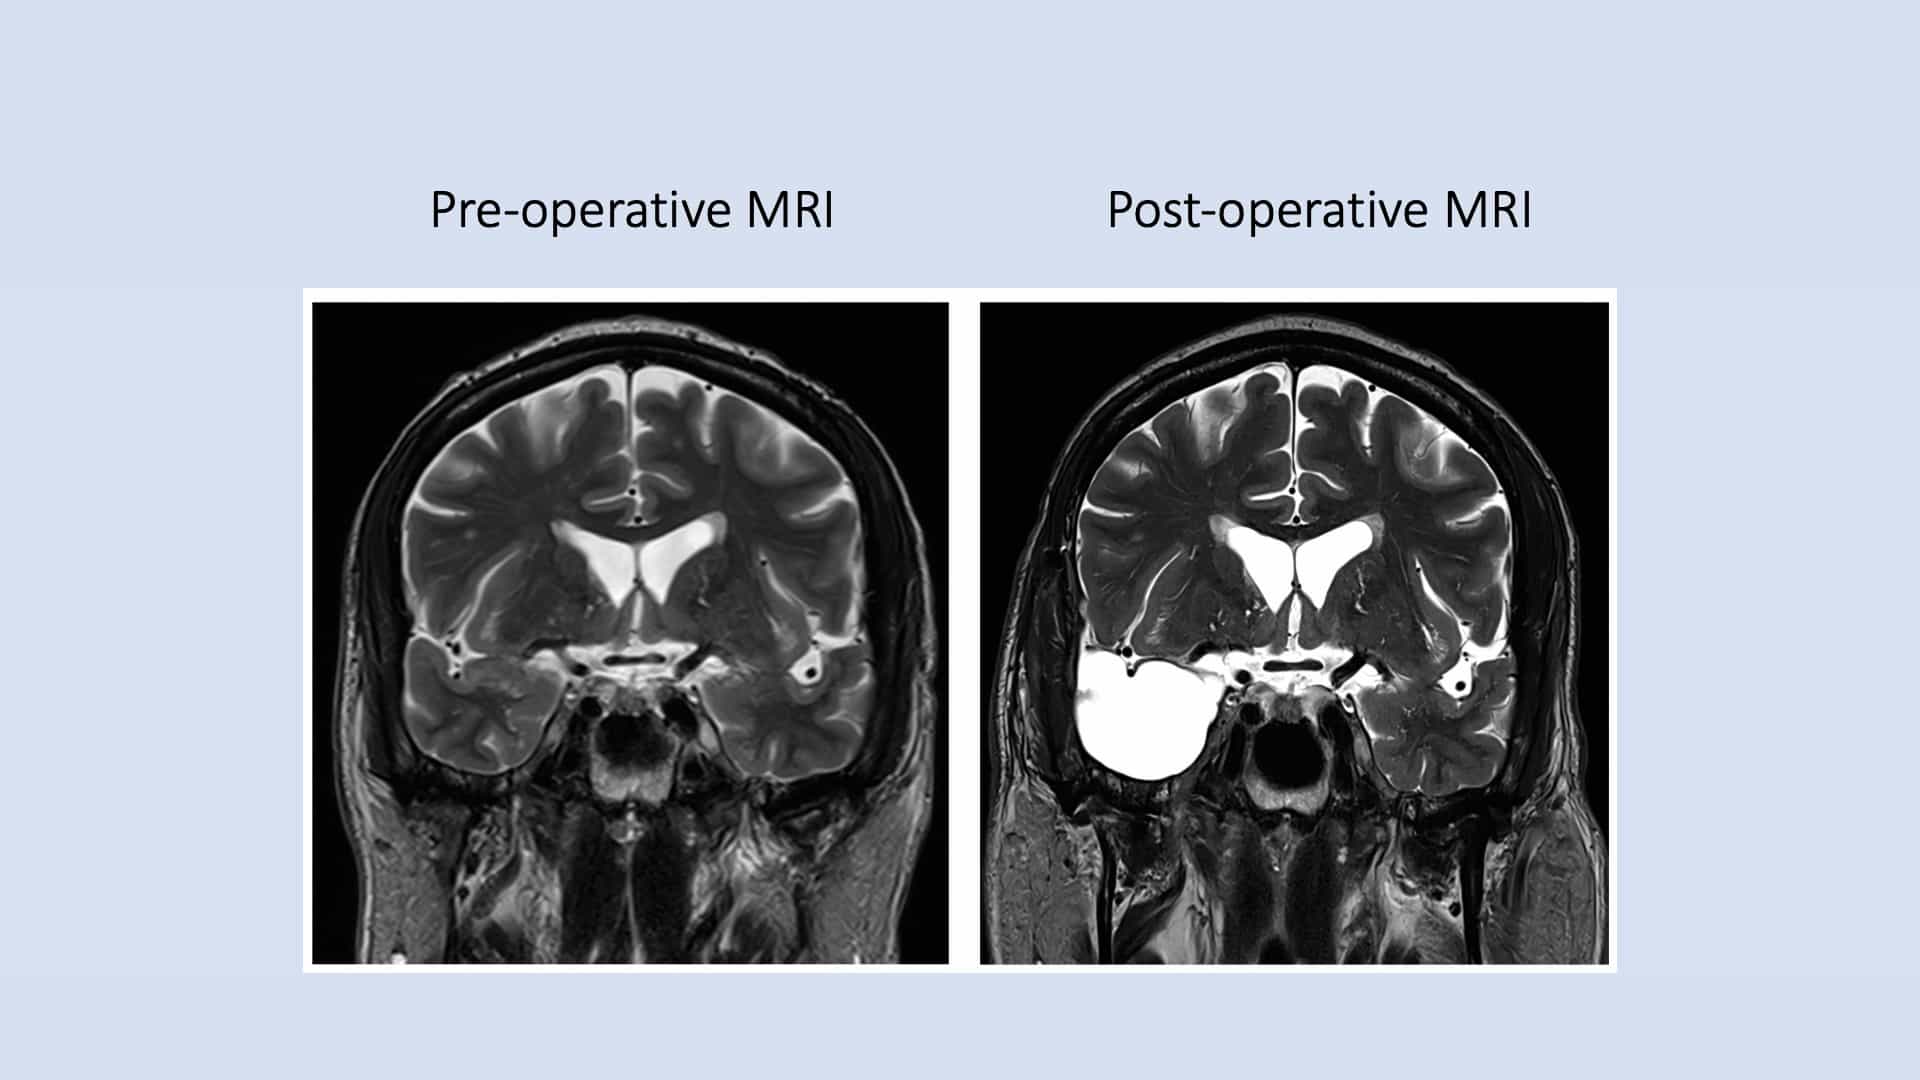
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
M M Ward1, N M Barbaro, K D Laxer
1Department of Neurosurgery, University of California, San Francisco, USA.

Abstract:
Surgical treatment is increasingly used for patients with medically re fractory seizures. Valproate (VPA) is an effective, widely used anticonvulsant in this patient population, but believed by some researchers to increase surgical bleeding because of quantitative thrombocytopenia and functional defects in platelet aggregation. Because we have observed no clinical evidence that perioperative administration of VPA increases blood loss or complications related to postoperative bleeding in patients undergoing temporal lobectomy at our institution, we sought to test this hypothesis. We made a retrospective review of the medical records of all patients who underwent epilepsy surgery at the University of California, San Francisco Medical Center, from September 1986 through January 1993. Patients who had a temporal lobectomy and whose medical records documented preoperative platelet counts and pre- and postoperative hematocrit and hemoglobin values were included. We excluded patients who had cranial surgery before temporal lobectomy and those with intracranial neoplasms or vascular malformations. Patients were divided into two groups: those who received VPA in the immediate preoperative period and those who had not received VPA recently. We compared the estimated surgical blood loss and the estimated change in red blood cell (RBC) volume between groups by unpaired t tests. The charts of 87 consecutive patients qualified for inclusion in the study. Patients in the VPA group had relative (but not absolute) thrombocytopenia preoperatively (235 +/- 64 vs. 277 +/- 69 k in the No-VPA group). There were no differences in the estimated blood loss, RBC volume, or in the incidence of postoperative transfusion. VPA apparently does not increase complications of hemostasis during therapeutic surgical resections for epilepsy. Therefore, we do not recommend routinely discontinuing VPA before craniotomy.
Related Concept Videos
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...