Prophylactic application of thyrostatic drugs during excessive iodine exposure in euthyroid patients with thyroid autonomy: a randomized study
Related Experiment Video
Updated: Nov 5, 2026

Generation of a Mouse Spontaneous Autoimmune Thyroiditis Model
Published on: March 17, 2023
1Department of Gastroenterology and Endocrinology, Georg-August-Universitat, Gottingen, Germany.

In a prospective, randomized study we examined the influence of prophylactic short-term thyrostatic therapy on thyroid iodine metabolism in patients with euthyroid autonomy undergoing elective coronary angiography. From a total of 1177 patients, 51 fulfilled the criteria of euthyroid autonomy before coronary angiography (negative thyrotropin-releasing hormone test, 10-min uptake of at least 1.2%, 99mTc and no elevation of free thyroxine and free triiodothyronine indices) and were randomized into three groups: group 1 (N = 17) received 20mg/day of thiamazole and group 2 (N = 17) received 900 mg/day of sodium perchlorate; thyrostatic therapy was begun on the day before angiography and continued for 14 days; group 3 (N = 17) served as controls without treatment. Parameters of thyroid function-free thyroxine (FT4) index and free triiodothyronine (FT3) index, thyrotropin (TSH) and delta-TSH urine iodine excretion and 99mTc uptake were determined before and 30 days after coronary angiography. At the end of the study the mean FT4 index and FT3 index were elevated significantly in the control group compared with baseline values, but were still within the normal range. In contrast, the mean FT4 index and FT3 index remained unchanged in the treated groups. Four mild cases of hyperthyroidism were observed at the end of the study: two cases in the control group and one case in each of the treated groups. Thyrotropin suppression, urine iodine excretion and 99mTc uptake differed significantly between the treated groups and the control group. In the treated groups TSH suppression, urine iodine excretion and 99mTC uptake remained unchanged 30 days after coronary angiography compared with baseline values. In the control group the degree of TSH suppression and the level of urine iodine excretion increased (about twofold) significantly after coronary angiography, whereas 99mTc uptake decreased significantly (ca. 50%). In conclusion, short-term prophylactic thyrostatic therapy seems to have a protective effect against iodine excess in patients with euthyroid autonomy. However, mild hyperthyroidism could not be prevented in some cases. Probably a combination therapy of thiamazole and perchlorate would be more effective.
In a prospective, randomized study we examined the influence of prophylactic short-term thyrostatic therapy on thyroid iodine metabolism in patients with euthyroid autonomy undergoing elective coronary angiography. From a total of 1177 patients, 51 fulfilled the criteria of euthyroid autonomy before coronary angiography (negative thyrotropin-releasing hormone test, 10-min uptake of at least 1.2%, 99mTc and no elevation of free thyroxine and free triiodothyronine indices) and were randomized into three groups: group 1 (N = 17) received 20mg/day of thiamazole and group 2 (N = 17) received 900 mg/day of sodium perchlorate; thyrostatic therapy was begun on the day before angiography and continued for 14 days; group 3 (N = 17) served as controls without treatment. Parameters of thyroid function-free thyroxine (FT4) index and free triiodothyronine (FT3) index, thyrotropin (TSH) and delta-TSH urine iodine excretion and 99mTc uptake were determined before and 30 days after coronary angiography. At the end of the study the mean FT4 index and FT3 index were elevated significantly in the control group compared with baseline values, but were still within the normal range. In contrast, the mean FT4 index and FT3 index remained unchanged in the treated groups. Four mild cases of hyperthyroidism were observed at the end of the study: two cases in the control group and one case in each of the treated groups. Thyrotropin suppression, urine iodine excretion and 99mTc uptake differed significantly between the treated groups and the control group. In the treated groups TSH suppression, urine iodine excretion and 99mTC uptake remained unchanged 30 days after coronary angiography compared with baseline values. In the control group the degree of TSH suppression and the level of urine iodine excretion increased (about twofold) significantly after coronary angiography, whereas 99mTc uptake decreased significantly (ca. 50%). In conclusion, short-term prophylactic thyrostatic therapy seems to have a protective effect against iodine excess in patients with euthyroid autonomy. However, mild hyperthyroidism could not be prevented in some cases. Probably a combination therapy of thiamazole and perchlorate would be more effective.
Related Concept Videos
 01:25
Hyperthyroidism I: Introduction
 01:20
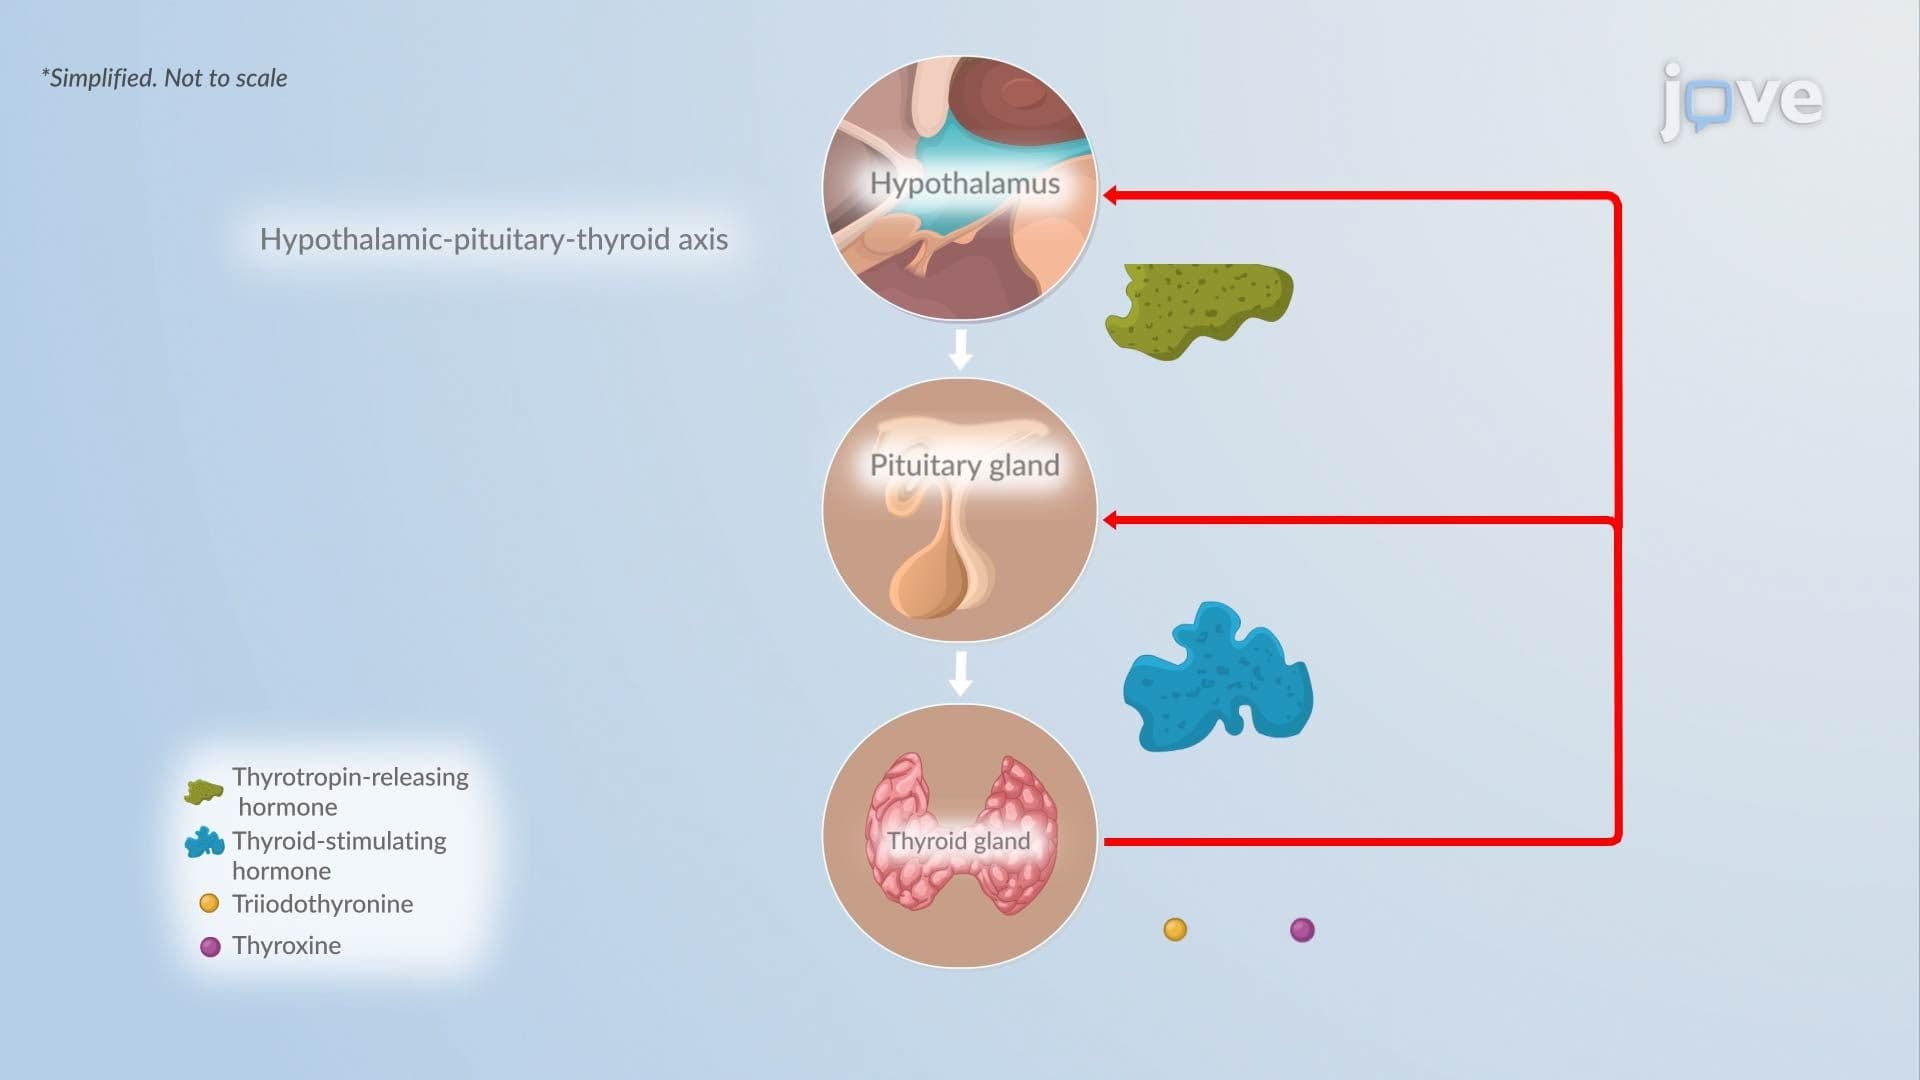
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology
 01:28
Graves' Disease I: Introduction
 01:27
Goiter