Related Experiment Video
Updated: Aug 6, 2026

Murine Prostate Micro-dissection and Surgical Castration
Published on: May 11, 2016
Effects of androgen deprivation on prostate alpha 1-adrenergic receptors
J P Lacey1, C F Donatucci, D T Price
1Department of Surgery (Urology), Duke University Medical Center, Durham, North Carolina 27710, USA.

Objectives:
Benign prostatic hyperplasia (BPH), the most common benign tumor in men, consists of two components-static (enlargement regulated by androgens) and dynamic (smooth muscle contraction through alpha 1-adrenergic receptors [alpha 1-ARs]). Because medical therapy of BPH involves tissue androgen deprivation, we studied the influence of androgen deprivation and replacement on regulation of rat ventral prostate alpha 1-ARs.
Methods:
Prostate weight, alpha 1-AR density, autoradiographic images, histologic features, and cell-specific protein were examined before and after castration and androgen replacement.
Results:
Castration decreases ventral prostate wet weight, a process reversed by testosterone administration. In contrast, there is an apparent increase in alpha 1-AR density (29 +/- 4 versus 65 +/- 6 fmol/mg total protein, mean +/- SEM) after castration, returning to baseline with testosterone replacement; alpha 1-AR density remains constant in control liver membranes. Alpha 1-ARs predominate in stroma throughout androgen deprivation therapy. Epithelially derived cells decrease (83% to 67%) after castration, resulting in a relative doubling in stroma (17% to 33%); the protein content of epithelial and stromal cells remains identical. Therefore, prostate-specific increases in alpha 1-ARs appear to result from relative increases in the ratio of smooth muscle to epithelium after castration rather than from direct upregulation of alpha 1-AR protein.
Conclusions:
Because alpha 1-AR density does not decrease with androgen deprivation, these studies suggest that alpha 1-AR antagonists remain an important component in BPH therapy, even when 5-alpha-reductase inhibitors are utilized.
More Related Videos
 07:25
A Bioluminescent and Fluorescent Orthotopic Syngeneic Murine Model of Androgen-dependent and Castration-resistant Prostate Cancer
Published on: March 6, 2018
 09:49
Isolation of Adipose Derived Regenerative Cells for the Treatment of Erectile Dysfunction Following Radical Prostatectomy
Published on: December 28, 2021
Related Concept Videos
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
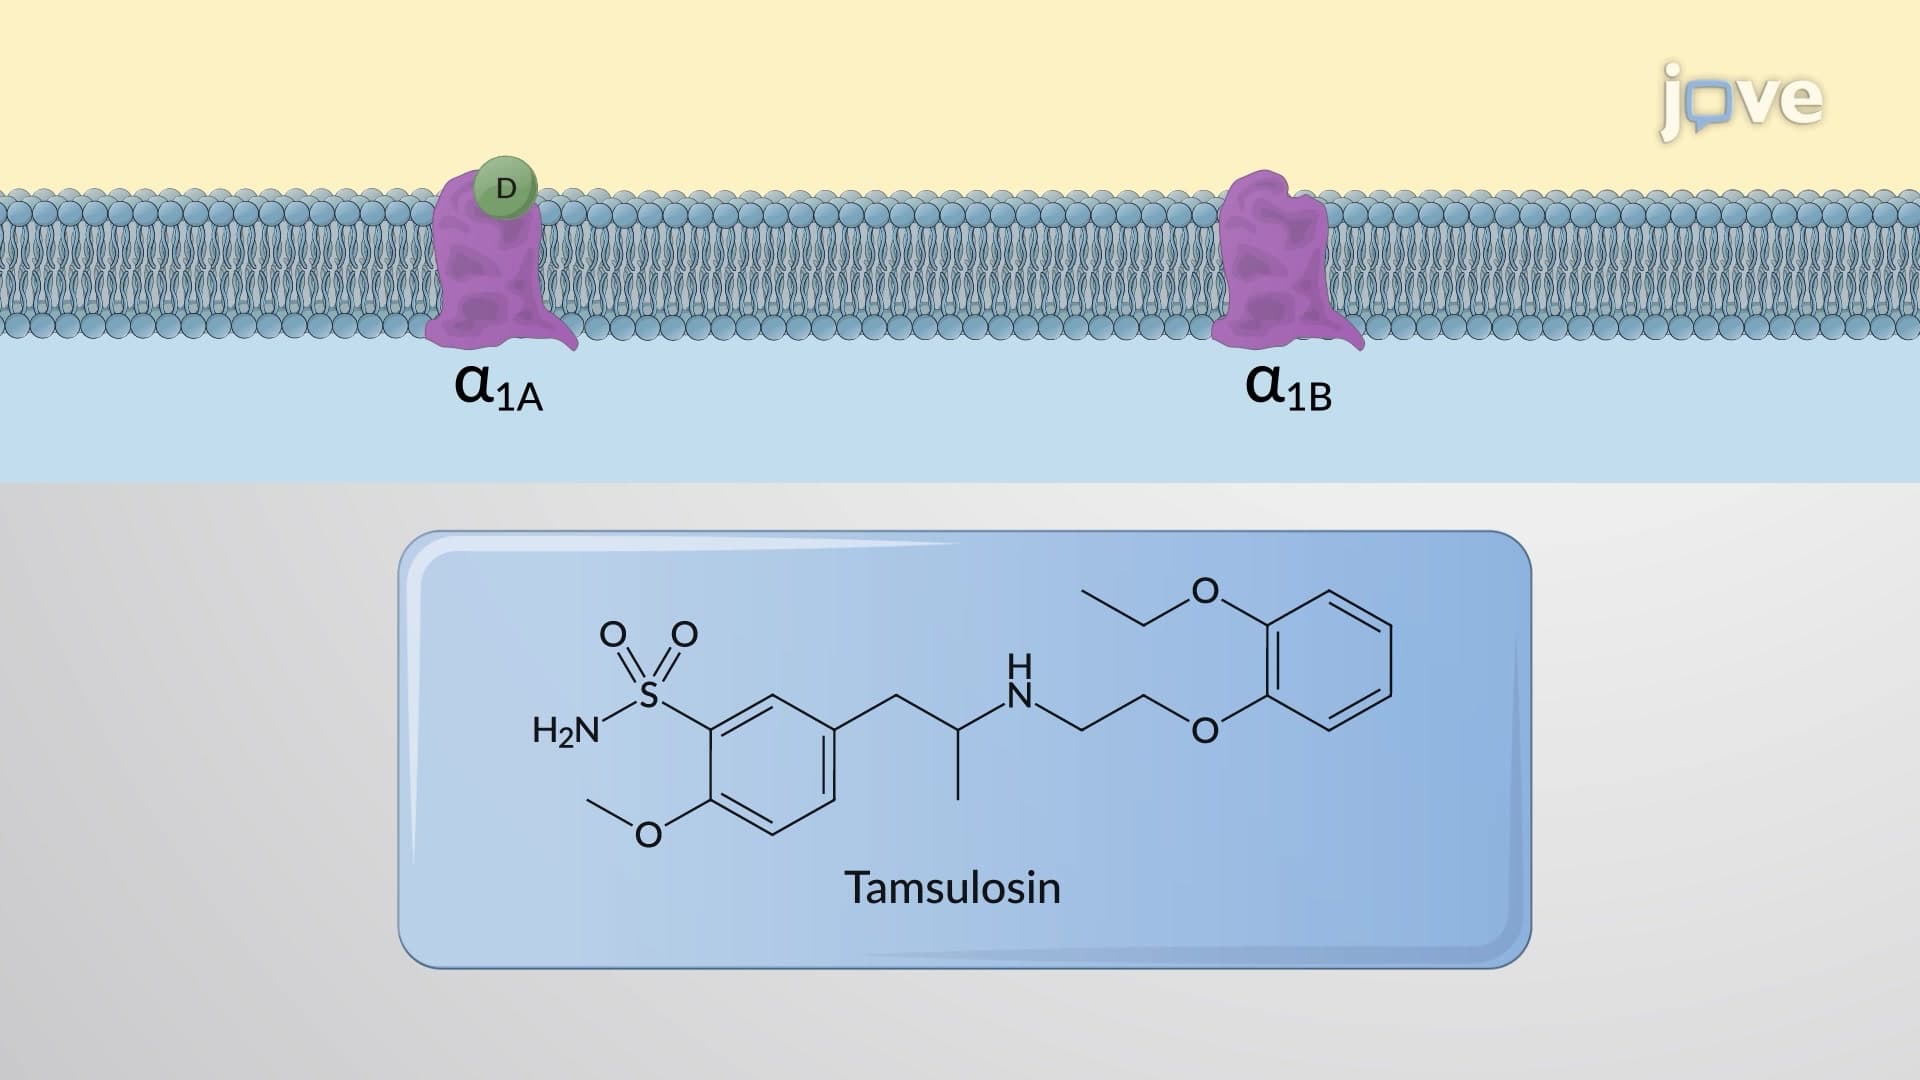
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
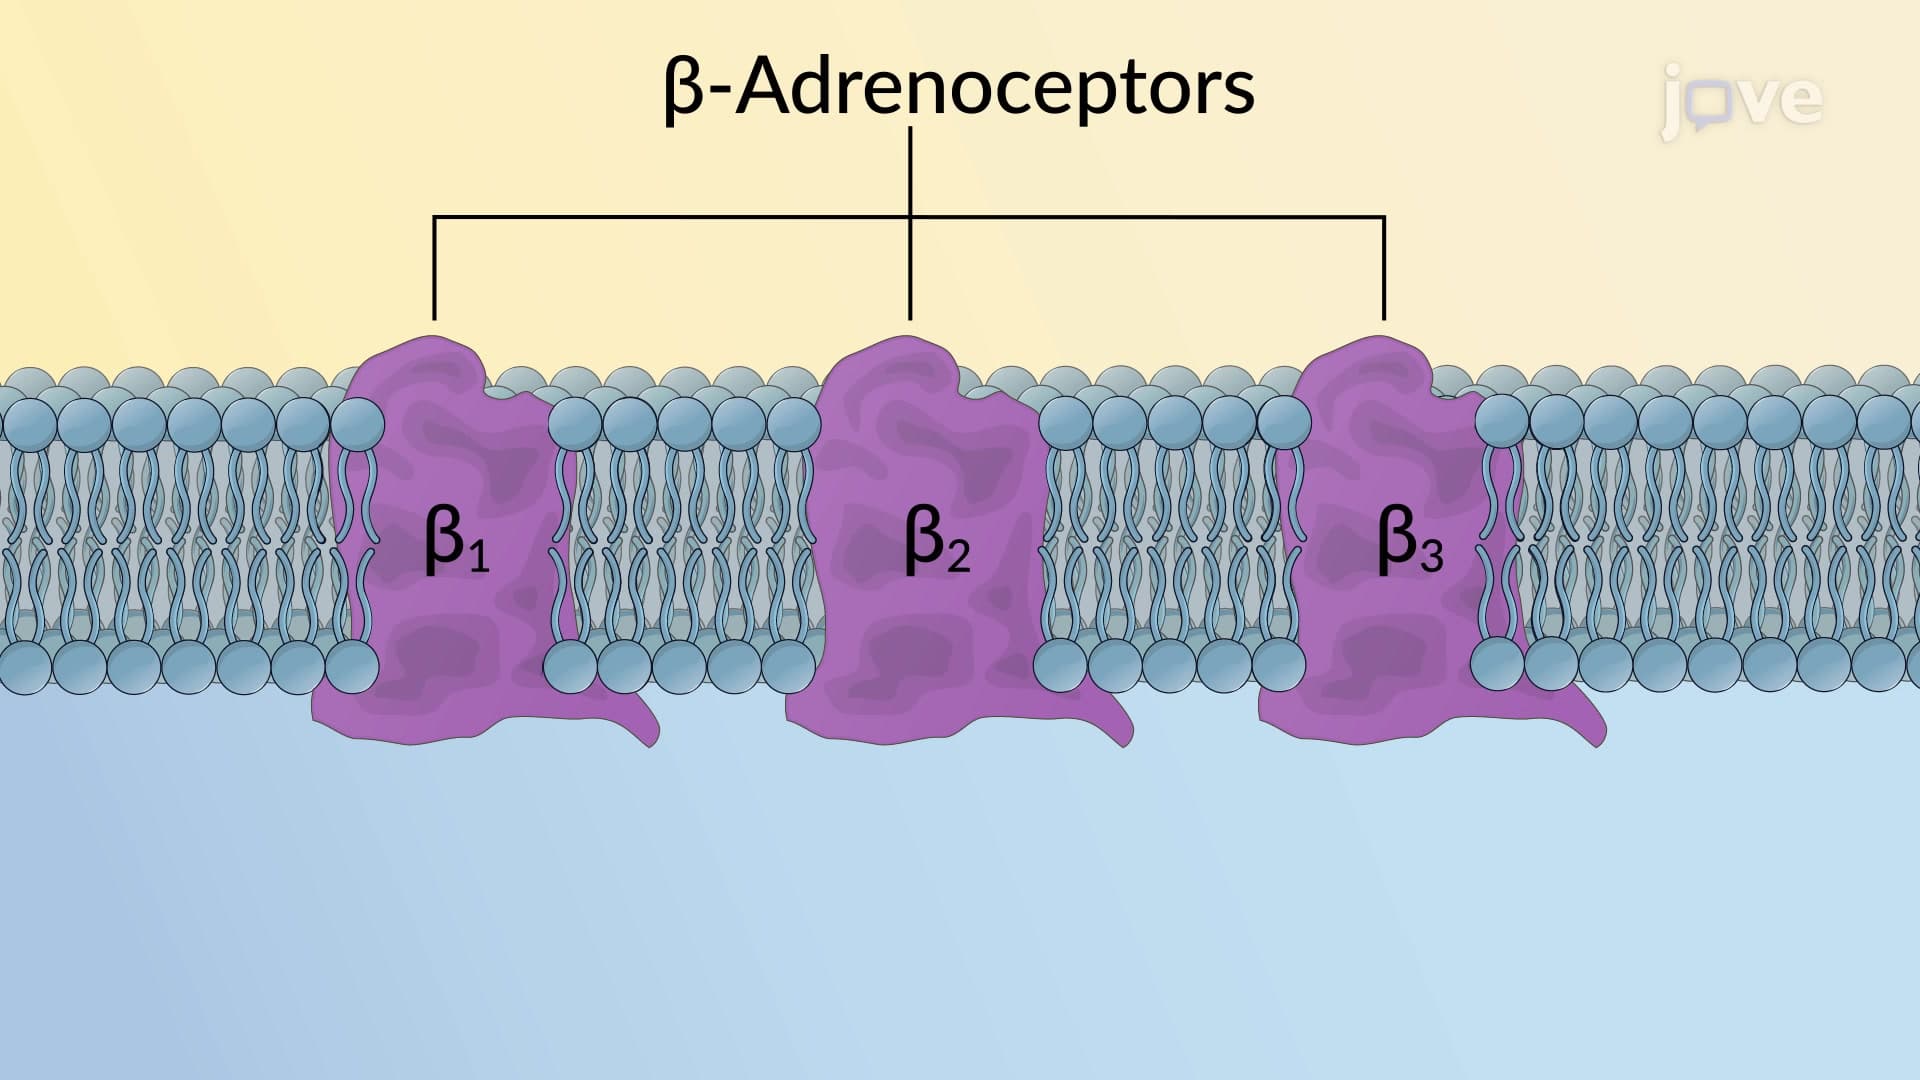
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:30
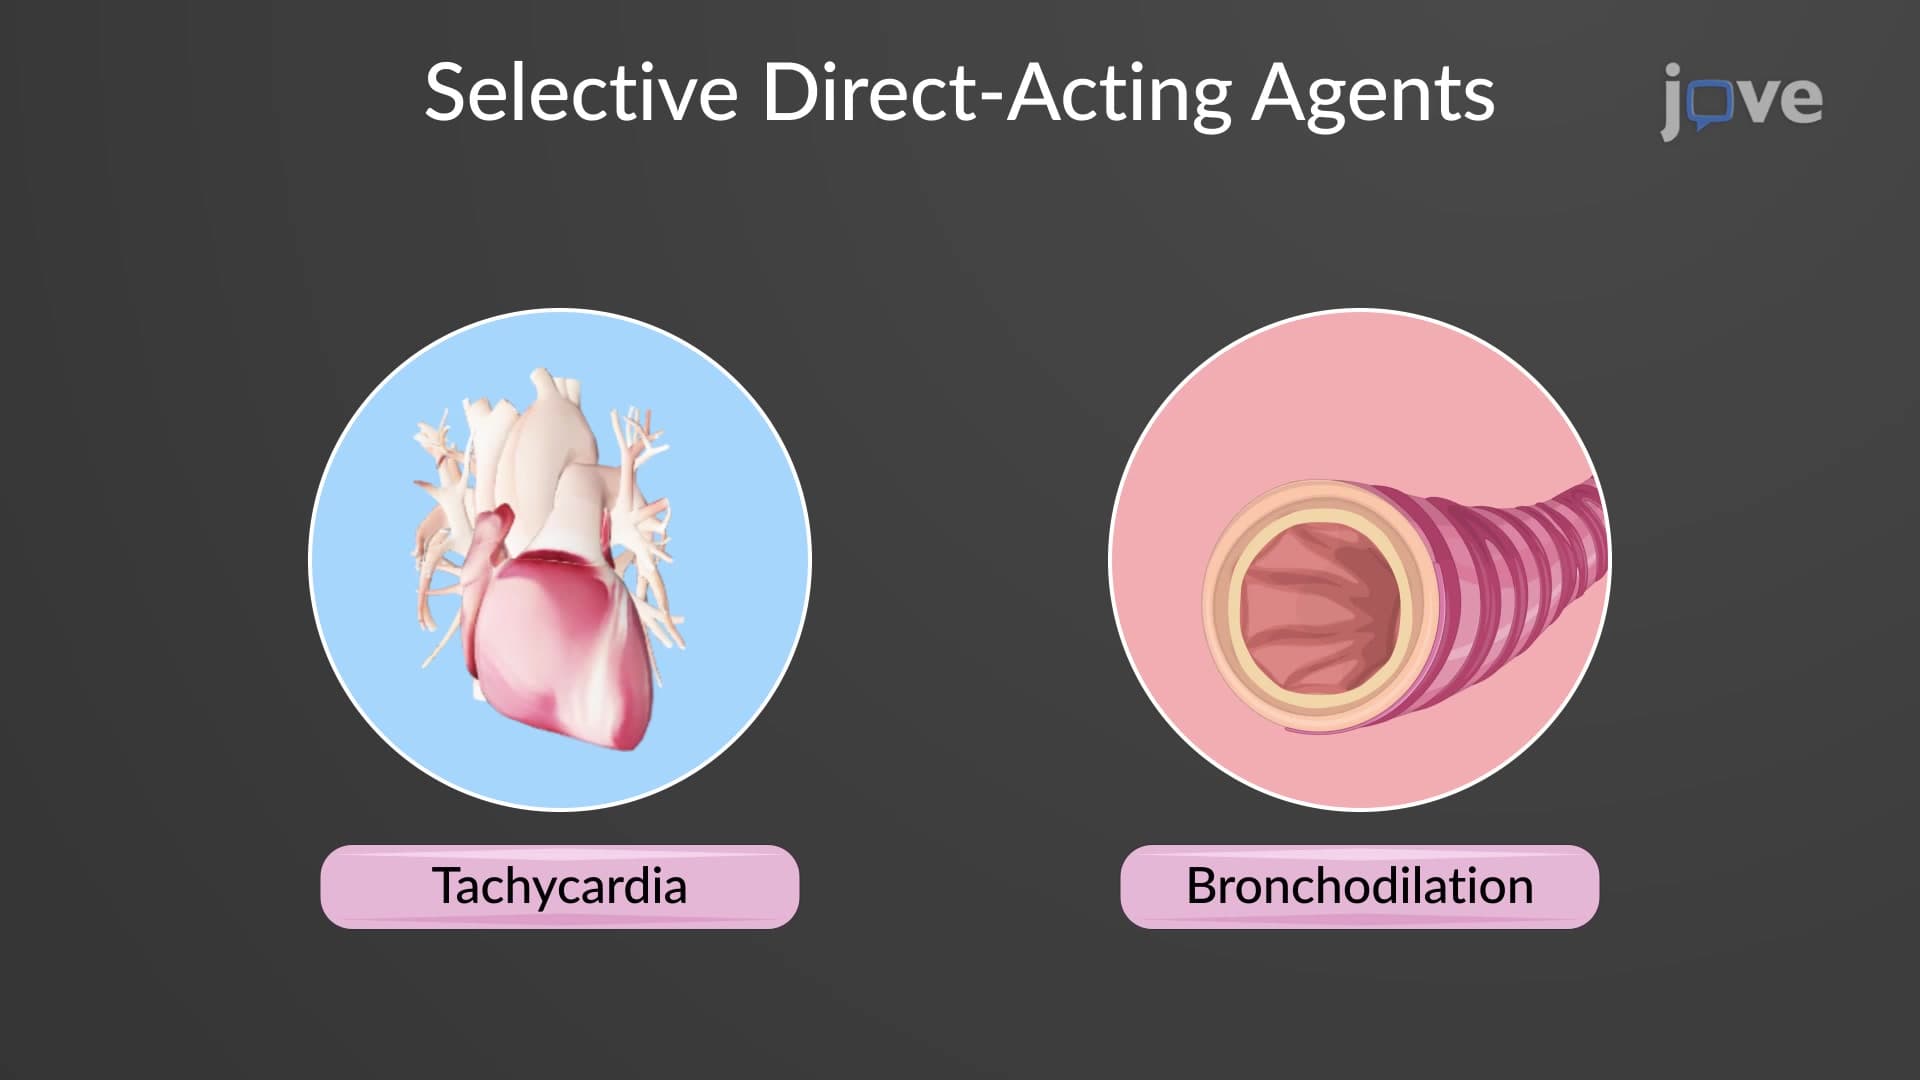
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:17
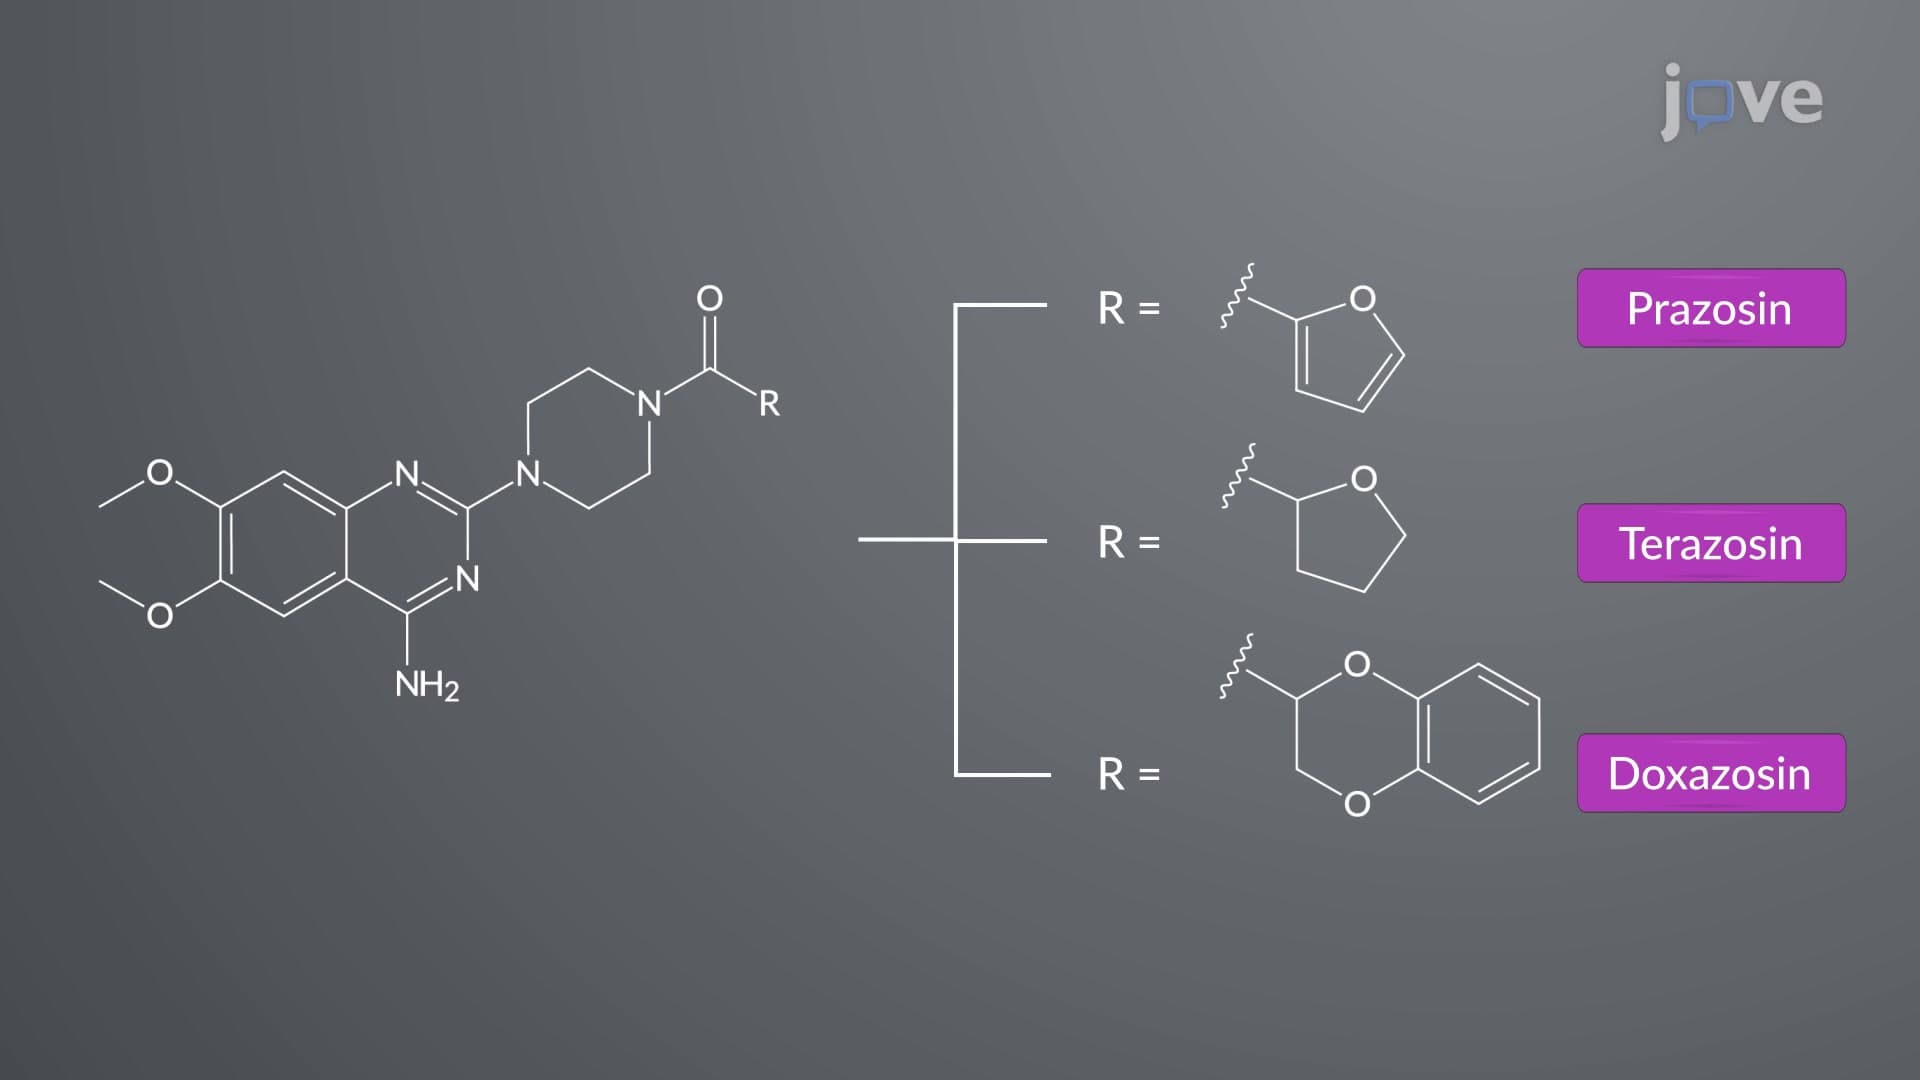
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:22
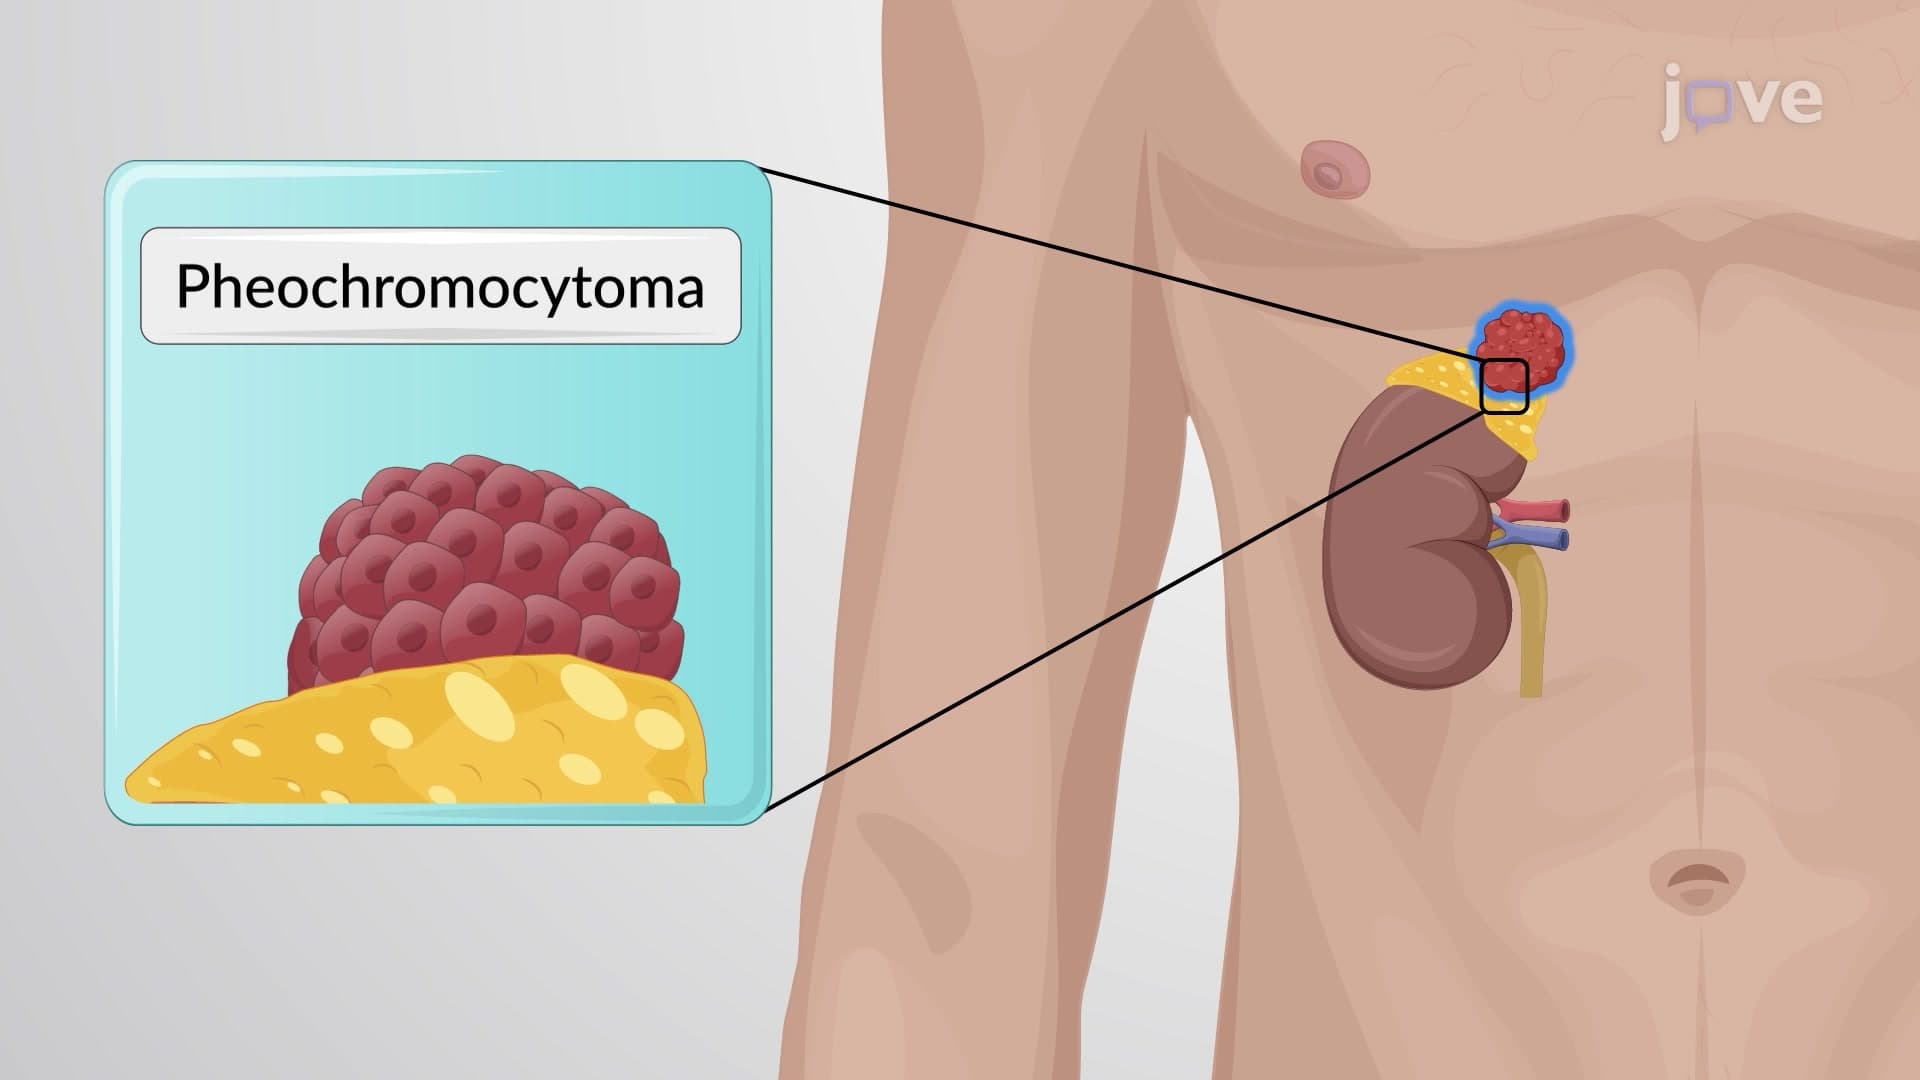
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...