[Dysmenorrhea]
Related Experiment Video
Updated: Nov 4, 2026
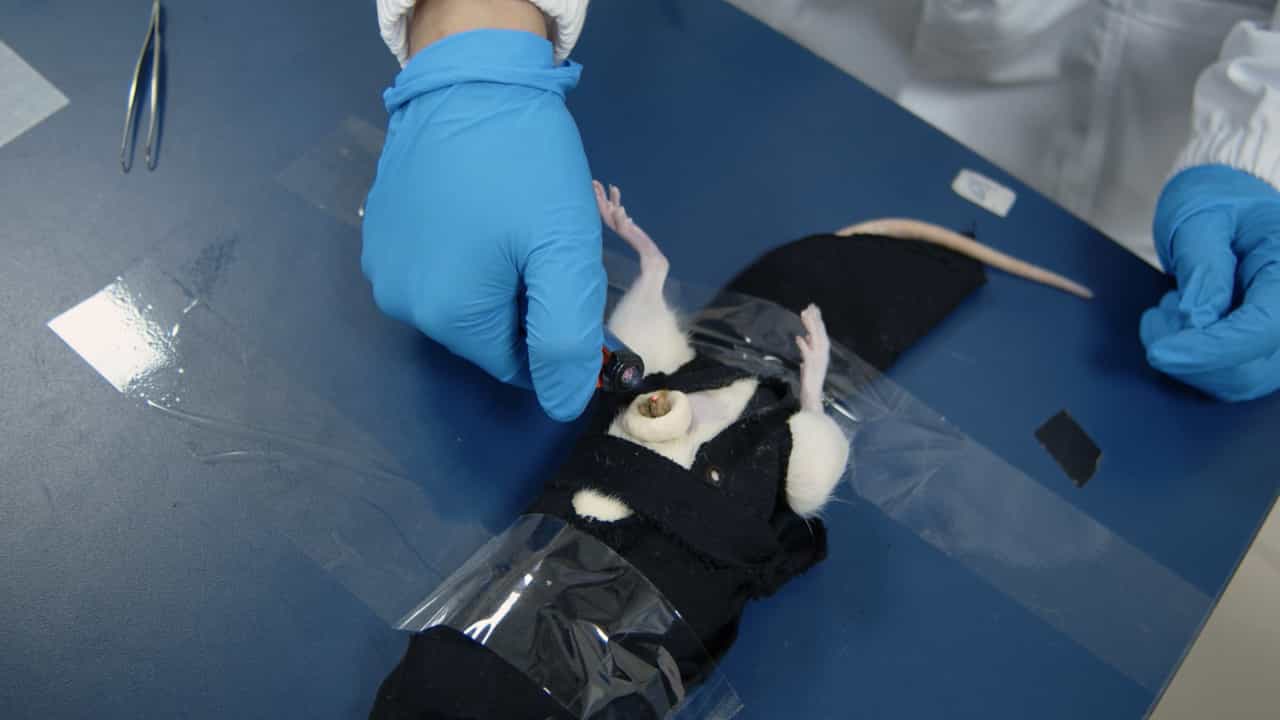
Herbs-Partitioned Moxibustion on the Navel in a Rat Model of Primary Dysmenorrhea with Cold Coagulation and Blood Stasis
Published on: October 4, 2024
1Seminar für Gynäkologie, Universität Basel.

Abstract:
Primary dysmenorrhea is very frequent in ovulating women; it can even become a disease. In some cases, but not always, it is preceded by premenstrual tensions. Secondary dysmenorrhoea should be clearly differentiated, because it is a symptom of uterine abnormalities or adnexal diseases, whereas primary dysmenorrhoea is an entity in itself. The most frequent cause of secondary dysmenorrhoea is endometriosis. Dysmenorrhea membranacea is a rare event, but should not be forgotten. Primary dysmenorrhea involves the entire organism and the psyche of the suffering woman. The problem is its cyclic repetition and everlasting painful expectation. The pathogenesis is more clarified now but nevertheless not yet completely investigated. There is evidence that under the dominating role of sexual hormones paracrine sequelae are occurring, which result in a local increase of prostaglandins. The most important factor is the rhythmic ischemic reaction due to vasoconstriction in small arteries of the uterine wall, causing excruciating pains at times. The treatment is different whether or not children are immediately desired. Oral contraception and progestogens are useful when given days before the onset of menstruation. If the ovulatory cycle should be maintained, the drugs of choice are non-steroidal antiinflammatory preparations, among them naproxen and ibuprofen the most effective. Since those drugs exert side-effects when administered over a long period of time, alternatives must be available. The most appropriate ones are ASS, magnesium, calcium antagonists or tocolytic agents. Few new approaches to further alternative therapies (neuro-stimulation) could not provide a decrease of the uterine contractility in cases of primary dysmenorrhea.

Related Concept Videos
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:24
Disorders of the Female Reproductive System
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...
 01:28
Menopause
 01:19
Secretory Phase
Following ovulation, the corpus luteum, a temporary endocrine structure, produces progesterone and estrogens. These hormones stimulate the growth and coiling of endometrial...