Related Experiment Video
Updated: Oct 13, 2026
Measurement of Heme Synthesis Levels in Mammalian Cells
Published on: July 9, 2015
Genetic and nongenetic factors for moderate hyperhomocyst(e)inemia
1Department of Pediatrics, Rush Medical College and Rush-Presbyterian St. Luke's Medical Center, Chicago, IL 60612, USA.

Insights
Assessing vascular disease risk requires demonstrating overt hyperhomocyst(e)inemia. Identifying genetic defects is crucial alongside plasma homocyst(e)ine levels for accurate risk evaluation.
Area of Science:
- Biochemistry
- Genetics
- Cardiovascular Medicine
Background:
- Hyperhomocysteinemia is linked to vascular disease.
- Genetic defects can cause persistent hyperhomocysteinemia.
- Nongenetic factors can influence hyperhomocysteinemia expression.
Purpose of the Study:
- To evaluate the risk of vascular disease associated with hyperhomocysteinemia.
- To emphasize the importance of identifying genetic defects in hyperhomocysteinemia assessment.
- To explore methods for evaluating hyperhomocysteinemia in the context of vascular disease risk.
Main Methods:
- Demonstrating overt hyperhomocysteinemia.
- Investigating genetic defects (e.g., cystathionine synthase deficiency, methylenetetrahydrofolate reductase).
- Utilizing post-methionine homocyst(e)ine determination when genetic defects are not found.
Main Results:
- Clinical vascular disease in nonhomocystinuric subjects requires prolonged hyperhomocysteinemia, often linked to genetic defects.
- Plasma homocyst(e)ine concentration alone may be insufficient due to nongenetic factor interference.
- Genetic analysis is as vital as plasma homocyst(e)ine measurement for risk assessment.
Conclusions:
- Accurate assessment of hyperhomocyst(e)inemia-associated vascular disease risk necessitates identifying underlying genetic defects.
- Post-methionine homocyst(e)ine levels can identify genetic susceptibility when environmental factors are controlled.
- A combined approach of genetic screening and biochemical analysis is recommended for comprehensive risk evaluation.
Abstract:
To assess the risk for homocyst(e)ine-associated vascular disease, overt hyperhomocyst(e)inemia should be demonstrated. In nonhomocystinuric subjects, clinical vascular disease must have developed after 40 or more years of persistent hyperhomocyst(e)inemia which may not be present without a genetic defect(s). Nongenetic factors, however, may amplify or mask phenotypic expression of a genetic defect, causing difficulties for the evaluation of hyperhomocyst(e)inemia based on plasma homocyst(e)ine concentration alone. Therefore, the search for genetic defects seems as important as the determination of plasma homocyst(e)ine concentration in evaluating the relationship between hyperhomocyst(e)inemia and the development of vascular disease. If genetic defect, such as heterozygous cystathionine synthase deficiency or thermolabile methylenetetrahydrofolate reductase is not detected, post-methionine homocyst(e)ine determination is a suitable means to identify genetic susceptibility to hyperhomocyst(e)inemia when the environmental factors are similar in the control and study groups.


Related Concept Videos
 02:19
Multiple Allele Traits
 01:37
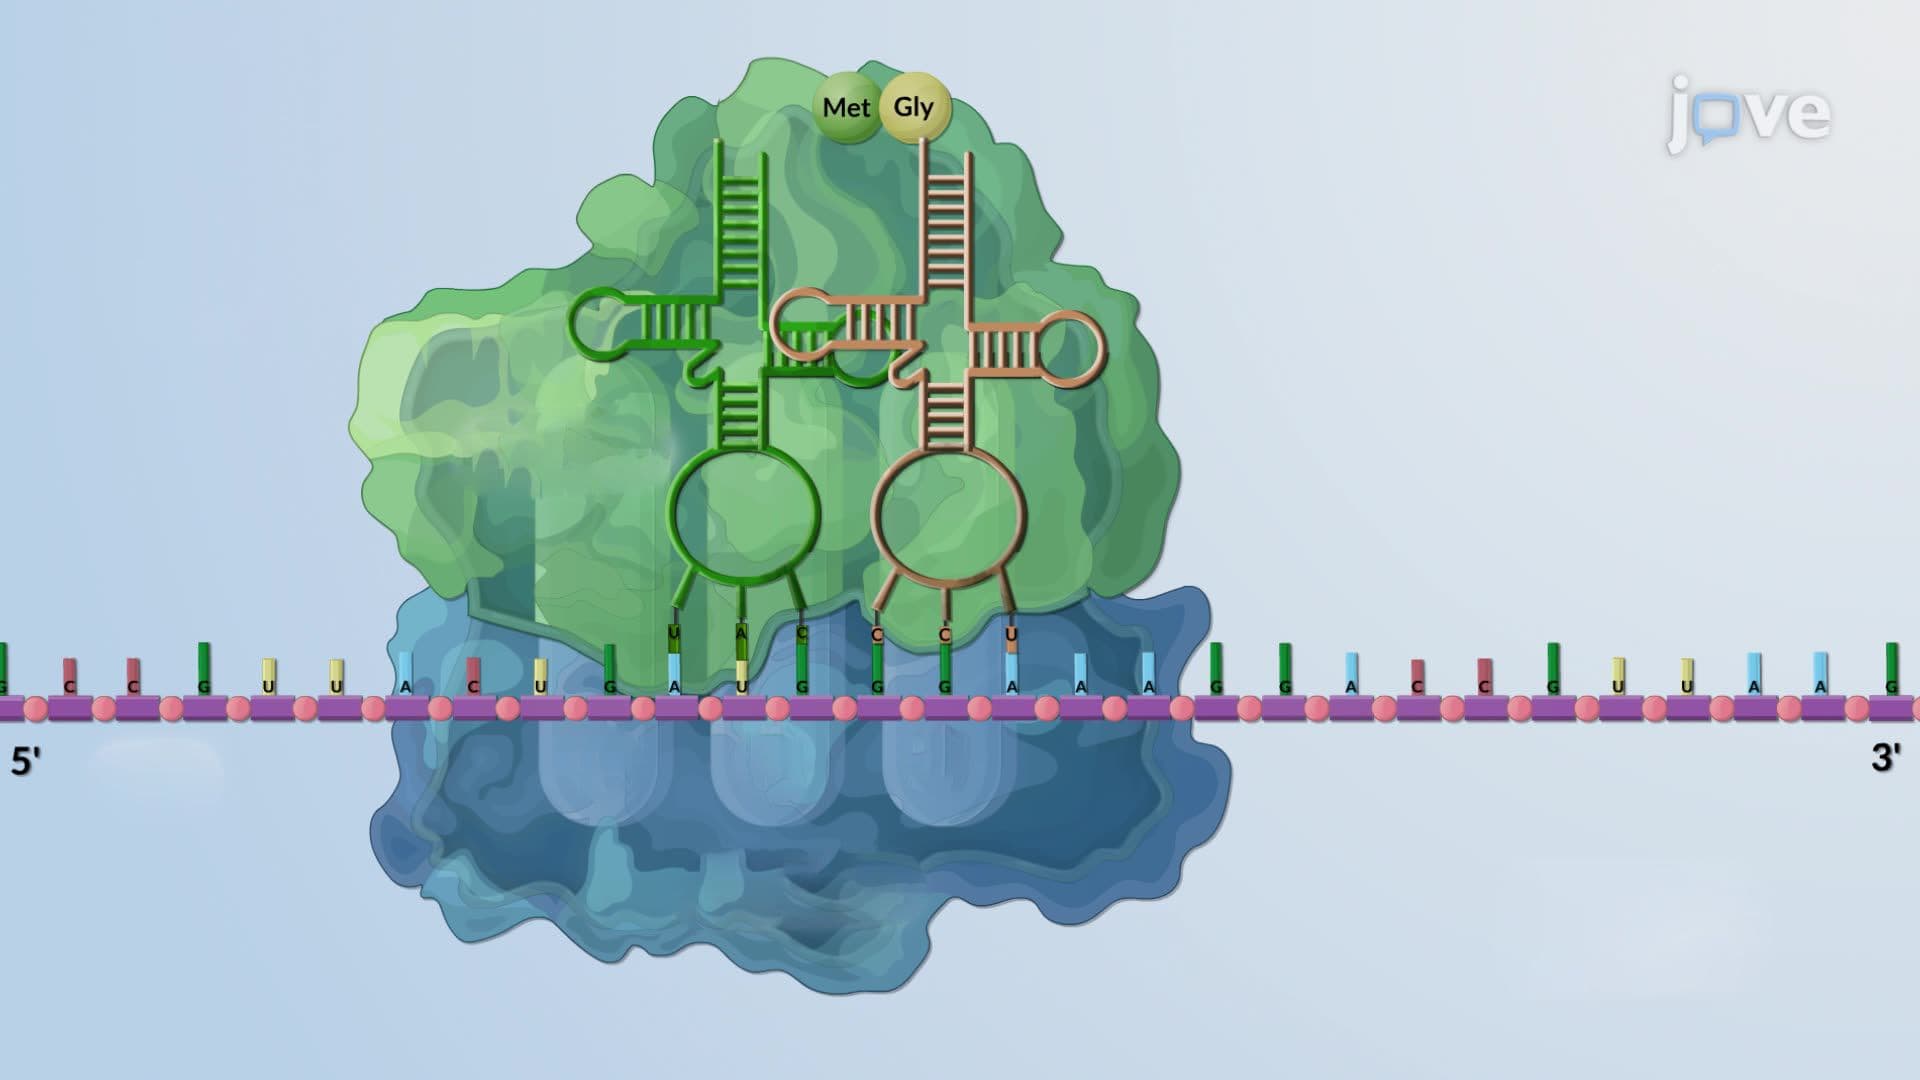
Translation
 01:24
Factors Affecting Erythropoiesis
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
 01:28
Human Genetics
The complex relationship between genetics and psychology is observable through common biological components such...
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...