Related Experiment Video
Updated: Aug 13, 2026
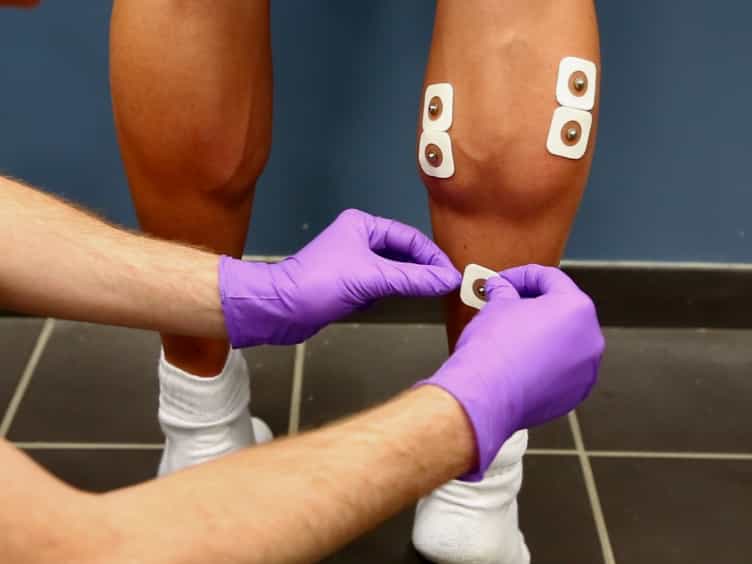

Assessment of Neuromuscular Function Using Percutaneous Electrical Nerve Stimulation
Published on: September 13, 2015
[Value of monitoring muscle relaxation]

Indication:
Sensitivity to neuromuscular blocking agents differs between individuals, and residual neuromuscular blockade is a common postoperative problem. Clinical signs such as head lift, hand grip, and inspiratory force are suitable means of showing residual blockade. However, an awake and cooperative patient is needed. Therefore, in clinical practice it is advantageous to use the responses evoked by a nerve stimulator.
Sites Of Nerve Stimulation And Differing Muscle Response:
In clinical anesthesia, the ulnar nerve is the most popular site. The response is evaluated by feeling the contractions of the adductor pollicis muscle. This muscle shows a slow onset of blockade and is highly sensitive to neuromuscular blocking agents. Therefore, the chance of overdosing the patient is decreased and during recovery additional safety is gained, as it can be safely assumed that at the time of normalization of the thumb twitches no residual blockade exists in the diaphragm or larynx. On the other hand, absent twitches of the adductor pollicis using train-of-four stimulation do not preclude intraoperative activity of more resistant muscles such as the diaphragm.
Recording Of Evoked Responses And Patterns Of Nerve Stimulation:
In clinical anesthesia, tactile evaluation of the muscle response is the usual method. Mechanomyography (Myograph) with a force transducer is used as the reference standard. This method, as well as the measurement of acceleration (Accelograph, TOF-Guard) and electromyography (Relaxograph) are mainly tools for teaching and research. Different patterns of nerve stimulation are used: during induction, single-twitch stimulation at 1Hz; during profound blockade, post-tetanic count stimulation (PTC); surgical blockade is evaluated using train-of-four stimulation (TOF); and recovery is followed by double-burst stimulation (DBS). Using simple train-of-four stimulation during recovery, a device is needed with a registering capacity to accurately determine a TOF-ratio > 0.7.
Conclusions:
Relaxometry allows monitoring of neuromuscular function independently of the patient's cooperation, and should be standard. In the intensive care unit, relaxometry helps to minimize the risk of overdosing. However, muscular weakness can persist despite adequate drug dosage. Relaxometry is only part one of a concept. Intubating and operating conditions are highly dependent on the depth of anesthesia, and the risk of postoperative residual blockade can be minimized by using short or medium action drugs.

Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic drugs,...
 01:29
Relaxation of Skeletal Muscles
When an action potential reaches the axon terminal, it depolarizes the membrane and opens voltage-gated sodium channels. Sodium ions enter the cell, further depolarizing the presynaptic membrane. This depolarization causes voltage-gated calcium channels to open.
 01:22
Muscle Stimulation Frequency
Wave summation
At low firing rates, motor neurons induce individual twitch contractions in muscle fibers. These twitches...