Related Experiment Video
Updated: Aug 19, 2026


Improved Renal Denervation Mitigated Hypertension Induced by Angiotensin II Infusion
Published on: May 26, 2022
Correlates of controlled hypertension in indigent, inner-city hypertensive patients
J S Ahluwalia1, S E McNagny, K J Rask
1Department of Medicine, Emory University School of Medicine, Atlanta, GA 30303, USA.

Insights
Access to regular care, insurance, and affordable medications are key to controlling hypertension in minority populations. Addressing cost barriers and ensuring consistent healthcare access can improve blood pressure management.
Area of Science:
- Cardiology
- Public Health
- Health Services Research
Background:
- Hypertension remains a significant public health challenge, particularly in minority and underserved populations.
- Effective blood pressure (BP) control is crucial for reducing cardiovascular disease morbidity and mortality.
- Identifying factors associated with controlled hypertension is essential for targeted interventions.
Purpose of the Study:
- To identify correlates of controlled hypertension among treated hypertensive patients in a predominantly minority, urban population.
- To understand the role of healthcare access, medication affordability, and insurance in BP management.
Main Methods:
- A case-control study was conducted in an urban public hospital setting.
- Patients with controlled hypertension (systolic blood pressure [SBP] ≤140 mm Hg, diastolic blood pressure [DBP] ≤90 mm Hg) were compared to those with uncontrolled hypertension (SBP ≥180 mm Hg or DBP ≥110 mm Hg).
- Logistic regression analysis adjusted for demographic factors to identify significant correlates of controlled hypertension.
Main Results:
- Controlled hypertension was significantly associated with having a regular source of care (OR 7.93) and recent physician visits (OR 4.81).
- Reporting that medication costs were not a deterrent (OR 3.63) and having insurance (OR 2.15) were also linked to better BP control.
- Medicaid coverage was associated with fewer reported cost barriers for medications and physician visits compared to the uninsured.
Conclusions:
- The absence of out-of-pocket expenses for medications and care under Medicaid may significantly contribute to blood pressure control.
- Improving access to regular healthcare and increasing sensitivity to medication costs are vital for enhancing BP control in indigent, inner-city populations.
- Targeted strategies focusing on healthcare access and cost reduction can improve hypertension management in vulnerable groups.
Objective:
To identify correlates of controlled hypertension in a largely minority population of treated hypertensive patients.
Design:
Case-control study.
Setting:
Urban, public hospital.
Patients:
A consecutive sample of patients who were aware of their diagnosis of hypertension for at least 1 month and had previously filled an antihypertensive prescription. Control patients had a systolic blood pressure (SBP) < or = 140 mm Hg and diastolic blood pressure (DBP) < or = 90 mm Hg, and case patients had a SBP > or = 180 mm Hg or DBP > or = 110 mm Hg.
Measurements And Main Results:
Control subjects had a mean blood pressure (BP) of 130/80 mm Hg and case subjects had a mean BP of 193/106 mm Hg. Baseline demographic characteristics between the 88 case and the 133 control subjects were not significantly different. In a logistic regression model, after adjusting for age, gender, race, education, owning a telephone, and family income, controlled hypertension was associated with having a regular source of care (odds ratio [OR] 7.93; 95% confidence interval [CI] 3.86, 16.29), having been to a doctor in the previous 6 months (OR 4.81; 1.14, 20.31), reporting that cost was not a deterrent to buying their antihypertensive medication (OR 3.63; 1.59, 8.28), and having insurance (OR 2.15; 1.02, 4.52). Being compliant with antihypertensive medication regimens was of borderline significance (OR 1.96; 0.99, 3.88). A secondary analysis found that patients with Medicaid coverage were significantly less likely than the uninsured to report cost as a barrier to purchasing antihypertensive medications and seeing a physician.
Conclusions:
The absence of out-of-pocket expenditures under Medicaid for medications and physician care may contribute significantly to BP control. Improved access to a regular source of care and increased sensitivity to medication costs for all patients may lead to improved BP control in an indigent, inner-city population.

Related Concept Videos
 01:30
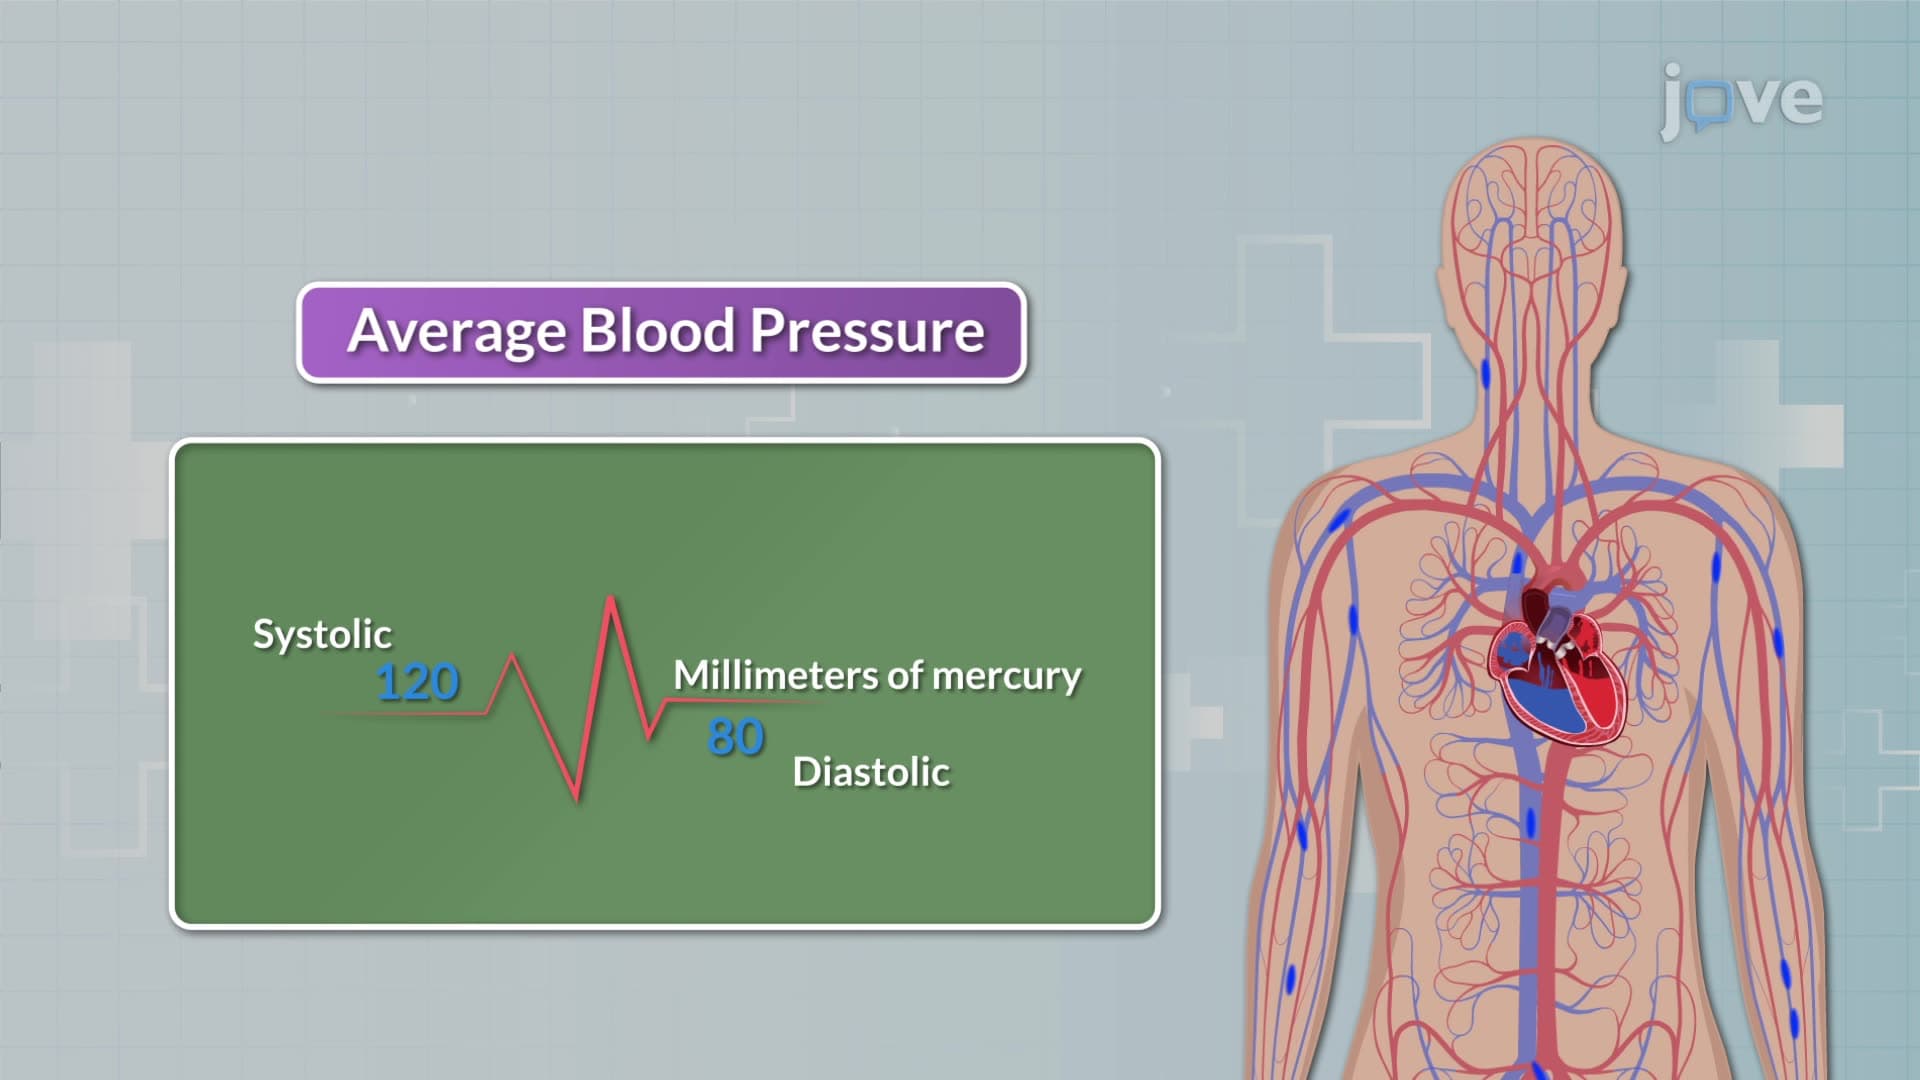
Blood Pressure
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Hypertension I: Introduction
 01:29
Hypertension II: Pathophysiology
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies