[Pulmonary complications in diabetes mellitus]
Related Experiment Videos

Abstract:
The lung is not considered a target organ in diabetes mellitus. In English language literature there are many papers showing the opposite. Many studies demonstrated a thickened alveolar epithelial and pulmonary capillary basal lamina and a reduced lung elasticity, others showed that these histopathological alterations developed into functional abnormalities: reduced lung volumes, reduced pulmonary diffusion capacity and elastic recoil. The pathogenesis is currently thought to involve the nonenzymatic glycosylation (NEG) of tissue proteins inducing an alteration in connective tissue. In patients with diabetic autonomic neuropathy there is an abnormal basal airway tone due to an alteration in vagal pathways: these patients have a reduced bronchial reactivity and bronchodilatation. Diabetic patients have an increased propensity to acquire infections, in particular tuberculosis and pulmonary fungal diseases (coccidioidomycosis, aspergillosis and mucormycosis). The frequency of occurrence of tuberculosis is reported to be four times than in non diabetics, there is a predilection for the lower lobes and the disease is more aggressive in poorly controlled diabetes mellitus. Pulmonary mucormycosis is an infection caused by Phycomycetes, the fungus has the propensity to invade vascular structures giving hemoptysis and leading to a high mortality unless diagnosed promptly. The mechanism for the increased susceptibility to infection is due to an alteration in chemotactic, phagocytic and bactericidal activity of polymorphonuclear leukocytes.
Related Concept Videos
 01:22
Complications of Diabetes Mellitus
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:27
Diabetic Retinopathy
 01:15
Diabetes: Symptoms, Diagnosis, and Complications
 01:18
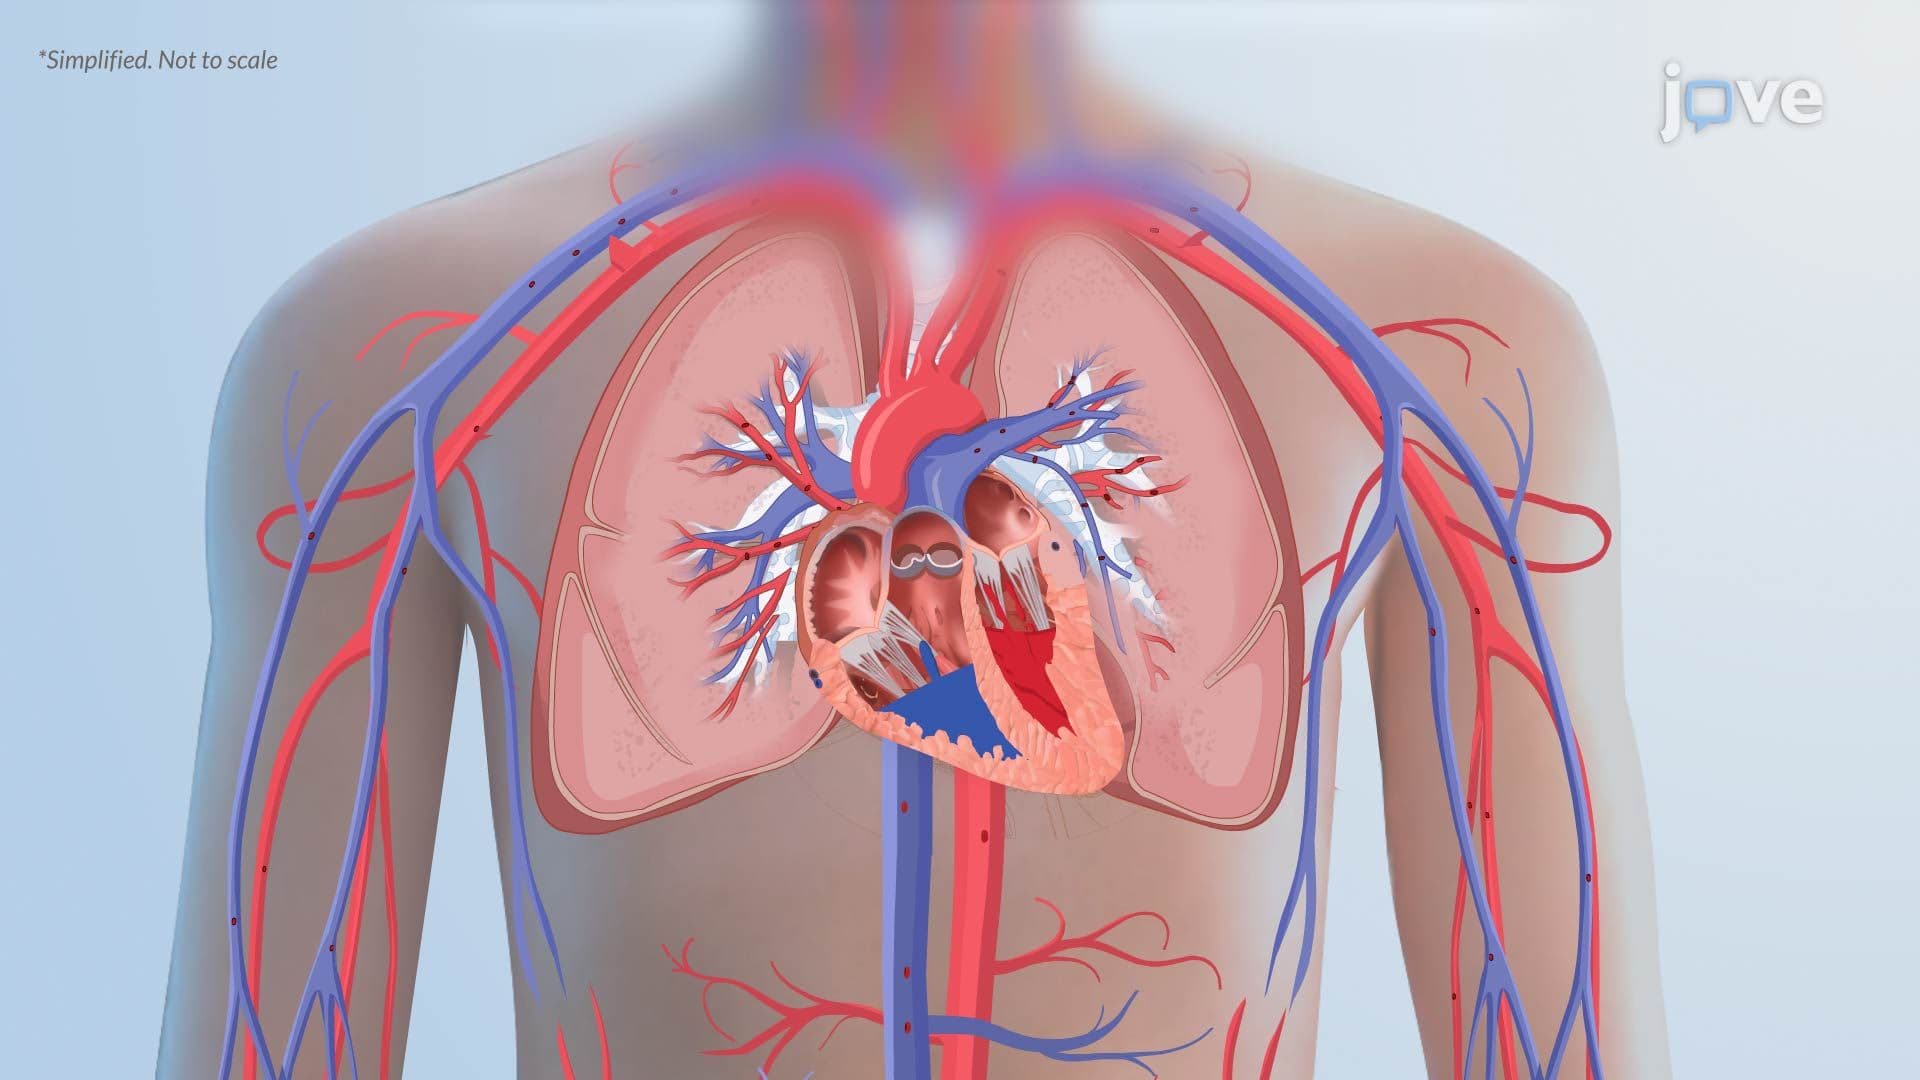
Pulmonary Edema II: Pathophysiology
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations