Related Experiment Video
Updated: Oct 9, 2026
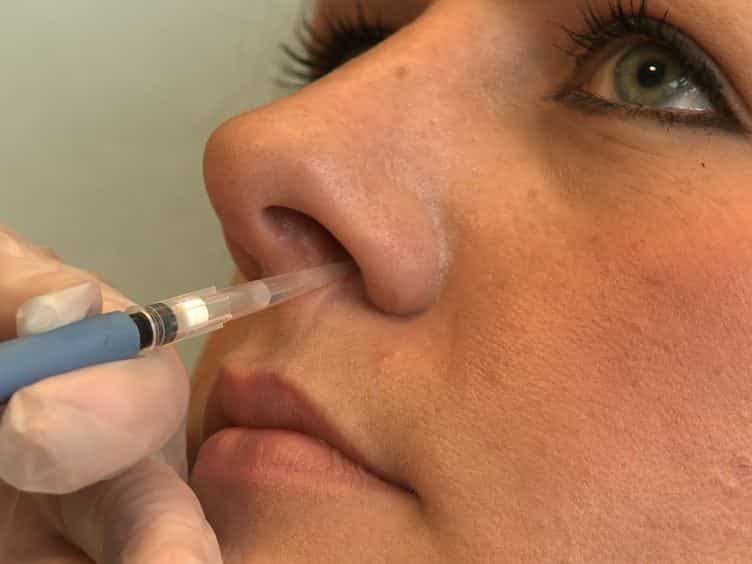
Experimental Human Pneumococcal Carriage
Published on: February 15, 2013
The epidemiology of community-acquired pneumonia among hospitalized adults
A Porath1, F Schlaeffer, D Lieberman
1Division of Internal Medicine, Soroka Medical Center, Faculty of the Health Sciences, Ben-Gurion University of the Negev, Beer-Sheva, Israel.

Objective:
To identify and characterize the aetiological agents of community-acquired pneumonia (CAP) among hospitalized patients, as an aid in therapeutic decision-making.
Method:
A prospective 1 year study of all patients hospitalized with CAP in the Negev region of Israel. The aetiology was determined by blood and pleural fluid cultures, and specific serological testing for pathogenic agents. Eighty-nine percent of the patients underwent follow-up for a month after discharge.
Results:
The study included 346 patients (53% males, mean age 49.3 +/- 19.5, range 17-94). A single aetiologic agent was identified in 146 patients (42.2%), multiple agents were found in 133 (38.4%), and no agent was identified in 67 (19.4%). Among the common pathogens were Pneumococcus sp. in 148 patients (42.8%). Mycoplasma pneumoniae (101, 29.2%), Chlamydia pneumoniae (62, 17.9%), Legionella sp. (56, 16.2%), viruses (35, 10.1%), Coxiella burnetti (20, 5.8%). Haemophilus influenzae (19, 5.5%), and other bacteria (21, 6.1%). Approximately 70% of the patients infected with M. pneumoniae and C. burnetti were younger than 45 years (P < 0.05). In contrast, about 50% of the patients with C. pneumoniae (TWAR) were over the age of 65 (P = 0.03). The presence of comorbidity was associated with a greater frequency of bacterial aetiologies (57% vs. 44%, P = 0.02), and fewer infections with M. pneumoniae (15% vs. 36%, P = 0.0004), or C. burnetii (2% vs. 8%, P = 0.02). Specific causative agents were associated with specific seasons: viruses between December and April (P = 0.03), and Legionella sp. from July to October (P = 0.003). In contrast, no seasonal variation was associated with pneumococcus, M. pneumoniae, or C. pneumoniae (TWAR).
Conclusions:
Patients are hospitalized with CAP throughout the year. Since the pathogen is usually unknown at hospitalization, epidemiological data is important for choosing medication. The findings of this study point to the importance of macrolides alone or in combination with cephalosporins, as the treatment of choice for patients in our region.
More Related Videos
 11:32
Following in Real Time the Impact of Pneumococcal Virulence Factors in an Acute Mouse Pneumonia Model Using Bioluminescent Bacteria
Published on: February 23, 2014
 12:21
A Mouse Model for the Transition of Streptococcus pneumoniae from Colonizer to Pathogen upon Viral Co-Infection Recapitulates Age-Exacerbated Illness
Published on: September 28, 2022
Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:30
Pneumonia III: Complications and Assessment
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:14
Atypical Pneumonia
 01:29
Pneumonia I: Introduction