Related Experiment Video
Updated: Aug 14, 2026
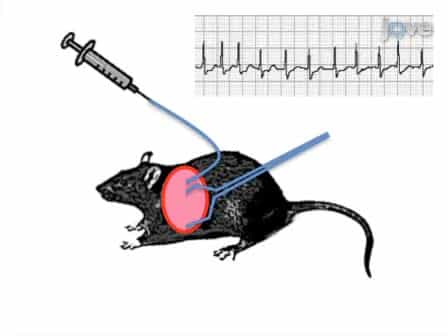

Methods for ECG Evaluation of Indicators of Cardiac Risk, and Susceptibility to Aconitine-induced Arrhythmias in Rats Following Status Epilepticus
Published on: April 5, 2011
Cardiac manifestations of acute carbamate and organophosphate poisoning
A M Saadeh1, N A Farsakh, M K al-Ali
1Princess Basma Teaching Hospital, Faculty of Medicine, Jordan University of Science, Irbid, Jordan.

Insights
Cardiac complications are frequent in organophosphate and carbamate poisoning, with ECG abnormalities common. Prompt intensive care and atropine can reduce mortality from these poisonings.
Area of Science:
- Toxicology
- Cardiology
- Critical Care Medicine
Background:
- Organophosphate and carbamate poisoning are significant public health concerns.
- Cardiac complications can arise from these poisonings, impacting patient outcomes.
- Understanding the frequency and nature of these cardiac issues is crucial for effective management.
Purpose of the Study:
- To investigate the incidence, extent, and underlying mechanisms of cardiac complications in organophosphate and carbamate poisoning.
- To identify predisposing factors for cardiac involvement in poisoned patients.
Main Methods:
- A retrospective study was conducted.
- Data were collected from 46 adult patients admitted to a medical intensive care unit (MICU) over five years.
- Patients diagnosed with organophosphate or carbamate poisoning were included.
Main Results:
- Cardiac complications occurred in 67% of patients, including non-cardiogenic pulmonary edema (43%) and arrhythmias (24%).
- Electrocardiographic abnormalities were prevalent, with prolonged Q-Tc interval (67%) and ST-T changes (41%) noted.
- Hypotension (17%) and hypertension (22%) were observed, with 17% requiring respiratory support. In-hospital mortality was 4% due to ventricular fibrillation.
Conclusions:
- Cardiac complications are common in organophosphate and carbamate poisoning, especially within the initial hours.
- Hypoxemia, acidosis, and electrolyte imbalances are key predisposing factors.
- Early and aggressive supportive care, including adequate atropine dosage, in intensive or coronary care settings can decrease mortality.
Objective:
To study the frequency, extent, and pathogenesis of the cardiac complications accompanying organophosphate and carbamate poisoning.
Design:
Retrospective study.
Setting:
A medical intensive care unit (MICU) of a general hospital.
Subjects:
46 adult patients admitted over a five year period with a diagnosis of organophosphate or carbamate poisoning.
Results:
Cardiac complications developed in 31 patients (67%). These were: non-cardiogenic pulmonary oedema, 20 (43%); cardiac arrhythmias, 11 (24%); electrocardiographic abnormalities including prolonged Q-Tc interval, 31 (67%); ST-T changes, 19 (41%); and conduction defects, 4 (9%). Sinus tachycardia occurred in 16 patients (35%) and sinus bradycardia in 13 (28%). Hypertension developed in 10 patients (22%) and hypotension in eight (17%). Eight patients (17%) needed respiratory support because of respiratory depression. Although more than two thirds of the patients (67%) had a prolonged Q-Tc interval, none had polymorphic ventricular tachycardia of the torsade de pointes type. Two patients died from ventricular fibrillation, an in hospital mortality of 4%.
Conclusions:
Cardiac complications often accompany poisoning with these compounds, particularly during the first few hours. Hypoxaemia, acidosis, and electrolyte derangements are major predisposing factors. Intensive supportive treatment in intensive or coronary care facilities with administration of atropine in adequate doses early in the course of the illness will reduce the mortality.

Related Concept Videos
 01:26
Toxic Reactions: Overview
Toxicity falls into two primary categories: local and systemic.
Local toxicity appears at the exposure site, such as protein denaturation caused by caustic substances.
In contrast, systemic toxicity requires the toxic agent's absorption and distribution,...
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is slower than the...
 01:30
Toxidromes: Clinical Features
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Introduction Cardiac Emergencies