Treatment of a dog with an insulinoma-related peripheral polyneuropathy with corticosteroids

L Van Ham1, K G Braund, S Roels

  • 1Department of Small Animal Medicine and Clinical Biology, University of Gent, Belgium.

The Veterinary Record
|July 26, 1997
PubMed

Related Concept Videos

Drugs for Treatment of Crohn's Disease in IBD Using Glucocorticoids01:21

Drugs for Treatment of Crohn's Disease in IBD Using Glucocorticoids

Glucocorticoids, a class of anti-inflammatory drugs, are pivotal in treating moderate to severe Crohn's disease by inducing remission. They exhibit their anti-inflammatory action by inhibiting the production of inflammatory cytokines such as tumor necrosis factor (TNF)-α, interleukin (IL)-1, and chemokines like IL-8. In addition, they reduce the expression of inflammatory cell adhesion molecules and inhibit gene transcription of nitric oxide synthase, phospholipase A2, cyclooxygenase-2 (COX-2),...
Diabetes: Management and Pharmacotherapy01:15

Diabetes: Management and Pharmacotherapy

The therapy for diabetes aims to alleviate hyperglycemia-related symptoms, prevent acute metabolic decompensation, and reduce chronic end-organ complications. Glycemic control is evaluated through short-term (self-monitoring, continuous glucose monitoring) and long-term (A1c, fructosamine) metrics, enabling near real-time tracking of blood glucose levels and reflecting glycemic control over specific time frames.
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
Insulin: Dosing Regimen and Adverse Effects01:16

Insulin: Dosing Regimen and Adverse Effects

Insulin-replacement therapy usually includes both long-acting insulin (basal) and short-acting insulin (to cater to postprandial needs). In a diverse group of type 1 diabetes patients, the average daily insulin dose is typically 0.5-0.7 units/kg body weight. However, obese patients and pubertal adolescents may need more due to insulin resistance.
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
Hypoglycemia and Glucagon01:15

Hypoglycemia and Glucagon

Without prolonged fasting, healthy individuals maintain blood glucose levels above 3.5 mM due to a well-adapted neuroendocrine counterregulatory system that effectively prevents acute hypoglycemia, a potentially life-threatening condition. The primary clinical scenarios for hypoglycemia encompass diabetes treatment, inappropriate production of endogenous insulin or insulin-like substances by tumors, and the use of glucose-lowering agents in non-diabetic individuals. Notably, hypoglycemia in the...
Type I Diabetes II: Pathophysiology01:26

Type I Diabetes II: Pathophysiology
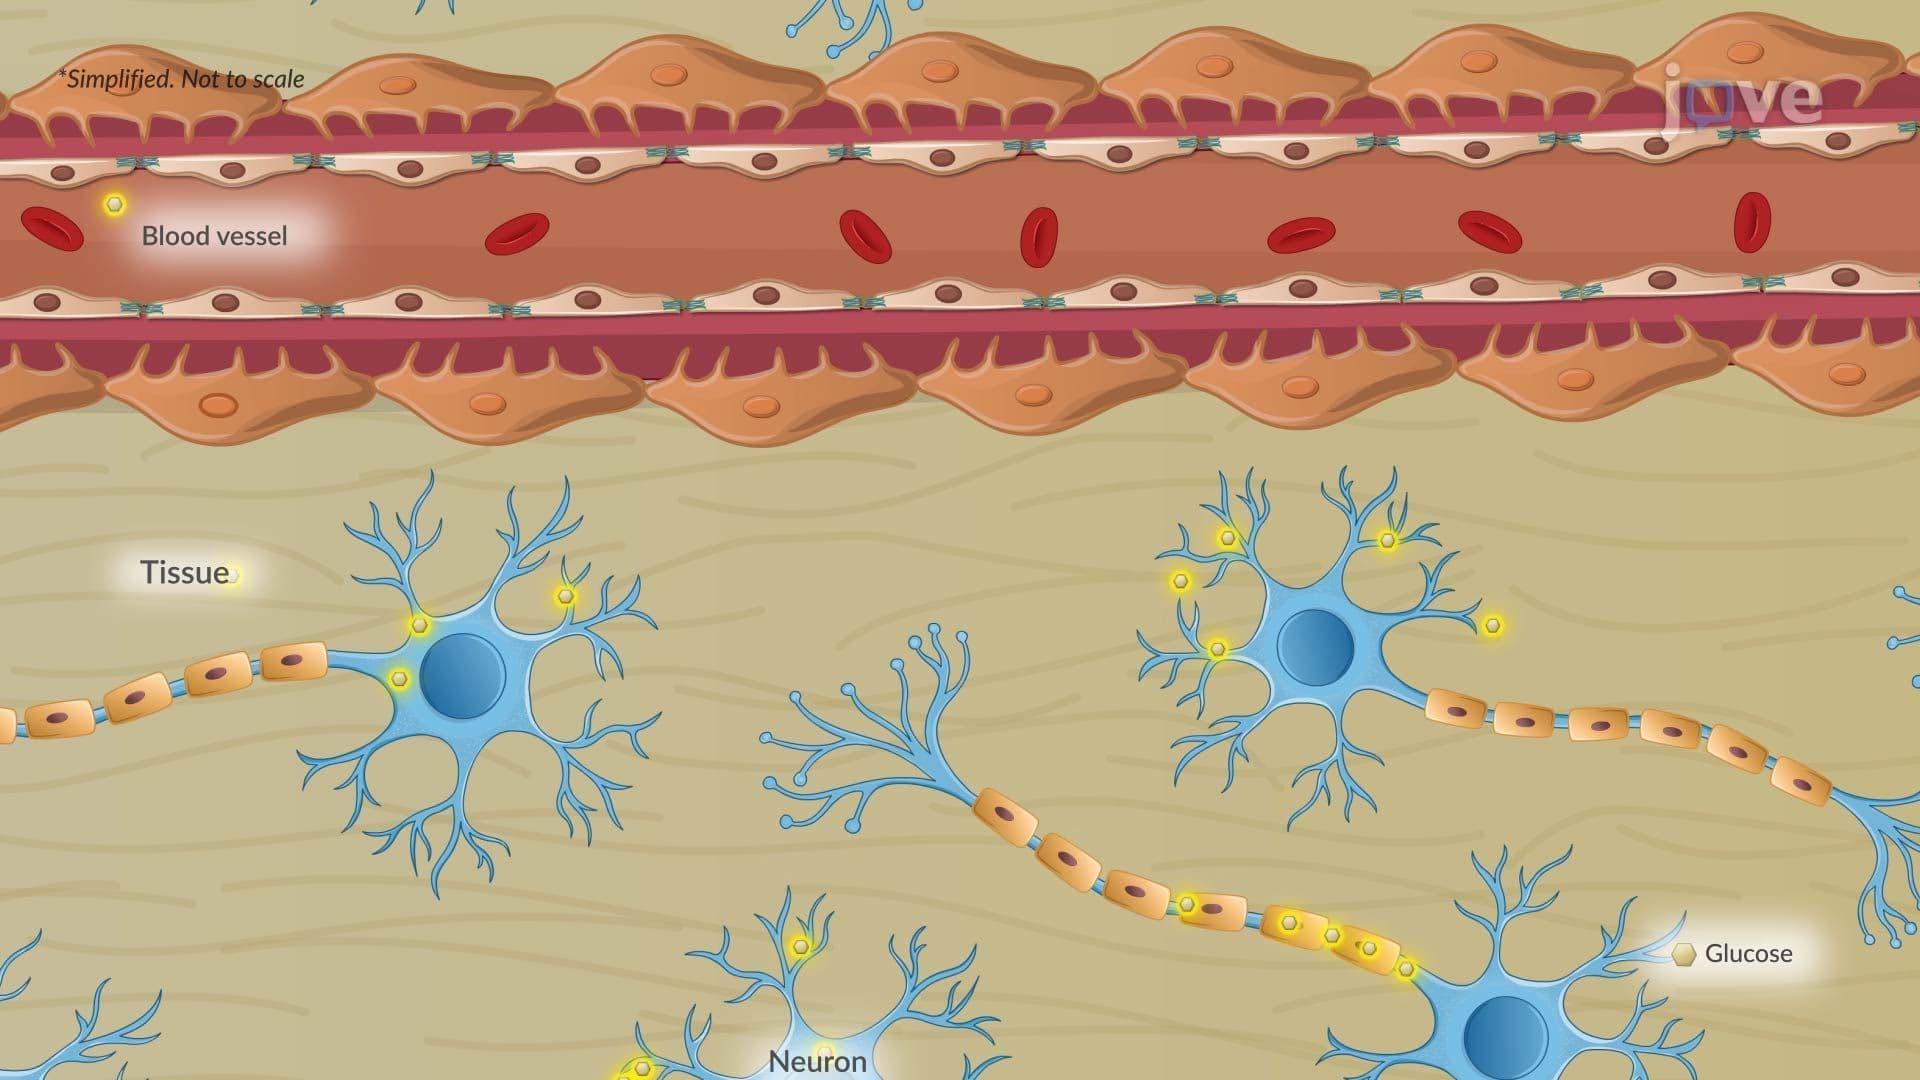
Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular uptake of...
Diabetic Neuropathy01:22

Diabetic Neuropathy

DefinitionDiabetic neuropathy is nerve damage caused by long-standing diabetes mellitus. It results directly from prolonged high blood sugar levels.PathophysiologyThe pathophysiology of diabetic neuropathy involves both metabolic and vascular disturbances triggered by chronic hyperglycemia.Metabolic injury: Elevated glucose levels activate the polyol pathway within nerve cells, leading to the accumulation of sorbitol and fructose. This increases oxidative stress, disrupts normal nerve...