[Churg-Strauss syndrome--case report]

B Grabowska1, M Raźny

  • 1Oddziału Chorób Wewnetrznych i Hematologii, Krakowskiengo Szpitala Specjalistycznego.

Wiadomosci Lekarskie (Warsaw, Poland : 1960)
|January 1, 1997
PubMed

Related Concept Videos

Barrett Esophagus-II: Clinical Manifestations and Management01:21

Barrett Esophagus-II: Clinical Manifestations and Management

Individuals with Barrett's esophagus are often asymptomatic, but they may experience symptoms commonly associated with GERD, such as heartburn and acid regurgitation. Additional symptoms can include difficulty swallowing, chest pain, unintentional weight loss, blood in the stool (which may appear black, tarry, or bloody), and episodes of vomiting.
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
Endocarditis II: Clinical Features of Infective Endocarditis01:25

Endocarditis II: Clinical Features of Infective Endocarditis
Endocarditis can present various clinical features depending on the causative organism and the patient's underlying health conditions. Initially, the clinical features of infective endocarditis develop gradually, presenting with nonspecific symptoms that can be easily mistaken for other illnesses.General SymptomsEarly symptoms of infective endocarditis are fever, chills, weakness, malaise, fatigue, and weight loss. These symptoms reflect the systemic nature of the infection and the body's...
Esophageal Achalasia01:27

Esophageal Achalasia

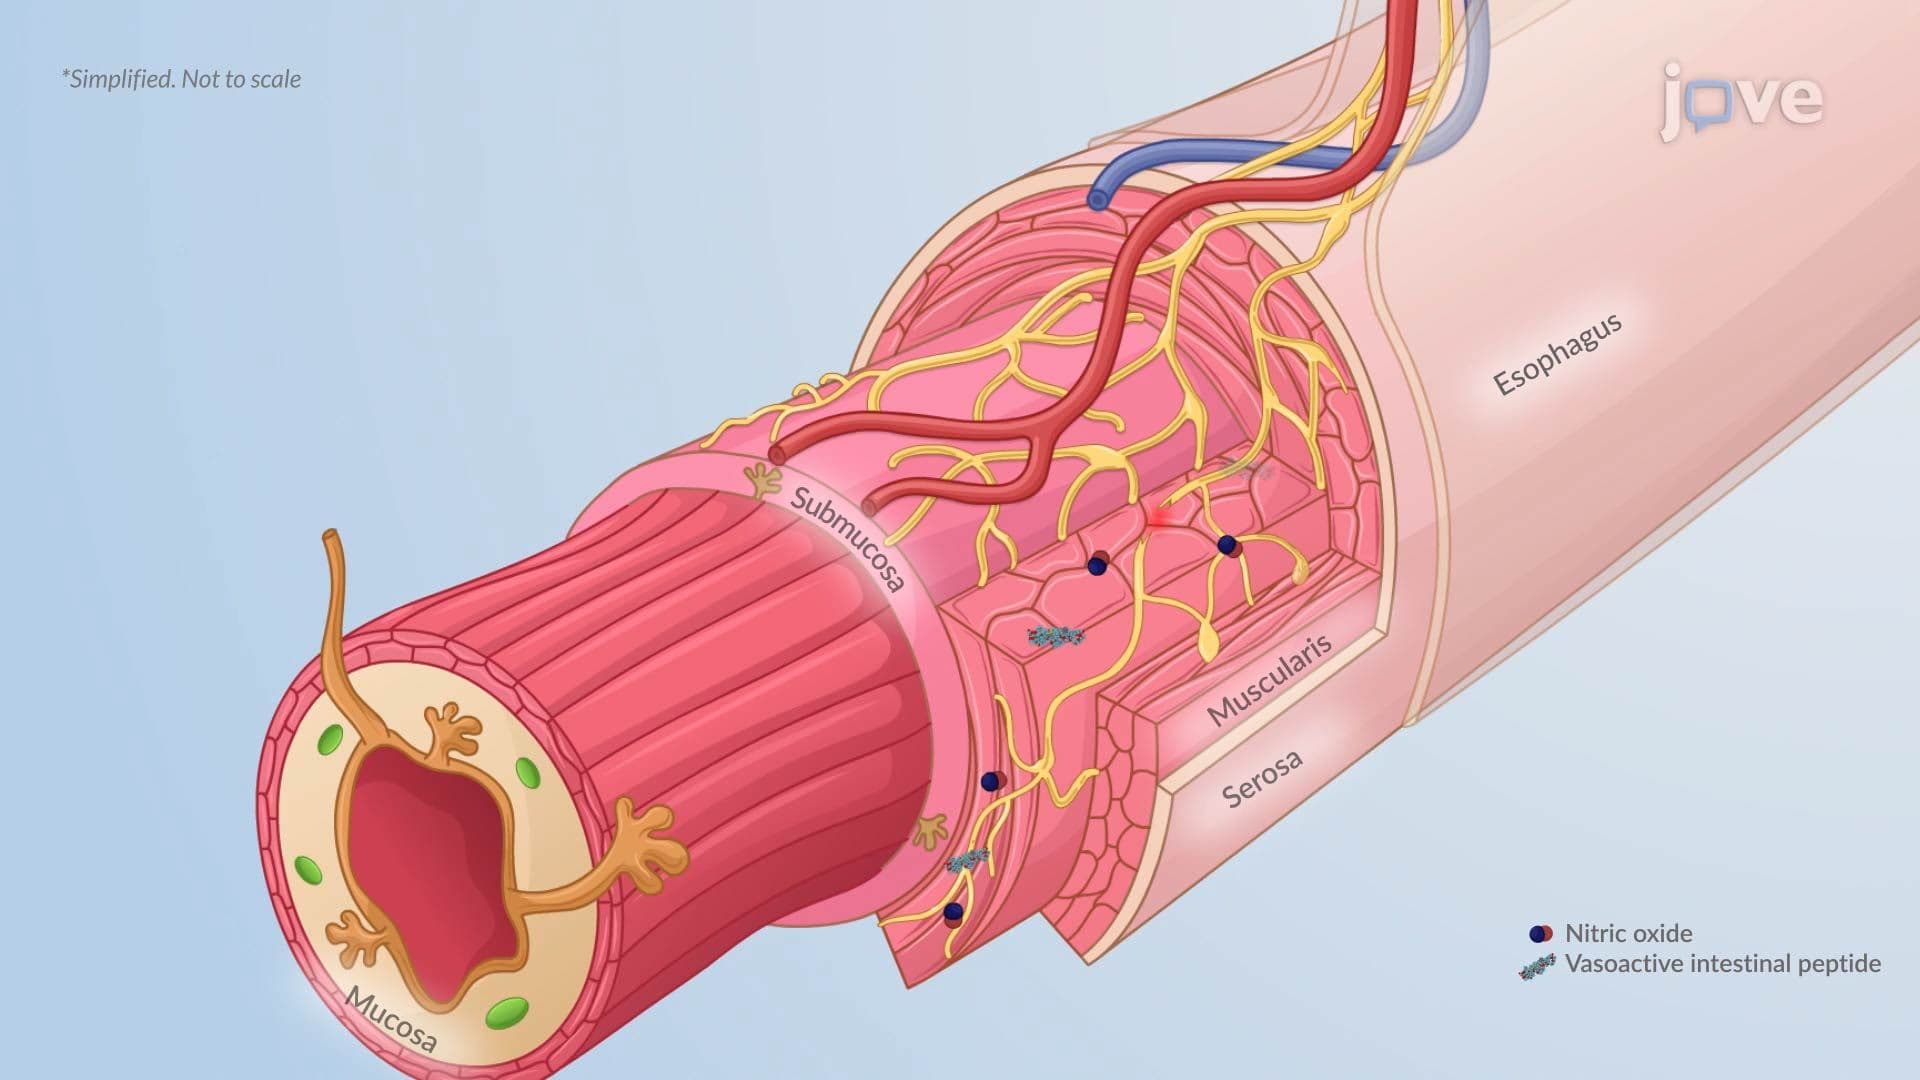
Esophageal achalasia is a chronic neurogenic disorder characterized by impaired relaxation of the lower esophageal sphincter (LES) and absent or ineffective peristalsis in the distal esophagus. This leads to a functional obstruction without a physical blockage, despite significant disruption of esophageal motility.EtiologyAchalasia is caused by degeneration of the myenteric (Auerbach's) plexus, specifically the loss of inhibitory ganglion cells that produce vasoactive intestinal peptide (VIP)...
Esophageal Strictures-I: Introduction01:30

Esophageal Strictures-I: Introduction

Esophageal strictures involve abnormal narrowing or tightening of the esophagus. They vary in length and severity, ranging from mild constriction to complete obstruction, and are classified as benign (noncancerous) or malignant (cancerous).
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
Cushing Syndrome II: Pathophysiology01:19

Cushing Syndrome II: Pathophysiology

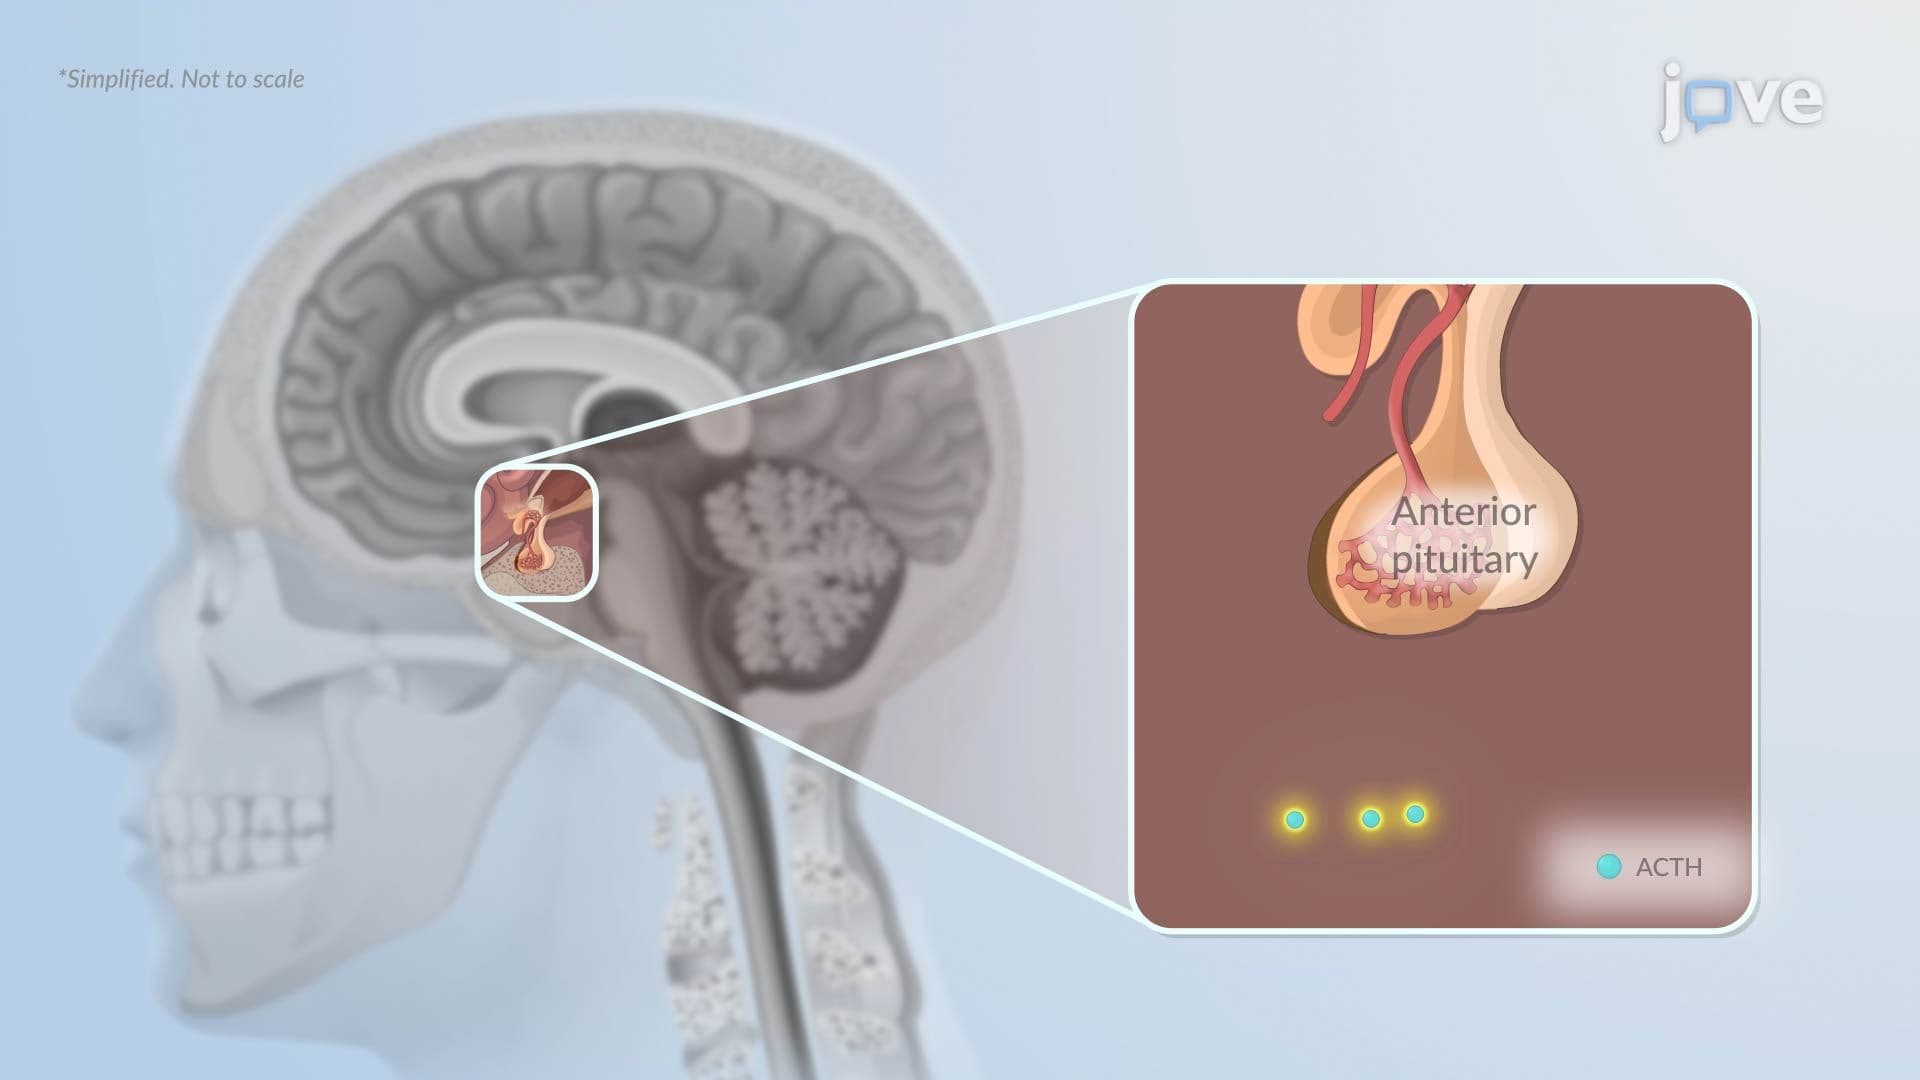
Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features of the...
Acute Coronary Syndrome III: Diagnostic Studies01:30

Acute Coronary Syndrome III: Diagnostic Studies

Diagnosing acute coronary syndrome or ACS begins with a thorough patient history. Notable symptoms include central, crushing chest pain radiating to the left arm, neck, jaw, or back, along with shortness of breath, sweating (diaphoresis), nausea, vomiting, dizziness, and palpitations.It is crucial to note any history of cardiac illnesses and assess risk factors, including age, gender, smoking, hypertension, diabetes, hyperlipidemia, and a sedentary lifestyle.During physical examination, vital...
