Related Experiment Video
Updated: Jun 5, 2026


Tumor Engraftment in a Xenograft Mouse Model of Human Mantle Cell Lymphoma
Published on: March 30, 2018
Immune function of successfully treated lymphoma patients

Immunologic function was evaluated in 12 patients with Hodgkin's disease and 5 patients with lymphocytic lymphoma who had been successfully treated with either chemotherapy, radiation therapy, or both of these modalities 3-42 mo previously. Only two of the patients were found to have total anergy to a battery of six recall skin test antigens and all were responsive to skin testing with phytohemagglutinin. However, 10 of 16 patients were unable to develop delayed cutaneous hypersensitivity to either of the neoantigens dinitrochlorobenzene or keyhole limpet hemocyanin. Four other patients developed reactivity to only one of these neoantigens for a total of 14 of 16 (88%) of the patients demonstrating some impairment in neoantigen response. Total lymphocyte, T-lymphocyte, B-lymphocyte, and null cell numbers, as well as serum immunoglobulins were quantitatively normal. Monocyte numbers, chemotaxis, and Fc receptor activity were normal. Monocyte staphylocidal activity at 60 min was modestly depressed and candidacidal activity was depressed in those receiving both chemotherapy and radiation therapy. Spontaneous (unstimulated) lymphocyte [3H]thymidine incorporation was low in the patients as a group and lymphoblastic transformation to specific antigens was impaired in 11 of 17 patients who had positive skin test reactions to the same antigen. Highly significant suppression of lymphoblastic transformation was noted after stimulation by the mitogens phytohemagglutinin, pokeweed, and concanavalin-A. The greatest impairment of mitogen response was seen in those patients receiving both chemotherapy and radiation therapy. These data demonstrate specific impairments of neoantigen processing, lymphocyte function, and to a lesser extent monocyte function in successfully treated patients with lymphoma. These impairments may contribute to the increased incidence of infections and second primary malignancies in these patients.
Immunologic function was evaluated in 12 patients with Hodgkin's disease and 5 patients with lymphocytic lymphoma who had been successfully treated with either chemotherapy, radiation therapy, or both of these modalities 3-42 mo previously. Only two of the patients were found to have total anergy to a battery of six recall skin test antigens and all were responsive to skin testing with phytohemagglutinin. However, 10 of 16 patients were unable to develop delayed cutaneous hypersensitivity to either of the neoantigens dinitrochlorobenzene or keyhole limpet hemocyanin. Four other patients developed reactivity to only one of these neoantigens for a total of 14 of 16 (88%) of the patients demonstrating some impairment in neoantigen response. Total lymphocyte, T-lymphocyte, B-lymphocyte, and null cell numbers, as well as serum immunoglobulins were quantitatively normal. Monocyte numbers, chemotaxis, and Fc receptor activity were normal. Monocyte staphylocidal activity at 60 min was modestly depressed and candidacidal activity was depressed in those receiving both chemotherapy and radiation therapy. Spontaneous (unstimulated) lymphocyte [3H]thymidine incorporation was low in the patients as a group and lymphoblastic transformation to specific antigens was impaired in 11 of 17 patients who had positive skin test reactions to the same antigen. Highly significant suppression of lymphoblastic transformation was noted after stimulation by the mitogens phytohemagglutinin, pokeweed, and concanavalin-A. The greatest impairment of mitogen response was seen in those patients receiving both chemotherapy and radiation therapy. These data demonstrate specific impairments of neoantigen processing, lymphocyte function, and to a lesser extent monocyte function in successfully treated patients with lymphoma. These impairments may contribute to the increased incidence of infections and second primary malignancies in these patients.


Related Concept Videos
 01:40
Cell-mediated Immune Responses
 01:28
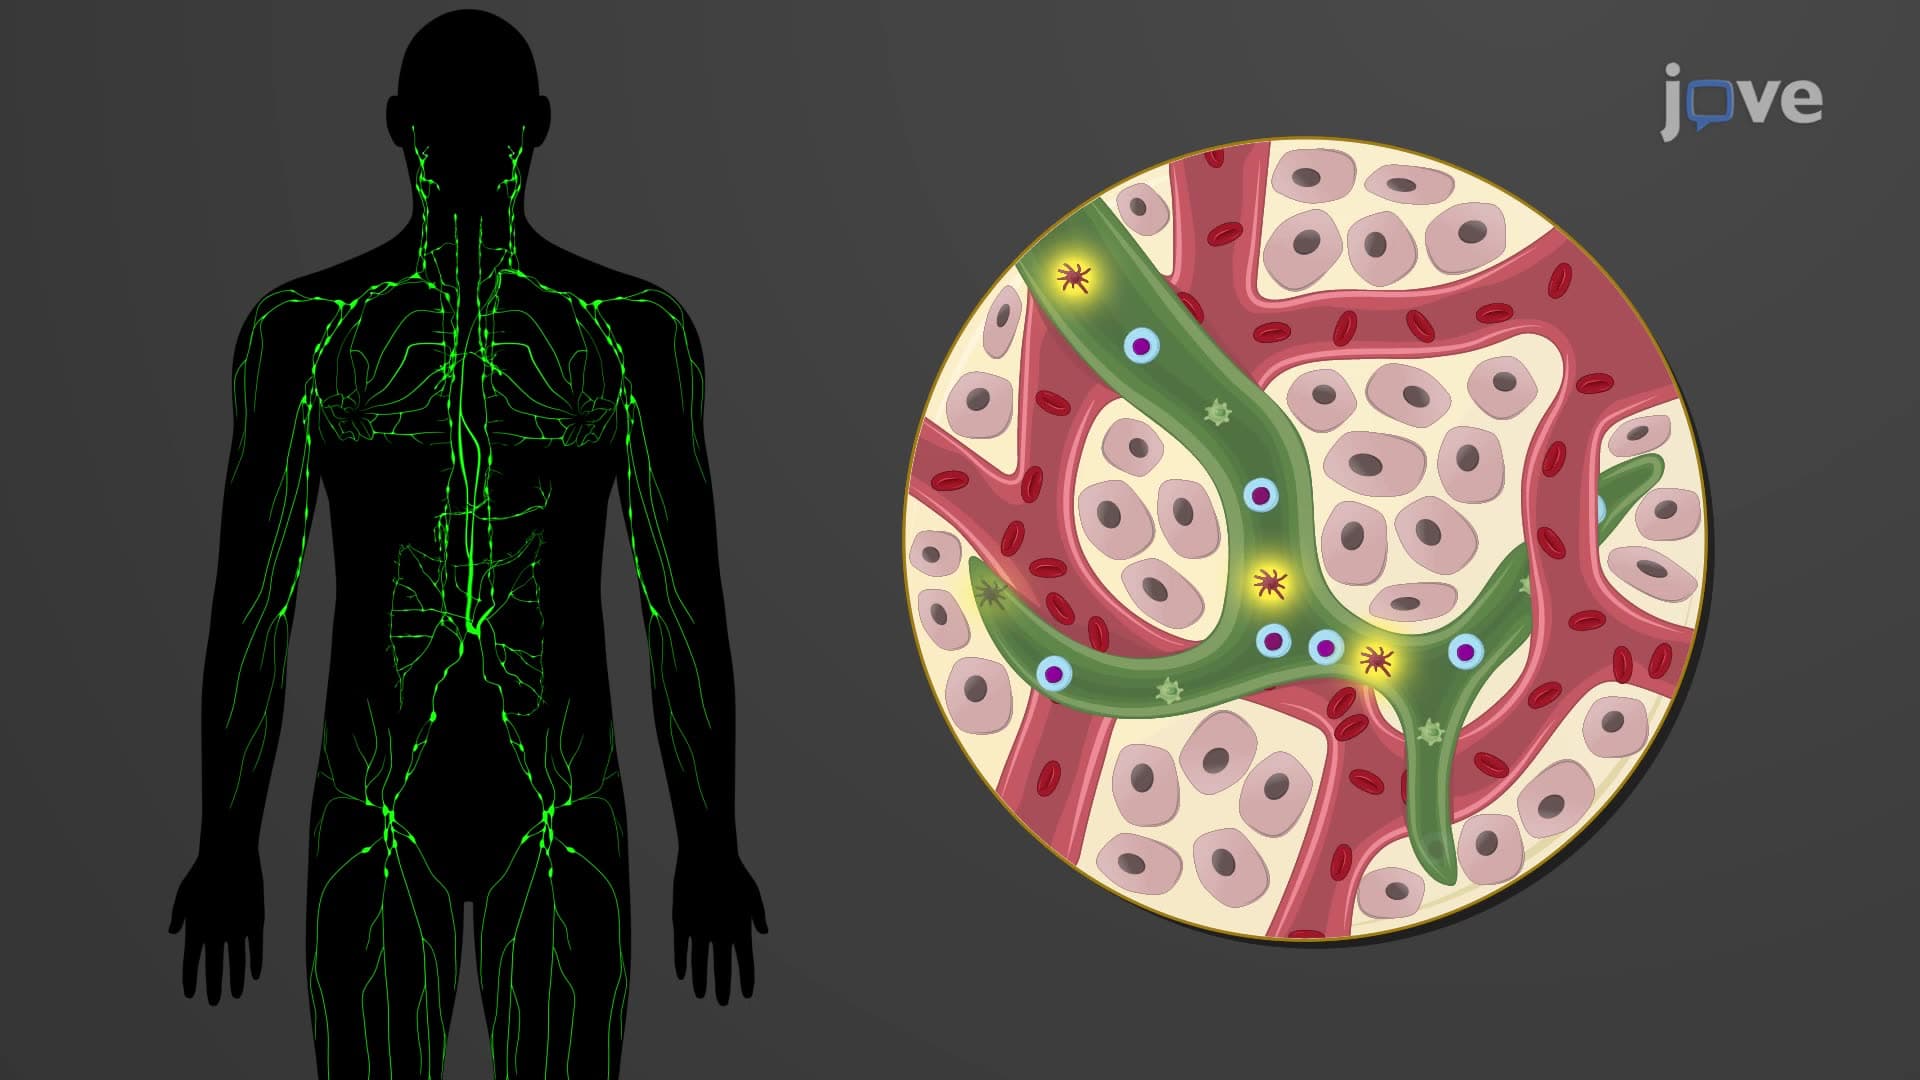
Functions of the Lymphatic and Immune System
The primary lymphoid organs, including the bone marrow and the thymus, serve as the maturation sites for lymphocytes. Secondary lymphoid organs, like the mucosa-associated lymphoid tissue, activate these lymphocytes and serve as...
 01:18
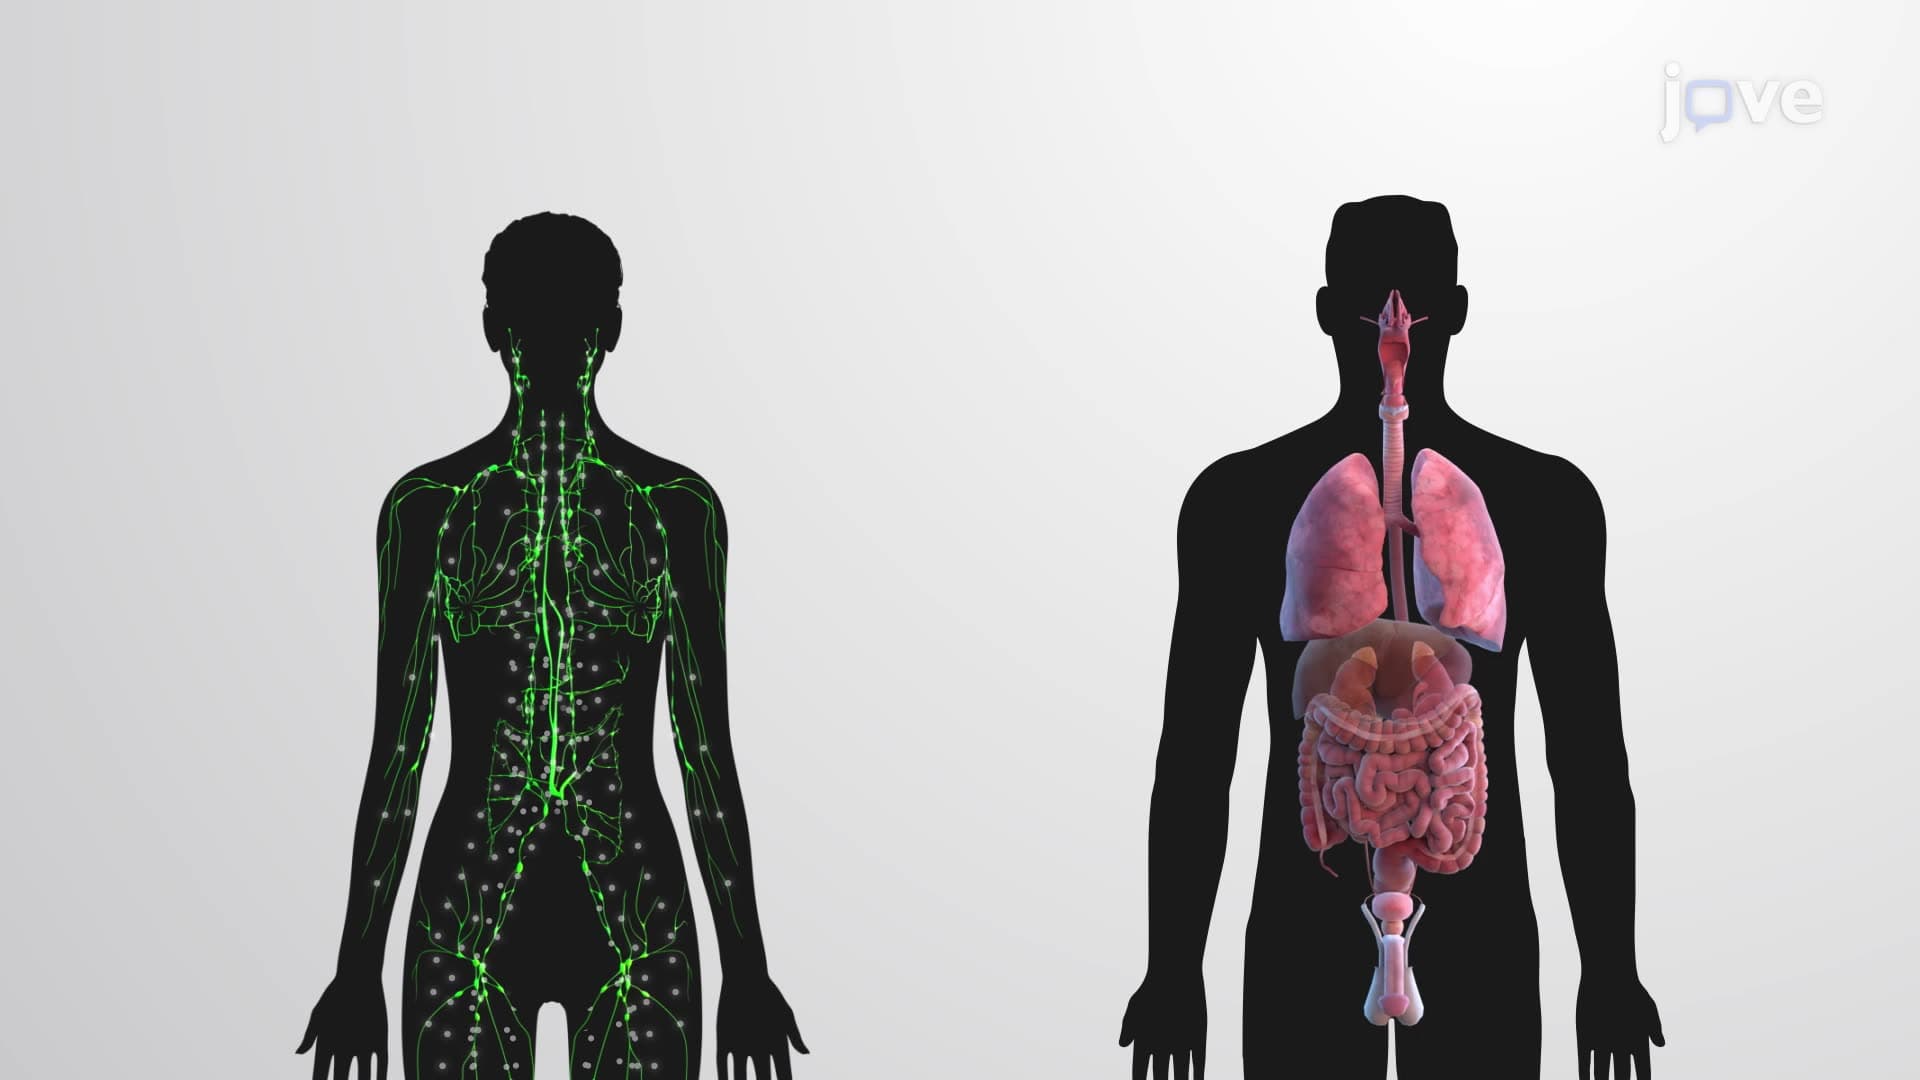
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
 01:20
Special Features of Adaptive Immunity
The primary cell types involved in adaptive immunity are T cells and B cells. Each type has a unique role in defending the body against pathogens. T cells are responsible for cell-mediated immunity. They identify and eliminate infected cells directly,...
 01:27
Cytotoxic T Cells-mediated Immune Response
Immunological surveillance is the ability of immune cells to monitor and eliminate infected cells with intracellular pathogens, neoplastically transformed cells, and cells with non-self antigens. Cytotoxic T cells and NK...
 01:27
Tumor Immunotherapy