Parietal cell protrusions in gastric ulcer disease
Related Experiment Video
Updated: Oct 31, 2026

Mouse- and Human-derived Primary Gastric Epithelial Monolayer Culture for the Study of Regeneration
Published on: May 7, 2018
1Department of Pathology, New England Medical Center, Boston, MA 02111, USA.

Abstract:
Oxyntic mucosal biopsy specimens from patients receiving omeprazole therapy have been described as frequently showing characteristic tonguelike protrusions of parietal cell cytoplasm (PCP) into the gland lumen. Although protrusion of parietal cell cytoplasm is believed to be associated with omeprazole therapy and has been implicated in the histogenesis of fundic gland polyps, we have observed it in a wide variety of different conditions unrelated to peptic ulcer disease or omeprazole therapy. To establish the incidence of PCP and analyze its relationship to gastritis, gland dilatation, cystic change, and fundic gland polyps, we studied 400 gastric mucosal biopsy specimens from gastric ulcer patients who were not receiving omeprazole therapy and who did not receive any medications for at least 2 weeks. Severity of each of these changes was graded on a scale of I to III. PCP was observed in oxyntic mucosal biopsy specimens from 60 (15%) patients and was associated with varying grades of chronic superficial or interstitial gastritis in 25 (Helicobacter pylori was identified in 12). Although chronic atrophic gastritis, cystic change, or fundic gland polyps were not identified in any of the cases with PCP, gland dilatation was present in 25 of 60 (42%) biopsy specimens. No consistent linear correlation was observed between increasing grades of PCP and gastritis or gland dilatation. Our findings of PCP in 15% of gastric ulcer patients who were off all medications for 2 weeks indicate that PCP is not always related to omeprazole usage. It appears to be a change encountered in a wide variety of diverse settings and, therefore, should not be used to monitor omeprazole therapy. In gastric ulcer patients, there is no linear correlation between PCP and gland dilatation or severity of gastritis. The lack of association of PCP with such cardinal features of fundic gland polyps as gland dilatation and cystic change suggests that PCP per se has little if any role in the development of such polyps. The exact clinical and functional significance of PCP remain to be established and merits further investigation.
More Related Videos


Related Concept Videos
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:25
Mucosal Barrier of the Stomach
Within parietal cells, carbonic acid is first formed through the reaction of water and carbon dioxide. The dissociation of carbonic acid releases bicarbonate and hydrogen ions. The bicarbonate...
 01:27
Peptic Ulcer
 01:26
Gastritis II: Pathophysiology
 01:28
Peptic Ulcer Disease II: Pathophysiology
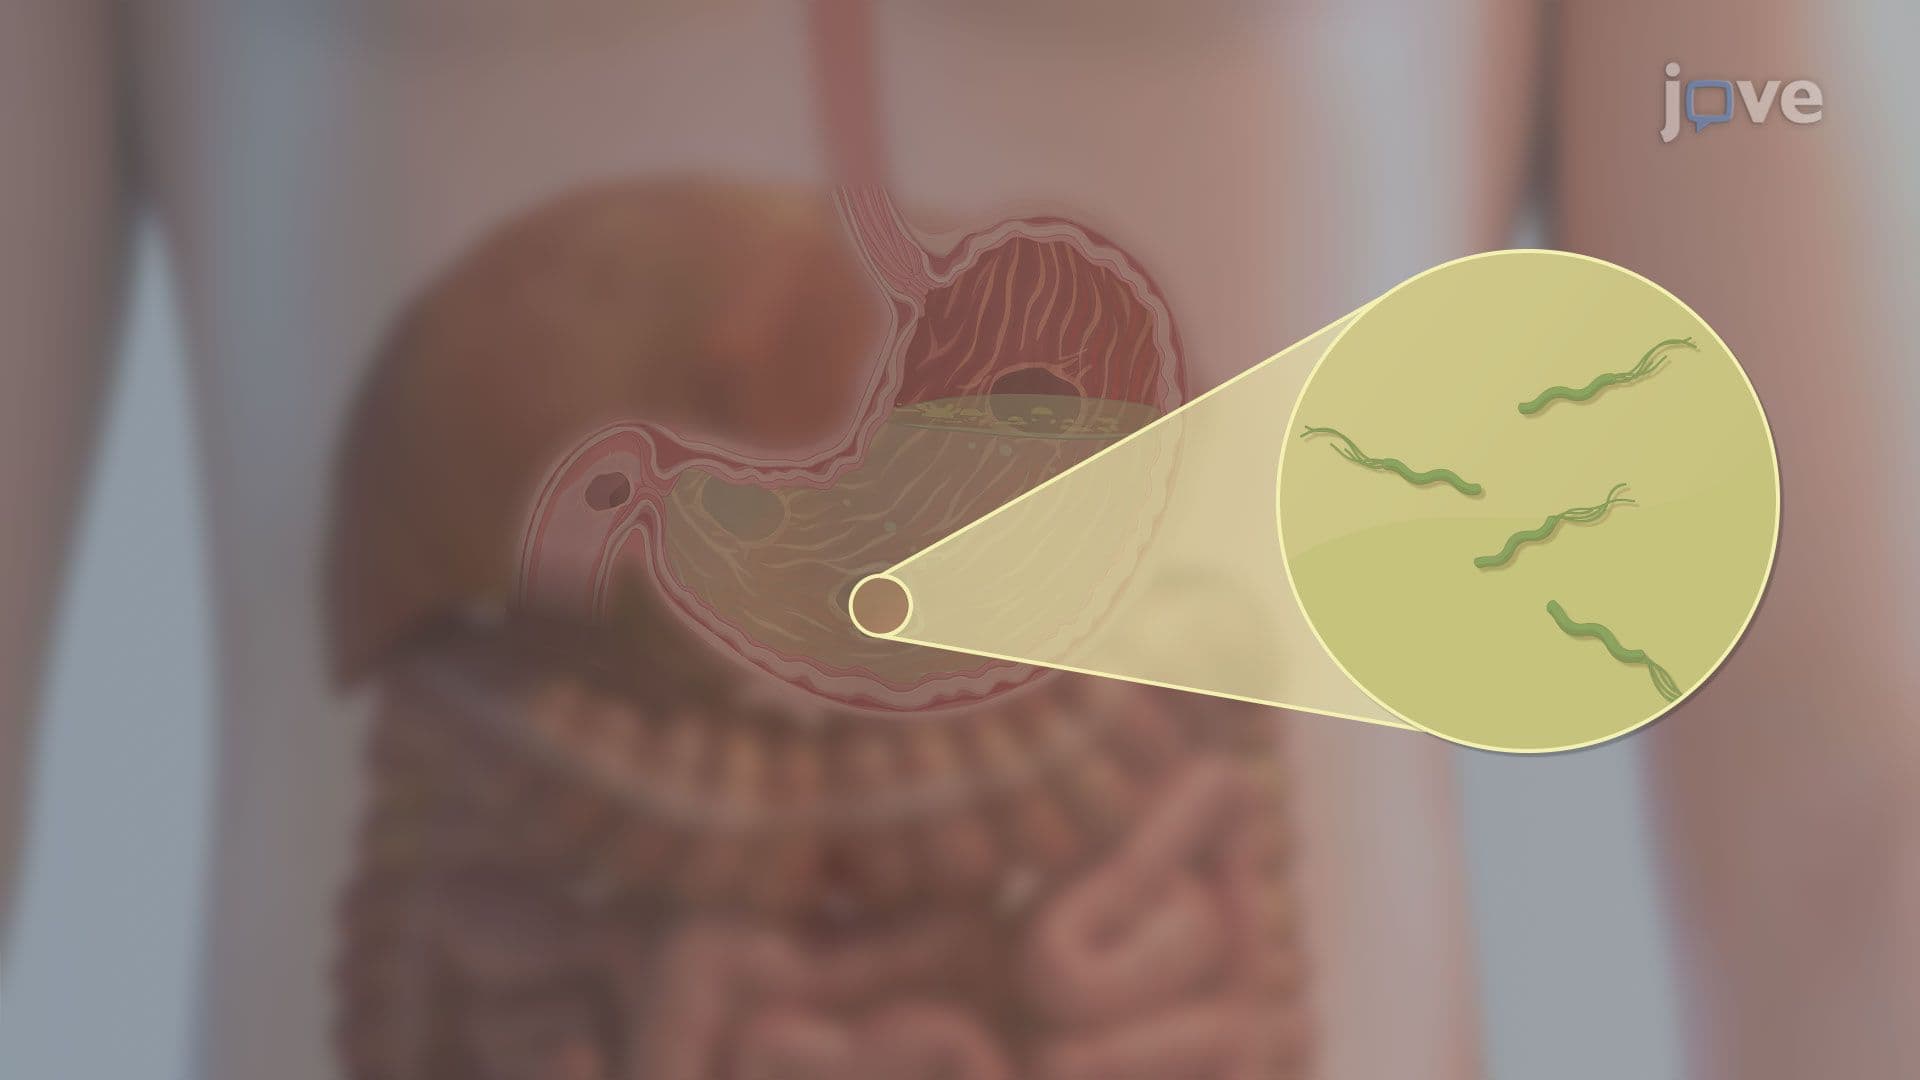
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:24
Peptic Ulcer Disease II: Pathophysiology