Practical treatment guide for dose individualisation in cancer chemotherapy
Related Experiment Video
Updated: Sep 15, 2026
Proton Therapy Delivery and Its Clinical Application in Select Solid Tumor Malignancies
Published on: February 6, 2019
P Canal1, E Chatelut, S Guichard
1Pharmacology Laboratory, Institut Claudius Regaud, Toulouse, France. canal@icr.fnclcc.fr

Abstract:
Dosages of anticancer drugs are usually calculated on the basis of a uniform standard, the body surface area (BSA). Although many physiological functions are proportionate to BSA, overall drug clearance is only partially related to this parameter. Consequently, following administration of equivalent drug dosages based on BSA, a wide variability in plasma drug concentrations can be found between patients, as a result of which some patients experience little toxicity while others may show severe toxic symptoms. A clear pharmacokinetic/pharmacodynamic correlation has been demonstrated for some anticancer drugs, and this relationship provides a background against which rational dose optimisation can be implemented for individual patients. The 3 strategies that can be employed for optimising dosage regimens, none based on BSA, are described and criticised. A priori adaptive dosage determination is based on the relative contribution of identifiable characteristics of patient, drug therapy and disease state that influence plasma drug concentrations; the dosage regimen is based on each patient's profile with regard to these characteristics. Although this approach is most successful with drugs whose clearance is closely tied to renal function, patient characteristics such age, obesity, serum albumin or hepatic function may be useful. The anticancer drug most closely identified with this approach is carboplatin, although dosage reduction strategies for etoposide, taxanes, anthracyclines, topotecan, oxazaphosphorines, vinca alkaloids or melphalan are advocated for patients with renal or hepatic dysfunction. The importance of pharmacogenetics for fluorouracil and mercaptopurine is also briefly discussed. The second approach consists of adaptive dosage adjustments during repetitive or continuous administration of a drug. It has been used for several years to administer methotrexate therapy and, more recently, it has been developed more fully and applied to continuous infusion of fluorouracil or etoposide. It was based, after determination of a target plasma concentration or area under the plasma drug concentration-time curve (AUC), on modification of the drug dosage during the cycle of chemotherapy or for the next cycle. Finally, the third approach of adaptive dosage adjustment with feedback control, based on population pharmacokinetics, with limited sampling strategy, may allow a feedback revision of the dosage following measurement of plasma drug concentration and comparison with the population previously studied. This approach is a theoretical strategy which has not, until now, been used prospectively in clinical oncology. For drugs such as anticancer agents with a very narrow therapeutic index, every effort should be made to minimise interpatient variability in drug exposure in order to maximise the benefit while keeping the risk of serious adverse effects at an acceptable level. This is particularly important when treatment is being given with curative intent.
More Related Videos
 06:20
Irradiator Commissioning and Dosimetry for Assessment of LQ α and β Parameters, Radiation Dosing Schema, and in vivo Dose Deposition
Published on: March 11, 2021
 07:57
Positron Emission Tomography-based Dose Painting Radiation Therapy in a Glioblastoma Rat Model using the Small Animal Radiation Research Platform
Published on: March 24, 2022
Related Concept Videos
 02:50
Combination Therapies and Personalized Medicine
The combination of the drug acetazolamide and sulforaphane is a good example of combination therapy to treat cancer. The cells in the interior of a large tumor often die due to the hypoxic and...
02:50Combination Therapies and Personalized Medicine
The combination of the drug acetazolamide and sulforaphane is a good example of combination therapy to treat cancer. The cells in the interior of a large tumor often die due to the hypoxic and...
 01:28
Dosage Regimens: Designs and Approaches
 01:24
Dosage Regimen: Individualization
 01:23
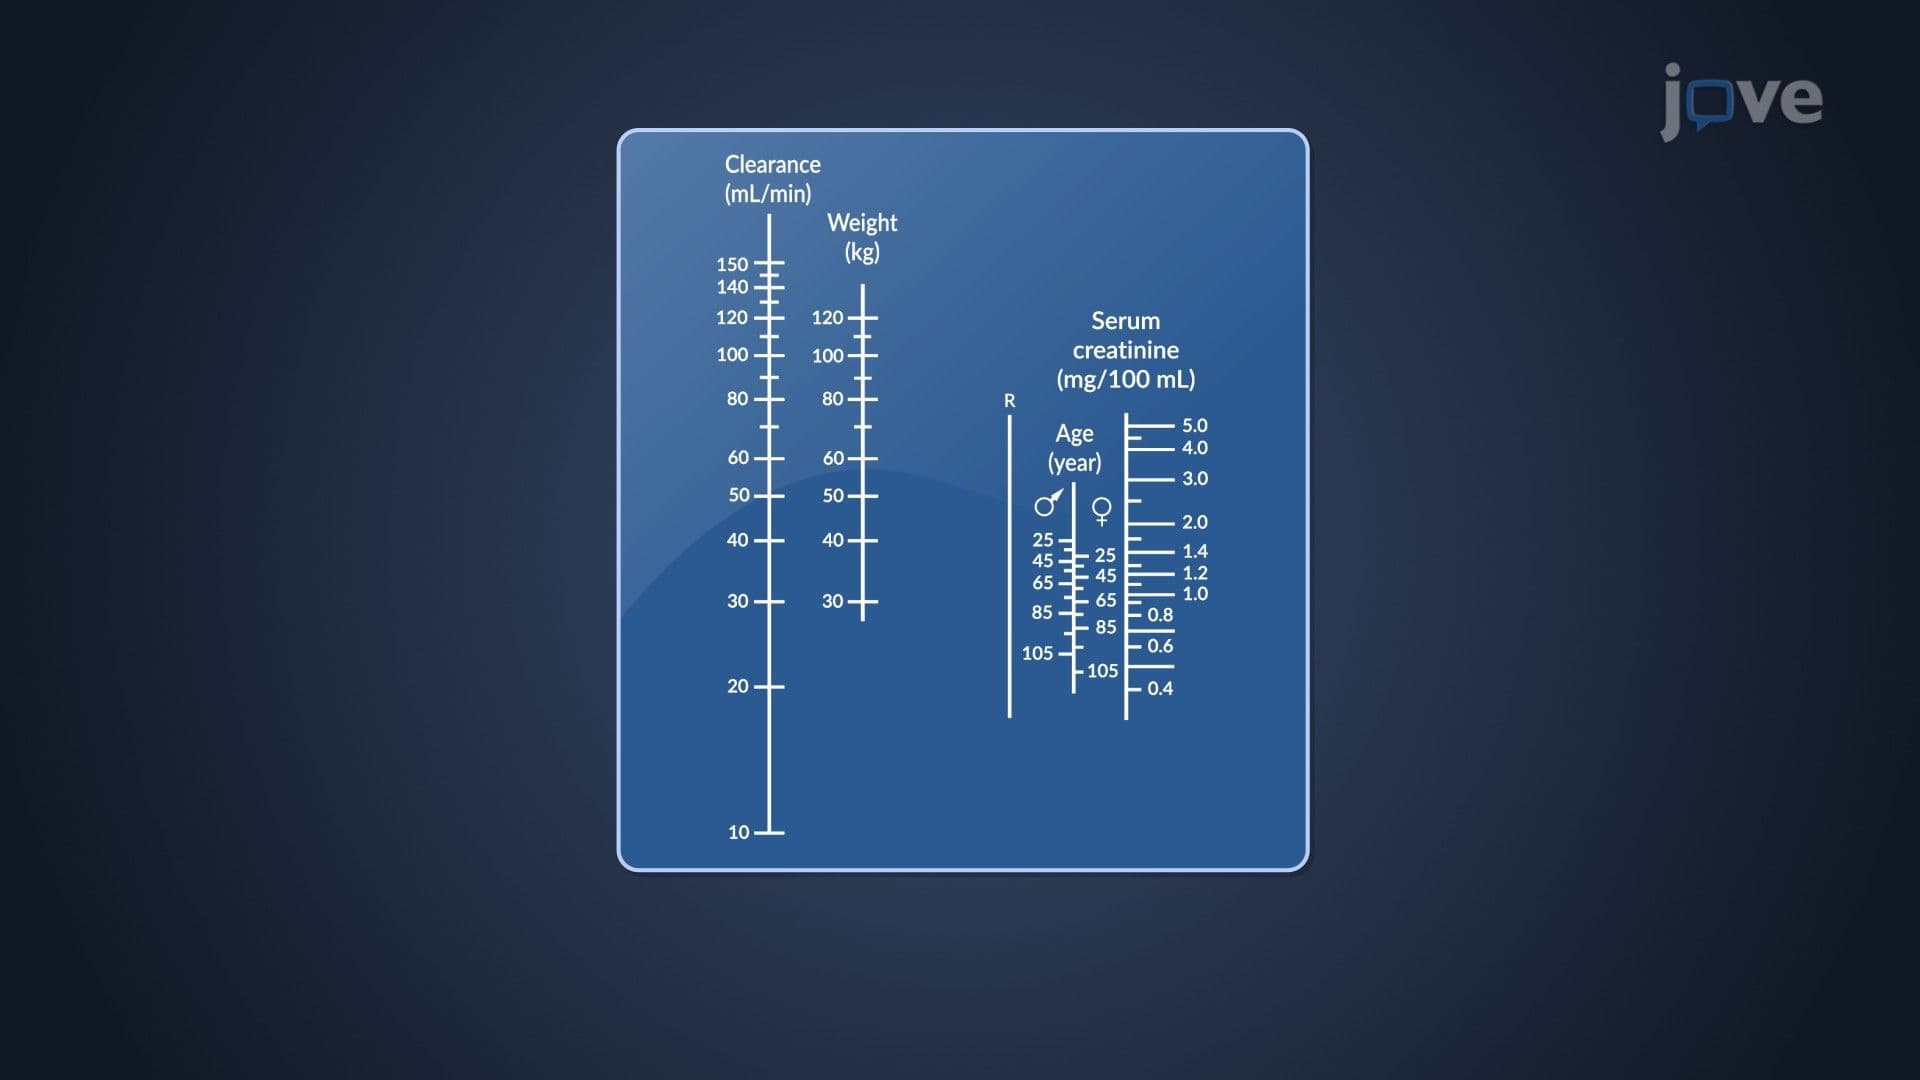
Dosage Regimen Designs: Nomograms and Tabulations
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses