Related Experiment Video
Updated: Jul 18, 2026


Multiplexed Fluorescent Immunohistochemical Staining, Imaging, and Analysis in Histological Samples of Lymphoma
Published on: January 9, 2019
Cutaneous lymphoid hyperplasia presenting as a solitary facial nodule: clinical, histopathological,
Reuven Bergman1, Ziad Khamaysi, Dvora Sahar
1Department of Dermatology and Dermatopathology Section, Rambam Medical Center, and the Bruce Rappaport Faculty of Medicine, Technion Institute of Technology, Haifa, Israel. r_bergman@rambam.health.gov.il

Insights
Cutaneous lymphoid hyperplasia presenting as a solitary facial nodule showed mixed T and B cells, with some atypical lymphocytes. Two of three cases had T-cell receptor gene rearrangements, and lesions regressed spontaneously.
Area of Science:
- Dermatology
- Immunohistochemistry
- Molecular Pathology
Background:
- Cutaneous lymphoid hyperplasia (CLH) can present as a solitary facial nodule.
- Distinguishing CLH from cutaneous lymphomas is crucial for appropriate management.
Purpose of the Study:
- To characterize the clinicopathological, immunophenotypical, and molecular features of CLH presenting as a solitary facial nodule.
- To assess the relationship between these features and clinical outcomes.
Main Methods:
- Retrospective study of three patients with solitary facial nodules.
- Clinical, histological, and immunophenotypical analysis.
- Molecular analysis for T-cell receptor (TCR) and immunoglobulin heavy chain (IGH) gene rearrangements.
Main Results:
- Histology revealed dense lymphocytic infiltrates with a mix of T cells (CD3+, CD4+ > CD8+) and B cells, occasional atypical lymphocytes, and histiocytes.
- TCR gene rearrangements were positive in 2 of 3 cases; one case also showed clonal B cells.
- Lesions showed spontaneous regression after biopsy, with no recurrence or extracutaneous spread during 5.0-5.5 years of follow-up.
Conclusions:
- CLH presenting as a solitary facial nodule shares features with benign reactive infiltrates and cutaneous lymphomas.
- Careful clinical and therapeutic management is necessary due to overlapping characteristics.
Objective:
To elucidate the clinicopathological, immunophenotypical, and molecular characteristics of cutaneous lymphoid hyperplasia presenting as a solitary facial nodule.
Design:
Retrospective study.
Setting:
University dermatology department.
Patients:
Three patients with a solitary facial nodule were studied clinically, histologically, immunophenotypically, and molecularly for T-cell receptor and immunoglobulin heavy chain gene rearrangements.
Main Outcome Measures:
Histological, immunophenotypical, and molecular characteristics in relation to the clinical outcome.
Results:
Histologically, dense diffuse lymphocytic infiltrates were present throughout the dermis, occasionally extending into the subcutaneous fat and the epidermis and hair follicles. Small lymphocytes predominated, but in 2 cases there were also medium to large atypical lymphocytes, with some blastlike lymphocytes. The lymphocytic population was mixed with more CD3(+) T cells than CD20(+) B cells, without germinal centers. There were more CD4(+) than CD8(+) cells, and some of the T cells stained for the memory T-cell marker CD45RO. Numerous CD68(+) histiocytes were scattered or formed small aggregates, and in 1 case small granulomas and many scattered S100 protein-positive and CD1a(+)dendritic cells were present. In addition, several polytypic plasma cells, eosinophils, and extravasated erythrocytes were found. Immunostaining for CD10, CD21, CD30, CD56, and BCL6 was negative. The Ki-67 proliferation index was relatively low (5%-10%). Results of the T-cell receptor gene rearrangement studies were positive in 2 cases, 1 of which also harbored clonal B cells. Serologic test results for Borrelia burgdorferi, Borrelia afzelii, and Borrelia garinii were negative in all 3 cases. Two lesions regressed spontaneously after an incisional biopsy, and none of the cases showed recurrence or extracutaneous spread during a follow-up period of 5.0 to 5.5 years.
Conclusions:
Cutaneous lymphoid hyperplasia that presents as a solitary facial nodule may share clinical, cytological, immunophenotypical, and molecular features with both benign reactive lymphocytic infiltrates and cutaneous lymphomas, and therefore a careful clinical and therapeutic approach is warranted.
Related Concept Videos
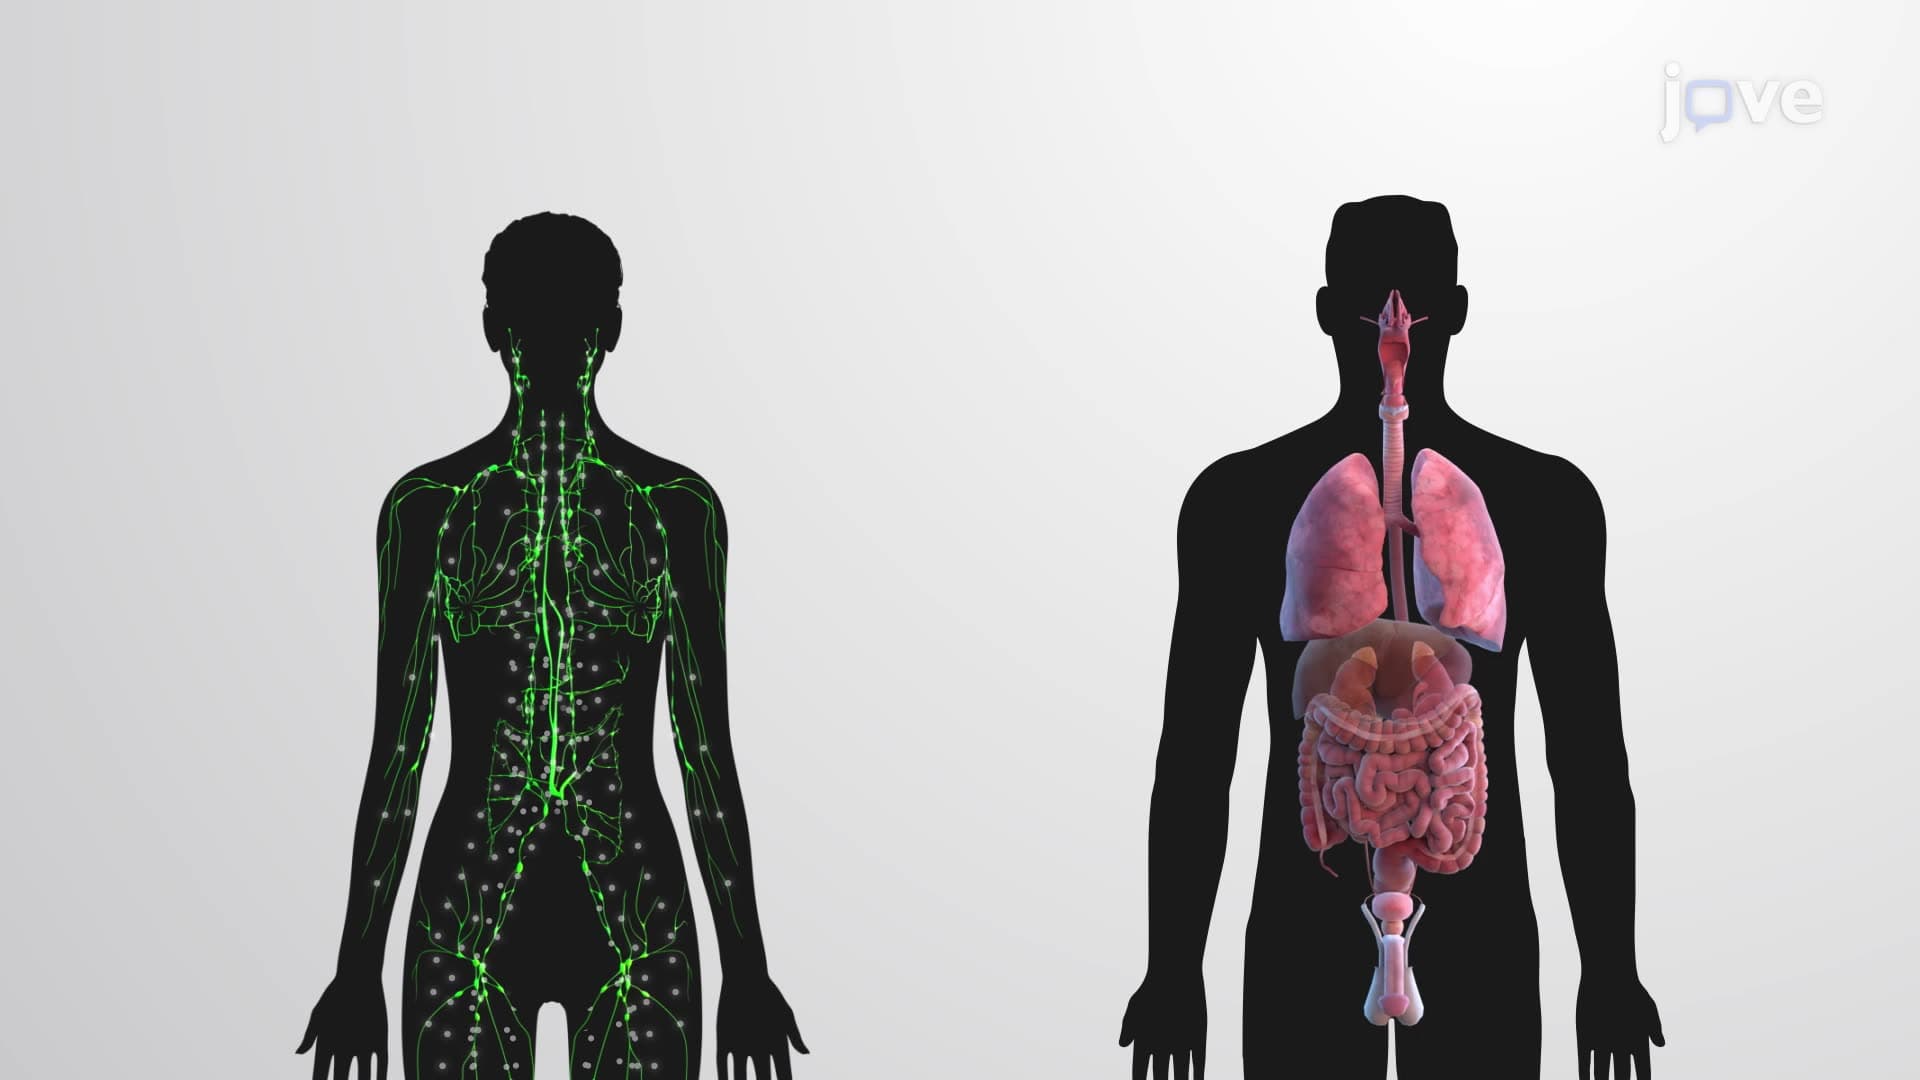 01:18
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
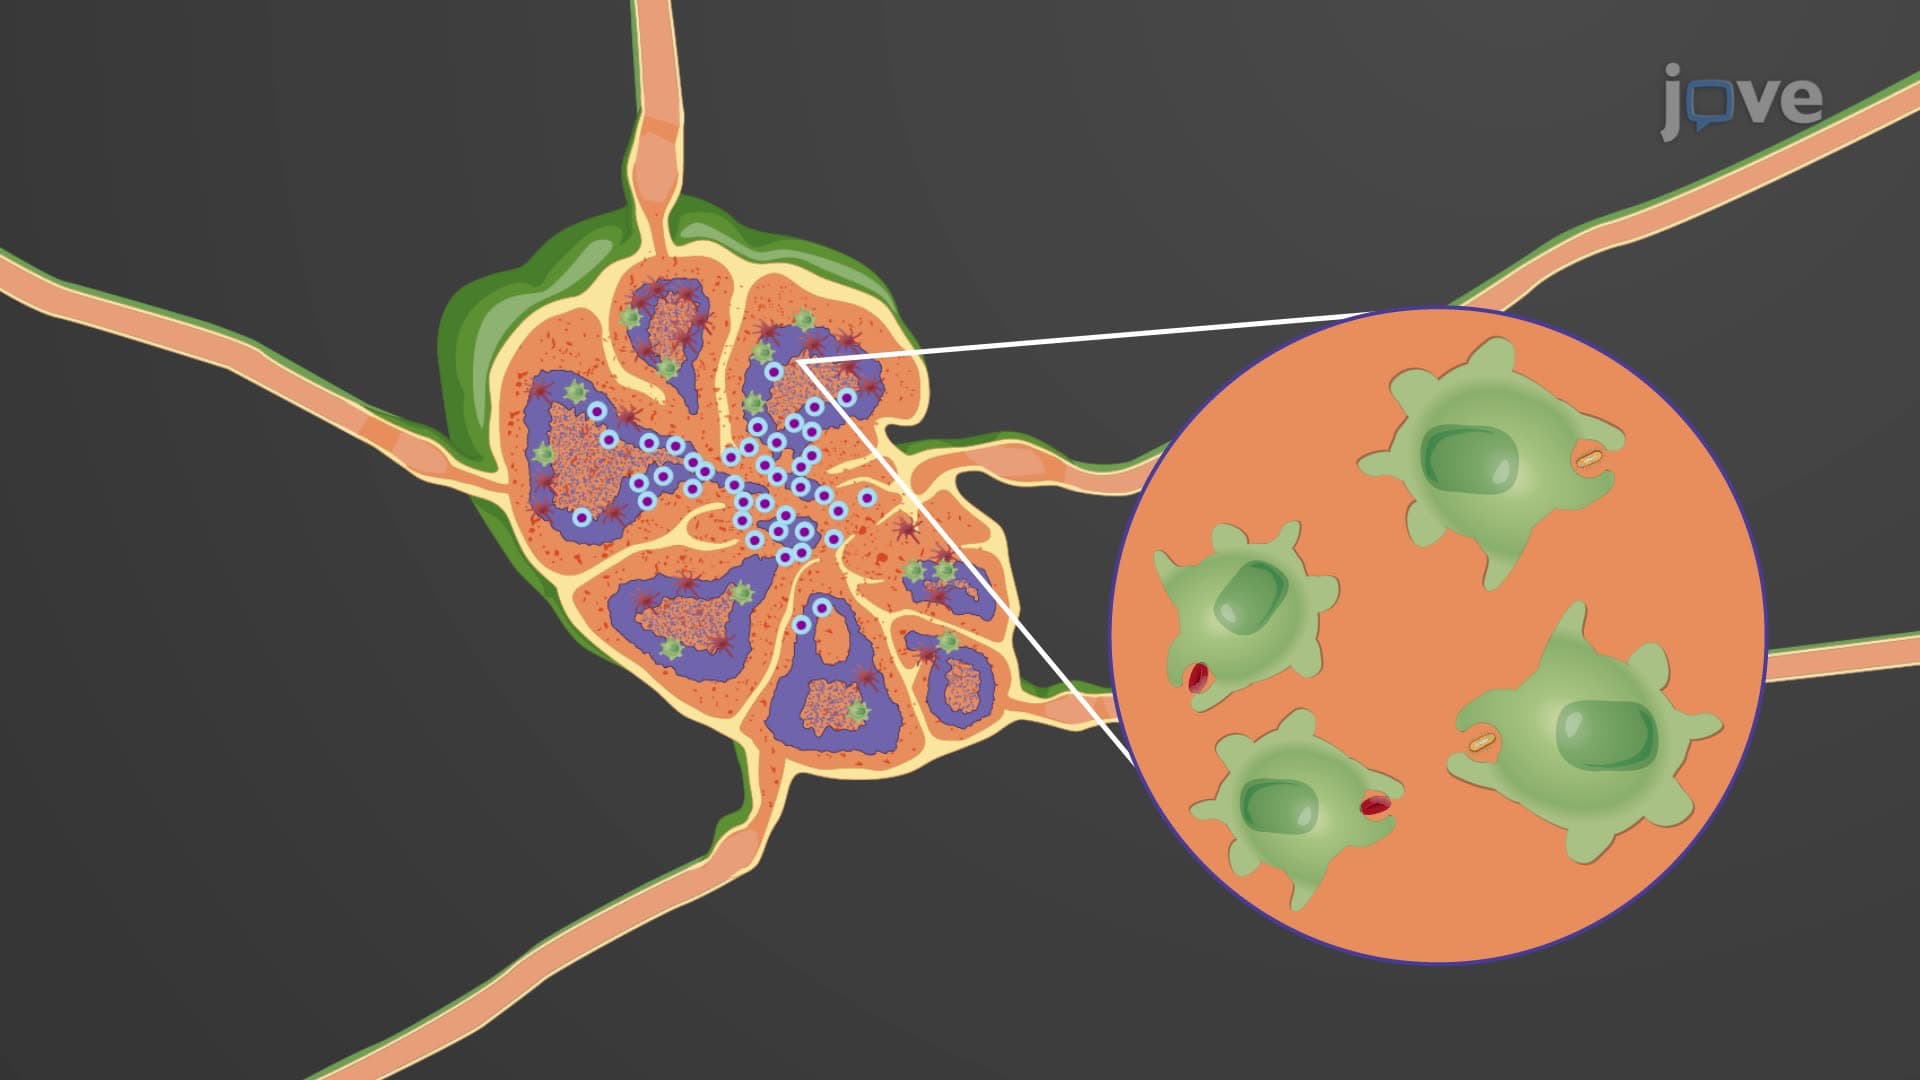 01:15
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
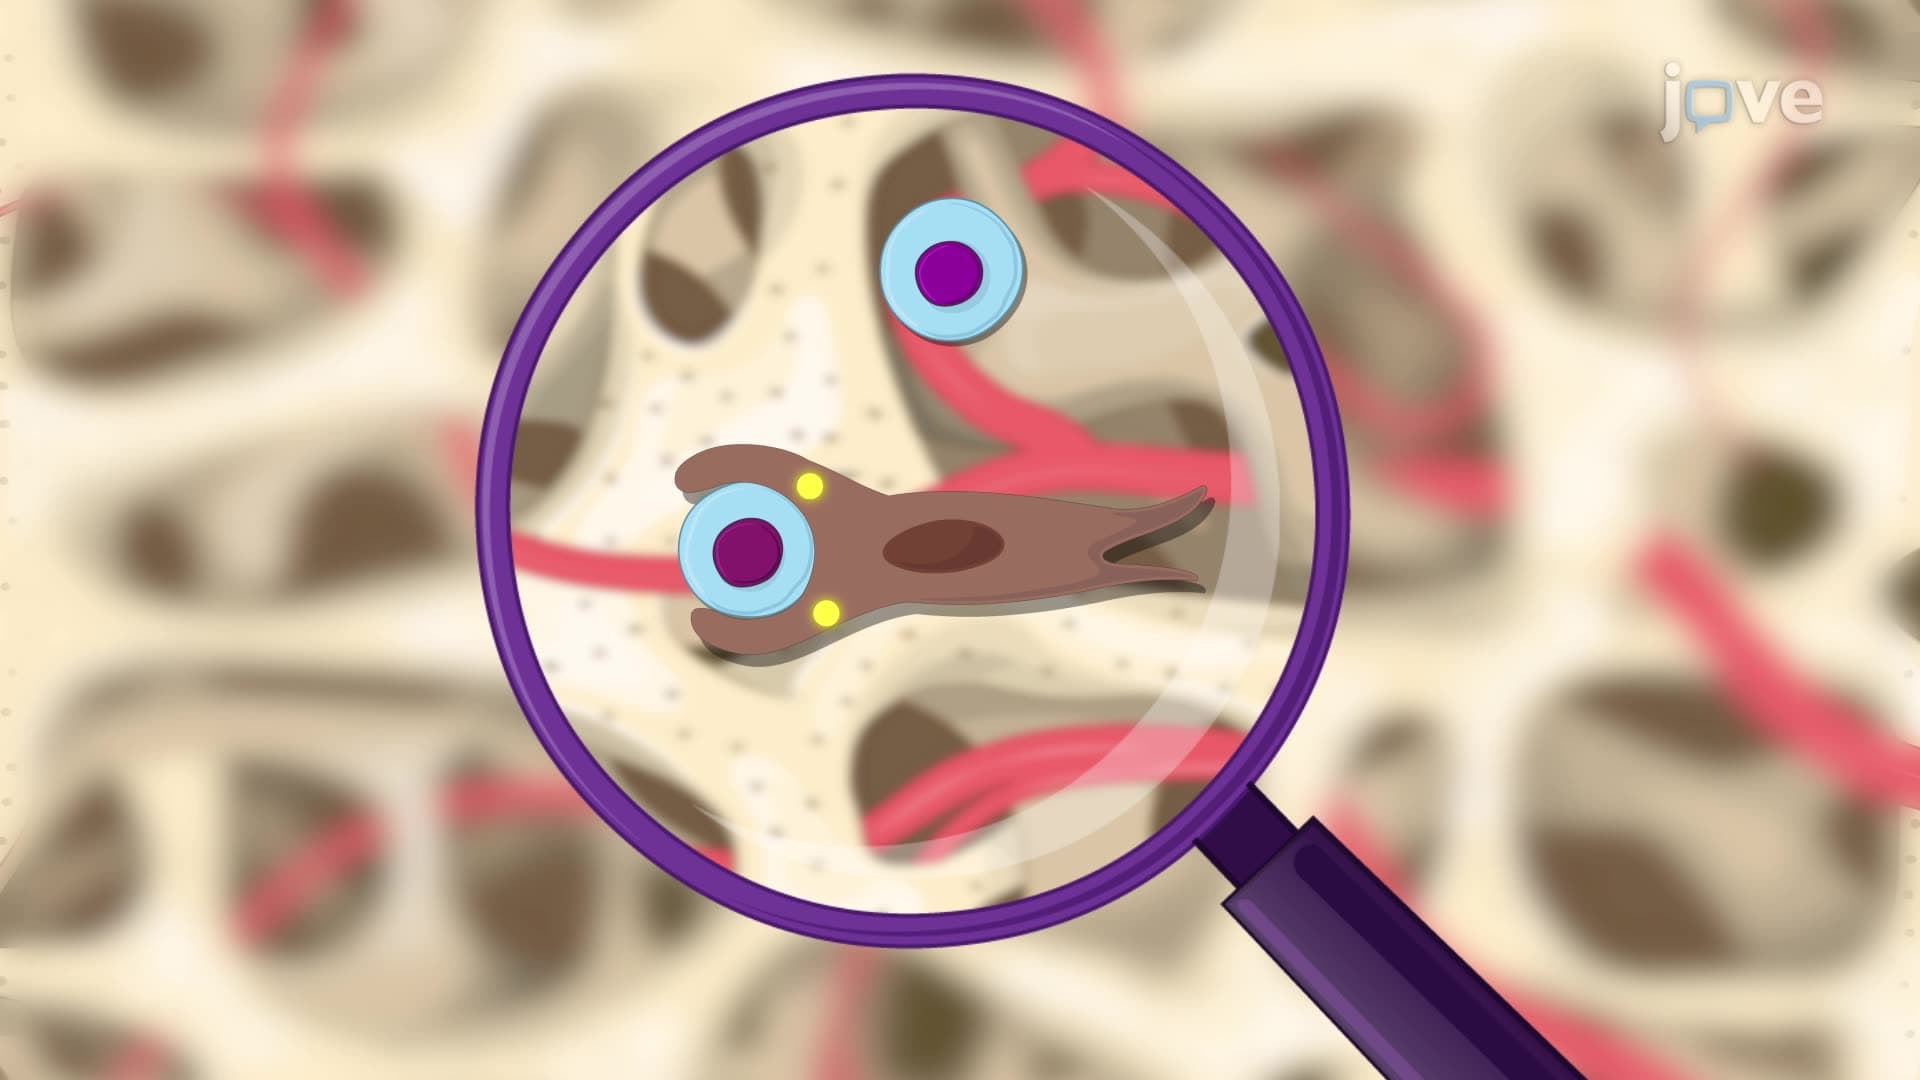 01:16
Primary Lymphoid Organs
The red bone marrow is a soft, spongy tissue nestled in the interior of long bones such as the humerus and femur. It is the site...
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...