Related Experiment Video
Updated: Aug 8, 2026

Methods to Assess Beta Cell Death Mediated by Cytotoxic T Lymphocytes
Published on: June 16, 2011
Heat-shock protein 65 as a beta cell antigen of insulin-dependent diabetes
D B Jones1, N R Hunter, G W Duff
1Department of Medicine, Western General Hospital, Edinburgh, UK.

Insights
Heat-shock protein 65 (HSP65) from Mycobacterium tuberculosis may be the primary beta-cell antigen in insulin-dependent diabetes. Autoimmunity to HSP65 might increase susceptibility to this autoimmune disease.
Area of Science:
- Immunology
- Endocrinology
- Microbiology
Background:
- The primary beta-cell antigen in insulin-dependent diabetes is a ~64 kD protein.
- Insulinoma cells synthesize this 64 kD protein upon stimulation with hyperthermia and cytokines like interleukin-1 beta, gamma interferon, and tumor necrosis factor.
Purpose of the Study:
- To investigate the identity of the 64 kD beta-cell antigen.
- To explore the potential role of heat-shock proteins in the pathogenesis of insulin-dependent diabetes.
Main Methods:
- Western blot analysis was used to assess cross-reactivity between the 64 kD beta-cell protein and antibodies against heat-shock protein 65 (HSP65) from Mycobacterium tuberculosis and Mycobacterium leprae.
- Inhibition assays were performed using serum from insulin-dependent diabetic patients.
Main Results:
- Cross-reactivity was observed between the 64 kD beta-cell protein and antibodies against Mycobacterium tuberculosis HSP65, but not against Mycobacterium leprae HSP65.
- Serum from insulin-dependent diabetic patients, containing antibodies to the 64 kD beta-cell antigen, inhibited the binding of Mycobacterium tuberculosis HSP65 antibodies to cytokine-treated cells.
Conclusions:
- Heat-shock protein 65 (HSP65) is suggested to be the 64 kD beta-cell antigen.
- Autoreactivity to an epitope of HSP65 may confer susceptibility to insulin-dependent diabetes mellitus.
Abstract:
The primary beta-cell antigen of insulin-dependent diabetes is thought to be a protein with a molecular weight of approximately 64 kD. Hyperthermic incubation and cytokines such as interleukin 1 beta, gamma interferon, and tumour necrosis factor induce synthesis of 64 kD protein by insulinoma cells. By western blot techniques, cross-reactivity was found between this 64 kD protein and monoclonal antibodies directed against Mycobacterium tuberculosis heat-shock protein 65, but not with antibodies directed against a similar epitope of M leprae heat-shock protein 65. Binding of M tuberculosis heat-shock protein 65 antibodies to interleukin-1 beta-treated cells was inhibited by prior addition of serum from insulin-dependent diabetic patients which contained antibodies to 64 kD beta-cell antigen. It is suggested that heat-shock protein 65 may be the 64 kD beta-cell antigen and that autoreactivity to an epitope of heat-shock protein 65 may confer susceptibility to insulin-dependent diabetes mellitus.


Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:25
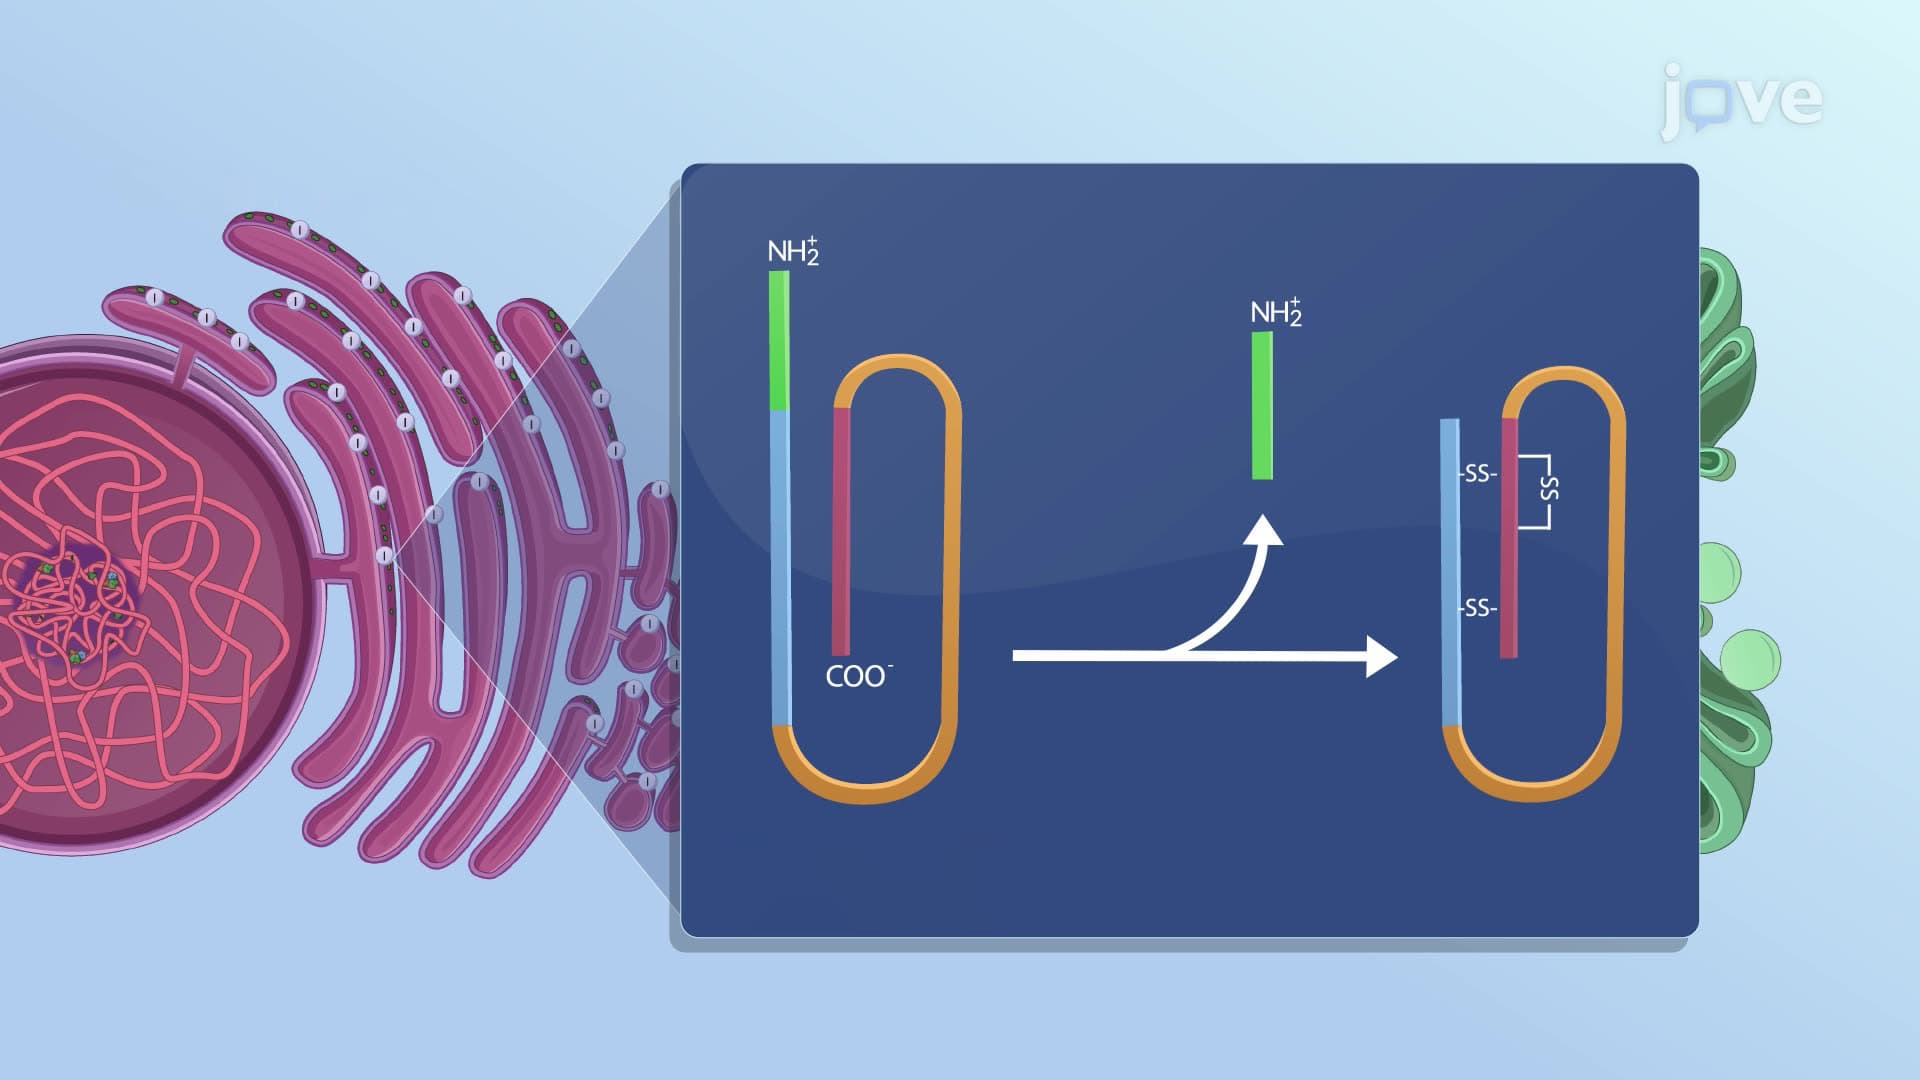
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:12
Type I Diabetes I: Introduction
 01:26
Type I Diabetes II: Pathophysiology