Related Experiment Video
Updated: May 14, 2026
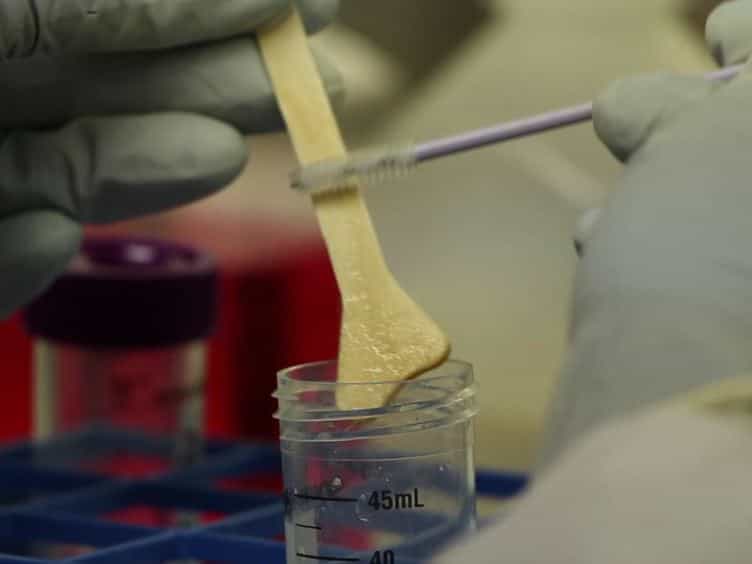

Collection, Isolation, and Flow Cytometric Analysis of Human Endocervical Samples
Published on: July 6, 2014
Cyclic changes in HIV shedding from the female genital tract during the menstrual cycle
Marcel E Curlin1, Wanna Leelawiwat, Eileen F Dunne
1Centers for Disease Control and Prevention, Atlanta, Georgia, USA. mcurlin@th.cdc.gov

Insights
Genital human immunodeficiency virus (HIV) shedding in women coinfected with herpes simplex virus type 2 varies during the menstrual cycle. Shedding is highest after menses and lowest at ovulation, impacting female-to-male HIV transmission risk.
Area of Science:
- Virology
- Immunology
- Gynecology
Background:
- Genital human immunodeficiency virus (HIV) shedding is a key factor in HIV transmission.
- Understanding shedding patterns throughout the menstrual cycle is crucial for assessing female-to-male transmission risk.
- Coinfection with herpes simplex virus type 2 (HSV-2) may influence HIV shedding.
Purpose of the Study:
- To investigate the relationship between the menstrual cycle and genital HIV shedding in women coinfected with HSV-2.
- To determine how HIV shedding varies across different phases of the menstrual cycle.
Main Methods:
- Prospective study involving 67 women with HIV type 1 and HSV-2 coinfection.
- Collection of genital samples across two menstrual cycles for HIV shedding analysis.
- Quantification of HIV shedding levels and assessment of variations by menstrual cycle phase and CD4 count.
Main Results:
- HIV shedding was detected in 60% (follicular), 48% (periovulatory), and 54% (luteal) of samples (P = .01).
- HIV shedding significantly declined from menses to ovulation (slope -0.054 log10 copies/swab/day, P < .001).
- Increased luteal phase shedding was observed in women with CD4 counts <350 cells/µL.
Conclusions:
- Genital HIV shedding frequency and magnitude fluctuate significantly during the menstrual cycle in reproductive-aged women.
- HIV shedding is greatest immediately following menses and lowest at ovulation.
- CD4 count influences luteal phase HIV shedding, suggesting immune status impacts transmission risk.
Abstract:
Factors increasing genital human immunodeficiency virus (HIV) shedding may increase female-to-male HIV transmission risk. We examined HIV shedding in 67 women with HIV type 1 and herpes simplex virus type 2 coinfection, during 2 menstrual cycles. Shedding occurred in 60%, 48%, and 54% of samples during the follicular, periovulatory, and luteal phases, respectively (P = .01). Shedding declined after menses until ovulation, with a slope -0.054 log10 copies/swab/day (P < .001), corresponding to a change of approximately 0.74 log10 copies between peak and nadir levels. Shedding increased during the luteal phase only among women with CD4 counts of <350 cells/µL. In reproductive-aged women, shedding frequency and magnitude are greatest immediately following menses and lowest at ovulation.


Related Concept Videos
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:19
Secretory Phase
Following ovulation, the corpus luteum, a temporary endocrine structure, produces progesterone and estrogens. These hormones stimulate the growth and coiling of endometrial...
 01:27
Ovarian Cycle
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...