Related Experiment Video
Updated: Sep 2, 2025
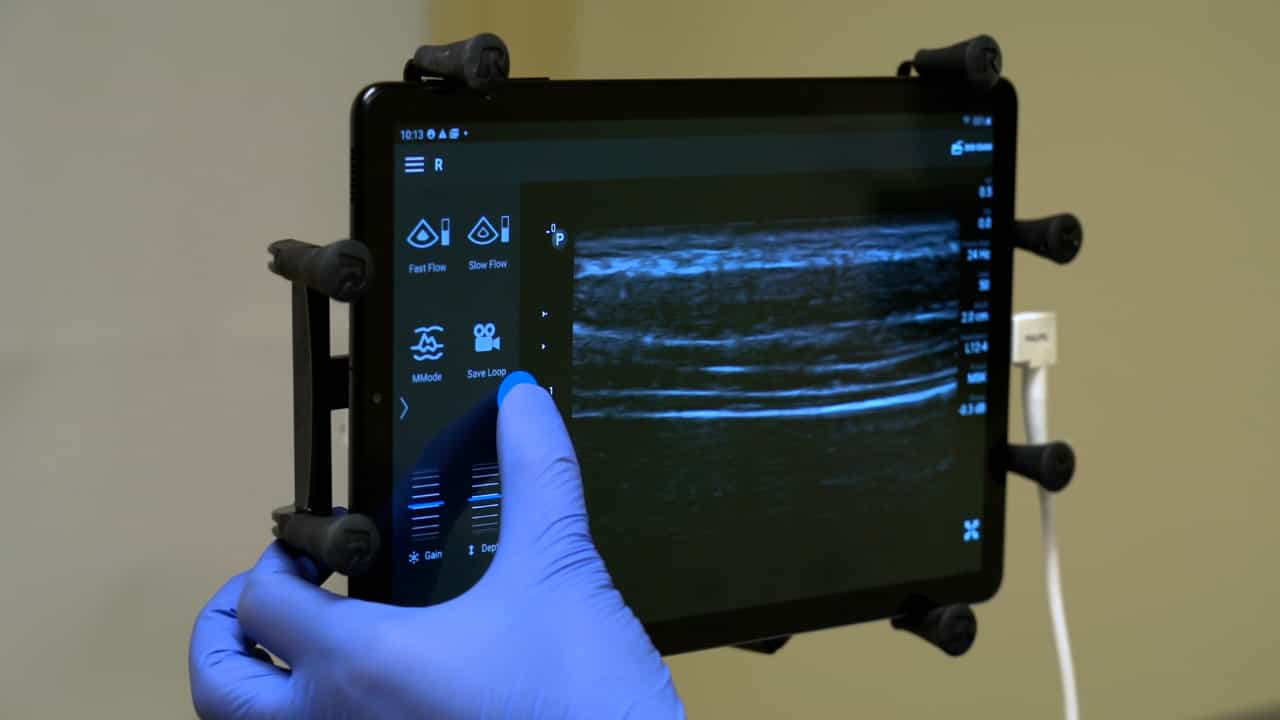

Author Spotlight: Unraveling the Impact of Mechanical Ventilation on Diaphragm Function and Patient Outcomes
Published on: November 3, 2023
Occurrence and Effects on Weaning From Mechanical Ventilation of Intensive Care Unit Acquired and Diaphragm Weakness:
Michele Bertoni1, Simone Piva1,2, Alessandra Beretta1
1Department of Anesthesia, Critical Care and Emergency, Spedali Civili University Hospital, Brescia, Italy.

Insights
Intensive care unit-acquired weakness (ICUAW) and diaphragm weakness (DW) frequently coexist in mechanically ventilated patients. ICUAW, not DW, significantly impacts ventilator-free days and weaning success.
Area of Science:
- Critical Care Medicine
- Neurology
- Pulmonology
Background:
- Mechanically ventilated (MV) patients often develop intensive care unit-acquired weakness (ICUAW) and diaphragm weakness (DW).
- The coexistence and impact of ICUAW and DW, particularly in cooperative versus uncooperative patients, remain unclear.
Purpose of the Study:
- To describe the co-occurrence of ICUAW and DW in MV patients.
- To evaluate the impact of ICUAW and DW on ventilator-free days (VFDs) and weaning success.
- To assess the correlation between maximal inspiratory pressure (MIP) and thickening fraction (TFdi) in patients with DW.
Main Methods:
- A prospective pilot study involving 73 critically ill MV patients.
- Muscle weakness assessed using the Medical Research Council score or simplified peroneal nerve test.
- Diaphragm dysfunction defined by MIP < 30 cm H2O or TFdi < 29%; weaning success defined by the WIND criteria.
Main Results:
- High prevalence of ICUAW (78%) and DW (81%) was observed, with co-occurrence in 65% of patients.
- ICUAW, but not DW, was independently associated with reduced VFDs at 28 days and lower likelihood of successful weaning (WIND).
- A significant but weak correlation was found between MIP and TFdi.
Conclusions:
- ICUAW and DW frequently coexist in MV patients, without a significant association between the two conditions.
- ICUAW is a significant predictor of prolonged ventilation and weaning failure, while DW is not.
- Larger studies are needed to confirm findings and explore advanced diagnostic methods for DW.
Purpose:
Limb intensive care unit (ICU)-acquired weakness (ICUAW) and ICU acquired diaphragm weakness (DW) occur frequently in mechanically ventilated (MV) patients; their coexistence in cooperative and uncooperative patients is unknown. This study was designed to (1) describe the co-occurrence of the two conditions (2) evaluate the impact of ICUAW and DW on the ventilator-free days (VFDs) at 28 days and weaning success, and (3) assess the correlation between maximal inspiratory pressure (MIP) and thickening fraction (TFdi) in patients with DW.
Methods:
This prospective pilot study was conducted in a single-center on 73 critically ill MV patients. Muscle weakness was defined as a Medical Research Council score < 48 in cooperative patients or a bilateral mean simplified peroneal nerve test < 5.26 mV in uncooperative patients. Diaphragm dysfunction was defined as MIP < 30 cm H2O or as a TFdi < 29%. Weaning success was defined according to weaning according to a new definition (WIND).
Results:
Fifty-seven patients (78%) had ICUAW and 59 (81%) had DW. The coexistence of the two conditions occurred in 48 patients (65%), without association (χ2 = 1.06, p = 0.304). In the adjusted analysis, ICUAW was independently related to VFDs at 28-days (estimate difference 6 days, p = 0.016), and WIND (OR of 3.62 for having WIND different than short weaning), whereas DW was not. The linear mixed model showed a significant but weak correlation between MIP and TFdi (p < 0.001).
Conclusion:
This pilot study is the first to explore the coexistence of ICUAW and DW in both cooperative and uncooperative patients; a lack of association was found between DW and ICUAW when considering both cooperative and uncooperative patients. We found a strong correlation between ICUAW but not DW with the VFDs at 28 days and weaning success. A future larger study is warranted in order to confirm our results, and should also investigate the use of transdiaphragmatic twitch pressure measurement during bilateral anterior magnetic phrenic nerve stimulation for the diagnosis of DW.

Related Concept Videos
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Acute Respiratory Failure-IV
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...