Related Experiment Video
Updated: May 5, 2026
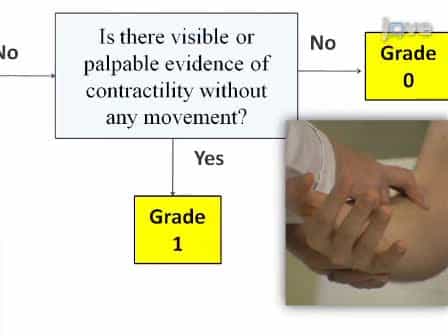

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Intensive Care Unit Acquired Weakness as a Modifiable Organ Dysfunction? A Narrative Review of Evolving Diagnostic
Moritz L Schmidbauer1, Konstantinos Dimitriadis1
1Department of Neurology, University Hospital LMU Munich, Marchioninistr. 15, 81377 Munich, Germany.

Insights
Intensive Care Unit Acquired Weakness (ICUAW) is common in critical illness, leading to poor outcomes. Early mobilization and neuromuscular electrical stimulation show promise for managing this condition.
Area of Science:
- Critical Care Medicine
- Neurology
- Rehabilitation Medicine
Background:
- Intensive Care Unit Acquired Weakness (ICUAW) affects up to 80% of high-risk critically ill patients.
- ICUAW is linked to prolonged ventilation, extended hospital stays, increased mortality, and long-term disability.
- It presents as tetraparesis and has heterogeneous pathophysiology, subclassified into Critical Illness Polyneuropathy (CIP), Myopathy (CIM), and Polyneuromyopathy (CIPNM).
Purpose of the Study:
- To review the prevalence, impact, diagnosis, and management of ICUAW.
- To highlight the need for refined definitions and targeted therapies for ICUAW.
- To emphasize the importance of multimodal strategies and long-term follow-up for improving patient outcomes.
Main Methods:
- Literature review of ICUAW prevalence, clinical definition, diagnostic tools, and therapeutic strategies.
- Analysis of current preventive measures focusing on metabolic factors and non-pharmacologic interventions.
- Discussion of the pathobiological heterogeneity and need for biologically refined definitions.
Main Results:
- ICUAW is a significant complication associated with severe patient outcomes and high healthcare costs.
- Diagnosis relies on the MRC Sum Score (<48), with limited utility of adjunct electrophysiologic studies.
- Preventive strategies include optimizing nutrition and avoiding overfeeding; early mobilization and neuromuscular electrical stimulation are promising non-pharmacologic treatments.
Conclusions:
- The multifactorial nature of ICUAW necessitates a biologically refined definition to guide targeted therapies.
- Comprehensive multimodal management and structured follow-up in Post-Intensive Care Syndrome (PICS) clinics are crucial.
- Improving outcomes for ICUAW requires a concerted effort in prevention, diagnosis, and rehabilitation.
Abstract:
Intensive Care Unit Acquired Weakness (ICUAW) is a highly prevalent neuromuscular complication affecting around 40% of critically ill patients, rising to over 80% in high-risk cohorts. It is independently associated with prolonged mechanical ventilation, increased intensive care unit (ICU) and hospital length of stay, elevated mortality (in-hospital, 1-year, and 5-year), higher healthcare costs, and long-term functional impairment. ICUAW is clinically defined by symmetric flaccid tetraparesis, frequently involving respiratory muscles, and exhibits significant pathobiological heterogeneity. Further subclassification is based on neurotopographic patterns: Critical Illness Polyneuropathy (CIP), Myopathy (CIM), and Polyneuromyopathy (CIPNM). Diagnosis typically relies on the Medical Research Council (MRC) Sum Score, with a threshold of <48 indicating clinically relevant weakness. While adjunct modalities such as electromyography/nerve conduction studies support assessment, their utility may be limited by patient cooperation and availability. Preventive strategies center on modifiable metabolic factors. Caloric and protein deficits exacerbate catabolism, while overfeeding-linked to anabolic resistance and stress hyperglycemia-also impairs recovery. To date, pharmacologic interventions remain inconclusive. However, early mobilization and neuromuscular electrical stimulation are promising non-pharmacologic strategies. The multifactorial and heterogeneous pathophysiology of ICUAW highlights the need for a biologically refined definition that can guide future targeted therapeutic interventions. Comprehensive multimodal strategies, together with structured long-term follow-up in Post-Intensive Care Syndrome (PICS) clinics, are essential for improving outcomes in this prevalent complication of critical care.

Related Concept Videos
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which...
 01:22
Acute Kidney Injury I: Introduction
 01:29
Acute Kidney Injury II: Pathophysiology
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:22
Acute Kidney Injury VI: Nursing Management
 01:22
Myasthenia Gravis ll: Pathophysiology