Related Experiment Video
Updated: Aug 14, 2026


Myocardial Infarction and Functional Outcome Assessment in Pigs
Published on: April 25, 2014
Rapid inward current in ischemically-injured subepicardial myocytes bordering myocardial infarction
E Patterson1, B J Scherlag, R Lazzara
1Department of Pharmacology, University of Oklahoma Health Sciences Center, Oklahoma City.

Insights
Enzymatically-dispersed myocytes accurately model electrophysiologic changes after myocardial infarction (MI). These changes, including altered membrane potential and Vmax, occur similarly in isolated cells and tissue, aiding MI research.
Area of Science:
- Cardiovascular Electrophysiology
- Myocardial Infarction Research
- Cellular Biology
Background:
- Investigating electrophysiological alterations in myocardial infarction (MI) is crucial for understanding cardiac dysfunction.
- Previous studies focused on intact tissue, but isolated cell models offer potential advantages for mechanistic studies.
Purpose of the Study:
- To determine if collagenase-dispersed epicardial myocytes overlying myocardial infarction (MI) reproduce the electrophysiological changes observed in intact epicardial tissue.
- To compare cellular electrophysiology in isolated myocytes versus multicellular tissue preparations at 1 and 4 days post-MI.
Main Methods:
- Utilized collagenase-dispersed epicardial myocytes and multicellular tissue preparations from canine subepicardium.
- Examined electrophysiologic properties, including membrane potential and Vmax, at 1 and 4 days after inducing myocardial infarction (MI).
- Assessed changes in response to varying extracellular potassium concentrations ([K0]+).
Main Results:
- Electrophysiologic changes in dispersed myocytes mirrored those in intact tissue preparations post-MI.
- Ischemically-injured myocytes exhibited depolarization and reduced membrane potentials compared to normal myocytes.
- On day 1 post-MI, reduced Vmax and prolonged recovery of Vmax from inactivation correlated with reduced membrane potentials.
- On day 4 post-MI, further alterations included a negative shift in Vmax inactivation, reduced maximal Vmax, and prolonged recovery from inactivation.
Conclusions:
- Enzymatically-dispersed myocytes effectively replicate altered cellular electrophysiology observed in multicellular tissue preparations following MI.
- Post-MI conduction and refractoriness changes are primarily driven by reduced membrane potential at day 1.
- At day 4, slowed conduction and prolonged refractoriness are further influenced by reduced maximal Vmax and altered inactivation properties.
Introduction:
To determine if collagenase-dispersed epicardial myocytes overlying myocardial infarction reproduce the same altered electrophysiology observed in intact epicardium, multicellular tissue preparations and enzymatically-dispersed myocytes from ischemically-injured canine subepicardium were examined 1 and 4 days after myocardial infarction.
Methods And Results:
The electrophysiologic changes observed with ischemic injury in enzymatically-dispersed myocytes were not different from changes observed in multicellular tissue preparations at 1 and 4 days postinfarction. Ischemically-injured myocytes were depolarized versus normal myocytes at [K0]+ (2.5 to 40 mM) with reduced membrane potentials also observed in injured subepicardial tissue preparations [K0]+ (4 to 24 mM). On day 1, the reduced Vmax and the prolonged recovery of Vmax from inactivation were consistent with the reduced membrane potentials observed at each [K0]+. The half-maximal Vmax, maximal Vmax, and Boltzmann constant (k) in injured myocytes were unchanged versus normal myocytes. On day 4 postinfarction, the half-maximal Vmax was shifted to a more negative membrane potential, the maximal Vmax was reduced, and k was increased in injured versus normal myocytes. Prolonged recovery from inactivation was observed with depressed membrane potentials in injured myocytes on day 4.
Conclusion:
Enzymatically-dispersed myocytes from ischemically-injured subepicardium closely reproduce altered cellular properties observed in multicellular tissue preparations. The data suggest that 1 day postinfarction, altered conduction and refractoriness largely result from a reduced membrane potential. At 4 days, a reduced maximal Vmax, a shift in the inactivation curve to more negative voltages, and prolonged recovery of Vmax from inactivation also contribute to slowed conduction and prolonged refractoriness.
Related Concept Videos
 01:30
Cardiac Action Potential
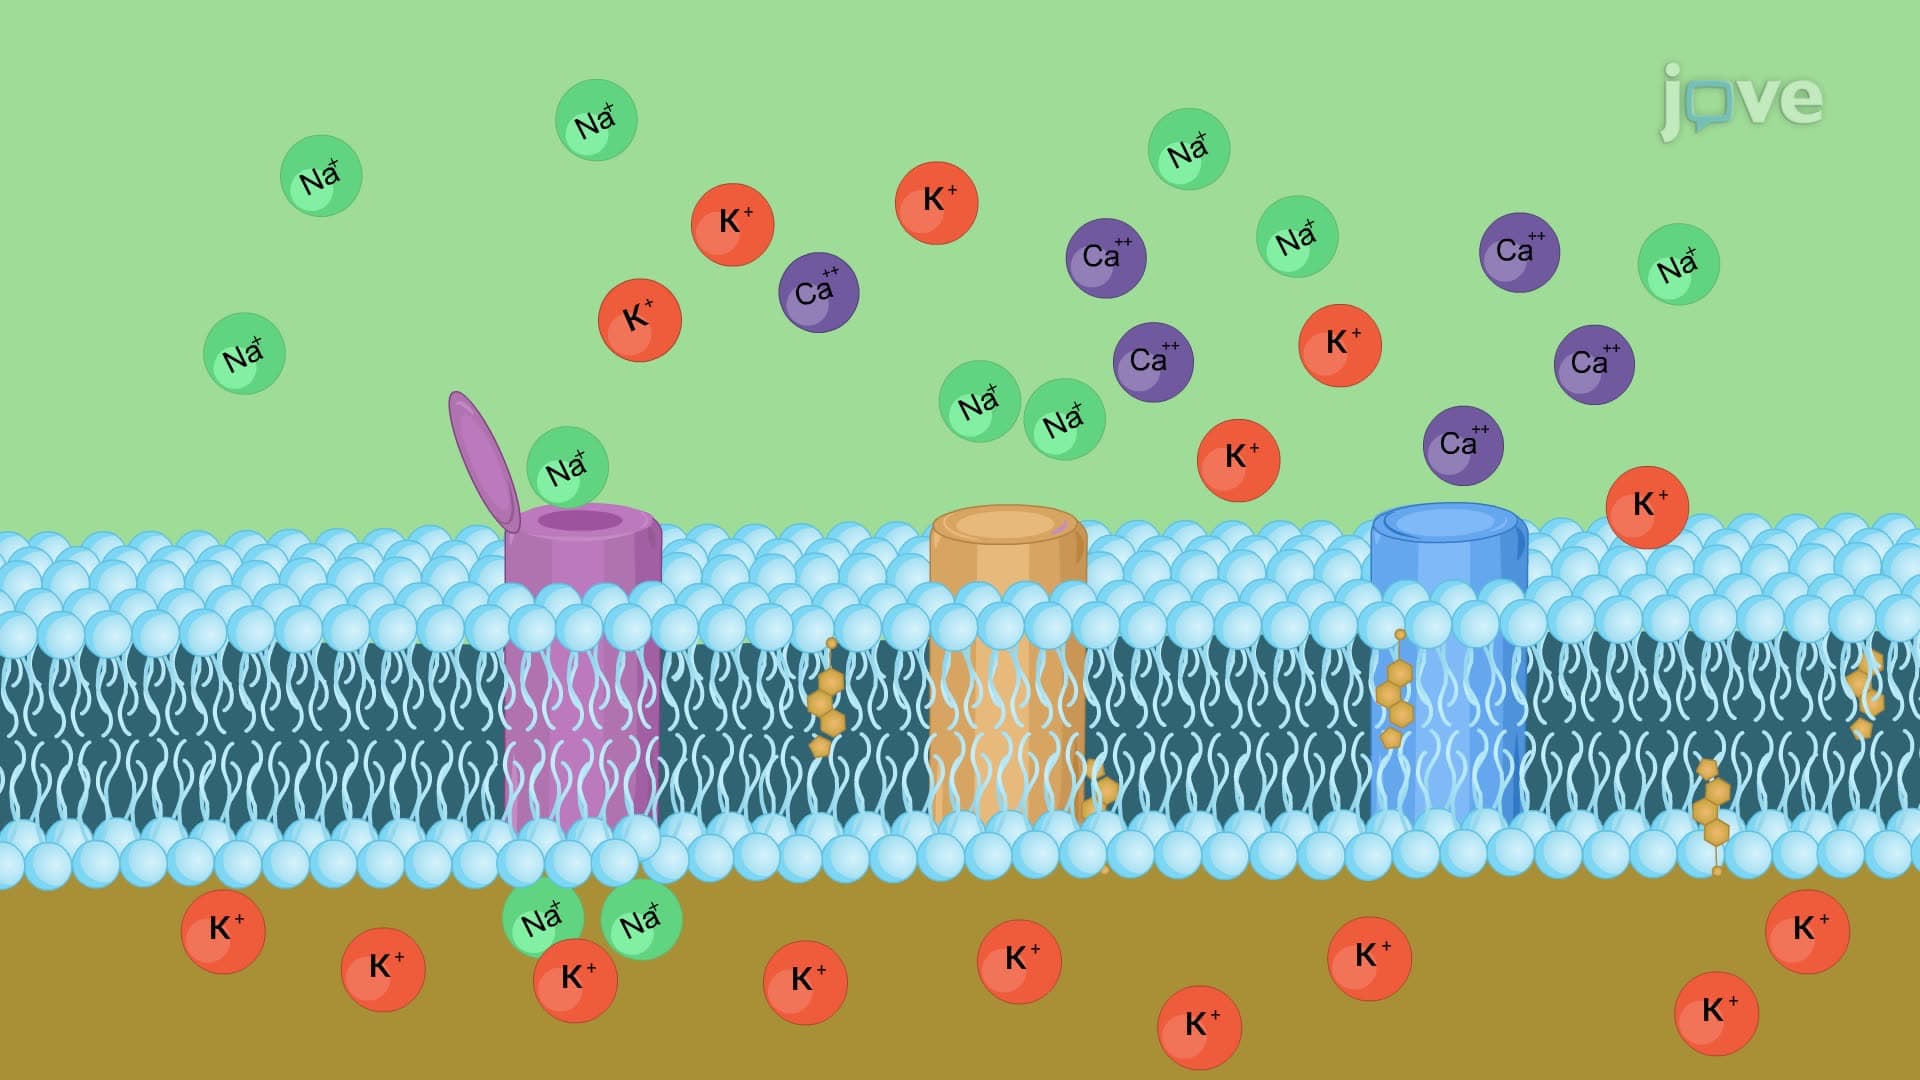
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:21
Myocarditis I: Introduction
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:30
Acute Coronary Syndrome I: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology