Related Experiment Video
Updated: Aug 13, 2026


Staining Protocols for Human Pancreatic Islets
Published on: May 23, 2012
Insulin injection sites: morphology and immunohistochemistry

Insights
Insulin was detected in injection sites 24 days after a non-diabetic woman
Area of Science:
- Forensic pathology
- Toxicology
- Endocrinology
Background:
- Detection of exogenous insulin in forensic investigations is crucial for determining the cause of death.
- Standard histological techniques can be challenging for preserving and detecting protein-based substances like insulin.
Observation:
- Insulin was identified in formalin-fixed, paraffin-embedded subcutaneous injection sites 24 days post-mortem.
- Birefringent crystalline material, likely zinc phosphate, was observed.
- Immunohistochemistry revealed granular insulin deposits and insulin staining on lipocyte membranes.
Findings:
- Granular insulin depots and membrane-bound insulin were visualized using immunohistochemistry.
- A granulocytic inflammatory cellular reaction with insulin uptake by inflammatory cells was present.
- Insulin was successfully detected despite a significant post-mortem interval and routine tissue processing.
Implications:
- This study demonstrates the feasibility of detecting insulin in fixed tissues long after death.
- The findings support the utility of immunohistochemistry in forensic toxicology cases involving insulin.
- This method can aid in confirming insulin administration in cases of suspected suicide or homicide.
Abstract:
In a case of insulin suicide in a nondiabetic woman, insulin was detected in routinely formalin fixed and paraffin embedded subcutaneous injection marks, in spite of a post-morterm interval of 24 days. Around birefringent crystalline material, probably zinc phosphate, immunohistochemistry revealed granular insulin depots as well as an insulin staining along the lipocyte membranes. A cellular reaction of granulocytic character was present, with an uptake of insulin by inflammatory cells.


Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:25
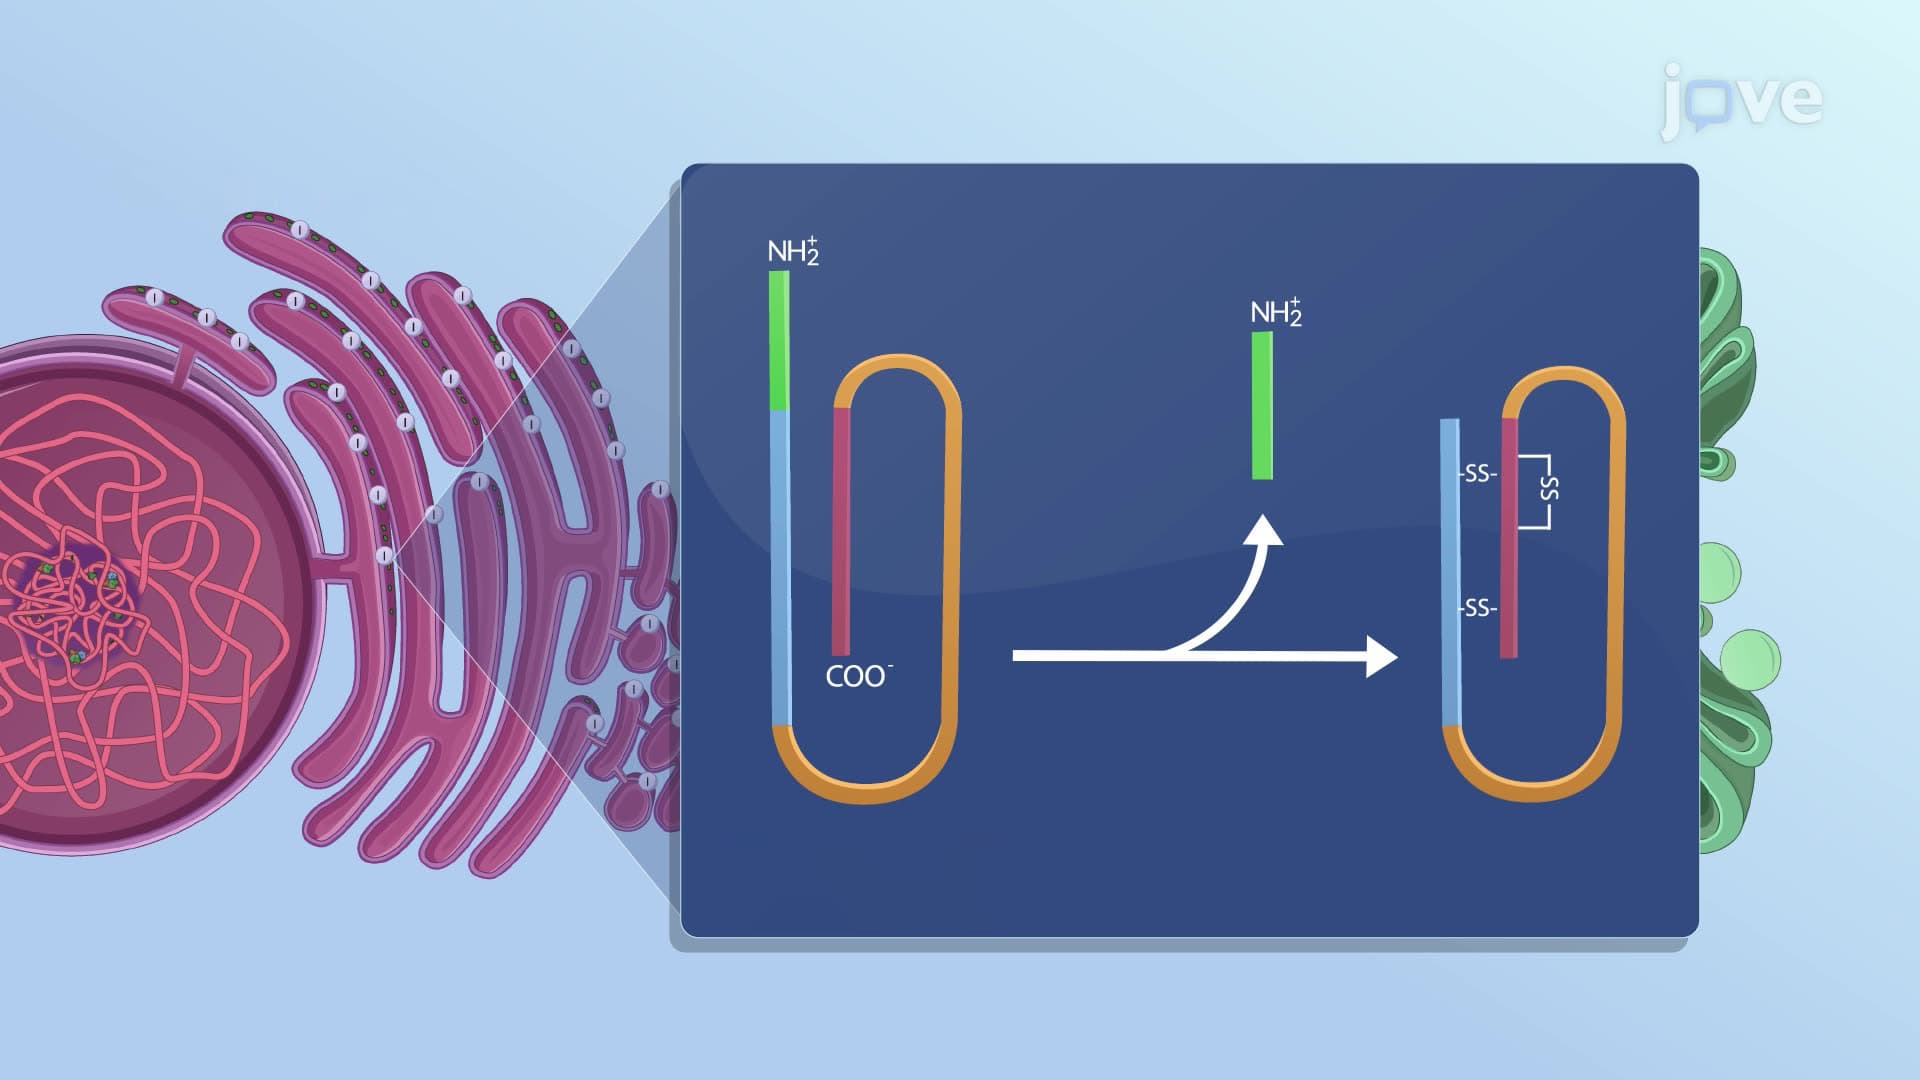
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:12
Type I Diabetes I: Introduction