Related Experiment Video
Updated: Aug 8, 2026


Identifying Dysregulated Genes Induced by Kaposi's Sarcoma-associated Herpesvirus (KSHV)
Published on: September 15, 2010
Lymphomas associated with HIV infection

Insights
Lymphomagenesis in HIV patients involves complex interactions. Epstein-Barr virus (EBV) plays a role in various lymphomas, with different EBV statuses observed in Burkitt and diffuse large cell lymphomas.
Area of Science:
- Oncology
- Virology
- Immunology
Background:
- Lymphomagenesis in Human Immunodeficiency Virus (HIV)-positive patients is complex and not fully understood.
- Non-Hodgkin lymphomas (NHL) in HIV patients are predominantly B-cell type.
- Epstein-Barr virus (EBV) is implicated in the development of these lymphomas.
Purpose of the Study:
- To elucidate the complex mechanisms of lymphomagenesis in HIV-positive individuals.
- To differentiate the characteristics of various lymphoma subtypes in the context of HIV infection.
- To investigate the role of Epstein-Barr virus (EBV) in HIV-associated lymphomas.
Main Methods:
- Analysis of lymphoma subtypes based on CD4 counts and disease progression in HIV patients.
- Assessment of MYC gene rearrangement in lymphoma cases.
- Evaluation of Epstein-Barr virus (EBV) status, including EBNA2 and LMP1 expression, and association with specific lymphoma types.
Main Results:
- Burkitt lymphoma occurs early in HIV infection (CD4 > 200/µL), often with MYC rearrangement and EBV negativity (EBNA2/LMP1-).
- Diffuse large cell lymphomas occur late in HIV infection (CD4 < 50/µL), with worse prognosis, MYC rearrangement in 30-40%, and EBV positivity (EBNA2/LMP1+).
- HIV-associated Hodgkin disease (HD) shows aggressive behavior, with neoplastic cells consistently EBV positive.
Conclusions:
- Lymphomagenesis in HIV is multifactorial, involving immune deficiency, EBV, other viruses, gene rearrangements, and cytokines.
- Distinct EBV profiles characterize different HIV-associated lymphoma subtypes.
- HIV-associated lymphomas, including HD, exhibit unique epidemiological and etiological features compared to non-HIV counterparts.
Abstract:
Lymphomagenesis in HIV positive patients is a complex phenomenon not yet completely understood (Karp and Broder, 1992). The great majority of NHL are of the B cell type. Burkitt lymphoma seems to develop early during the evolution of HIV infection in patients with a CD4 count above 200/microliter. MYC is rearranged in the majority of the cases. EBV latent infection is observed in 30-45%. EBV status is characterized by a negativity for EBNA2 and LMP1 The main sites of the tumour are the lymph node and the bone marrow. Diffuse large cell lymphomas, mostly represented by immunoblastic lymphomas with plasmacytoid differentiation and by centroblastic lymphomas rich in immunoblasts, are a late event in HIV infection, in patients with a low CD4 count (often below 50/microliter). The prognosis is worse than in Burkitt and Burkitt like lymphoma. MYC is rearranged in about 30-40% of the cases, whereas more than 70% are EBV positive. EBV status is characterized by a positivity for both EBNA2 and LMP1. B type ALC lymphomas are more frequently associated with EBV than in the general population and exhibit the same EBV status as diffuse large cell lymphomas. HD occurs at any stage of HIV infection. The majority of patients are in clinical stage III or IV at the time of diagnosis, and HIV associated HD shows a more aggressive course than non-HIV HD. Many cases remain difficult to classify; instead, the immunophenotype of neoplastic cells is similar to that in HD occurring in the general population. Histiocytes and epithelioid cells are even more numerous than T lymphocytes, and the CD4:CD8 ratio is low. Neoplastic cells are EBV positive in most or all cases, although they are consistently HIV negative by in situ hybridization. Lymphomagenesis seems to be very complex, with multiple agents acting together or successively. EBV, other viruses, rearrangement of various genes and production of cytokines all seem to have major roles in addition to immune deficiency.
More Related Videos
 07:21
Processing of Bronchoalveolar Lavage Fluid and Matched Blood for Alveolar Macrophage and CD4+ T-cell Immunophenotyping and HIV Reservoir Assessment
Published on: June 23, 2019
 07:17
Wild-type Blocking PCR Combined with Sanger Sequencing for Detection of Low-frequency Somatic Mutation
Published on: August 23, 2024
Related Concept Videos
 01:18
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
 01:16
Primary Lymphoid Organs
The red bone marrow is a soft, spongy tissue nestled in the interior of long bones such as the humerus and femur. It is the site...
 01:15
Secondary Lymphoid Organs
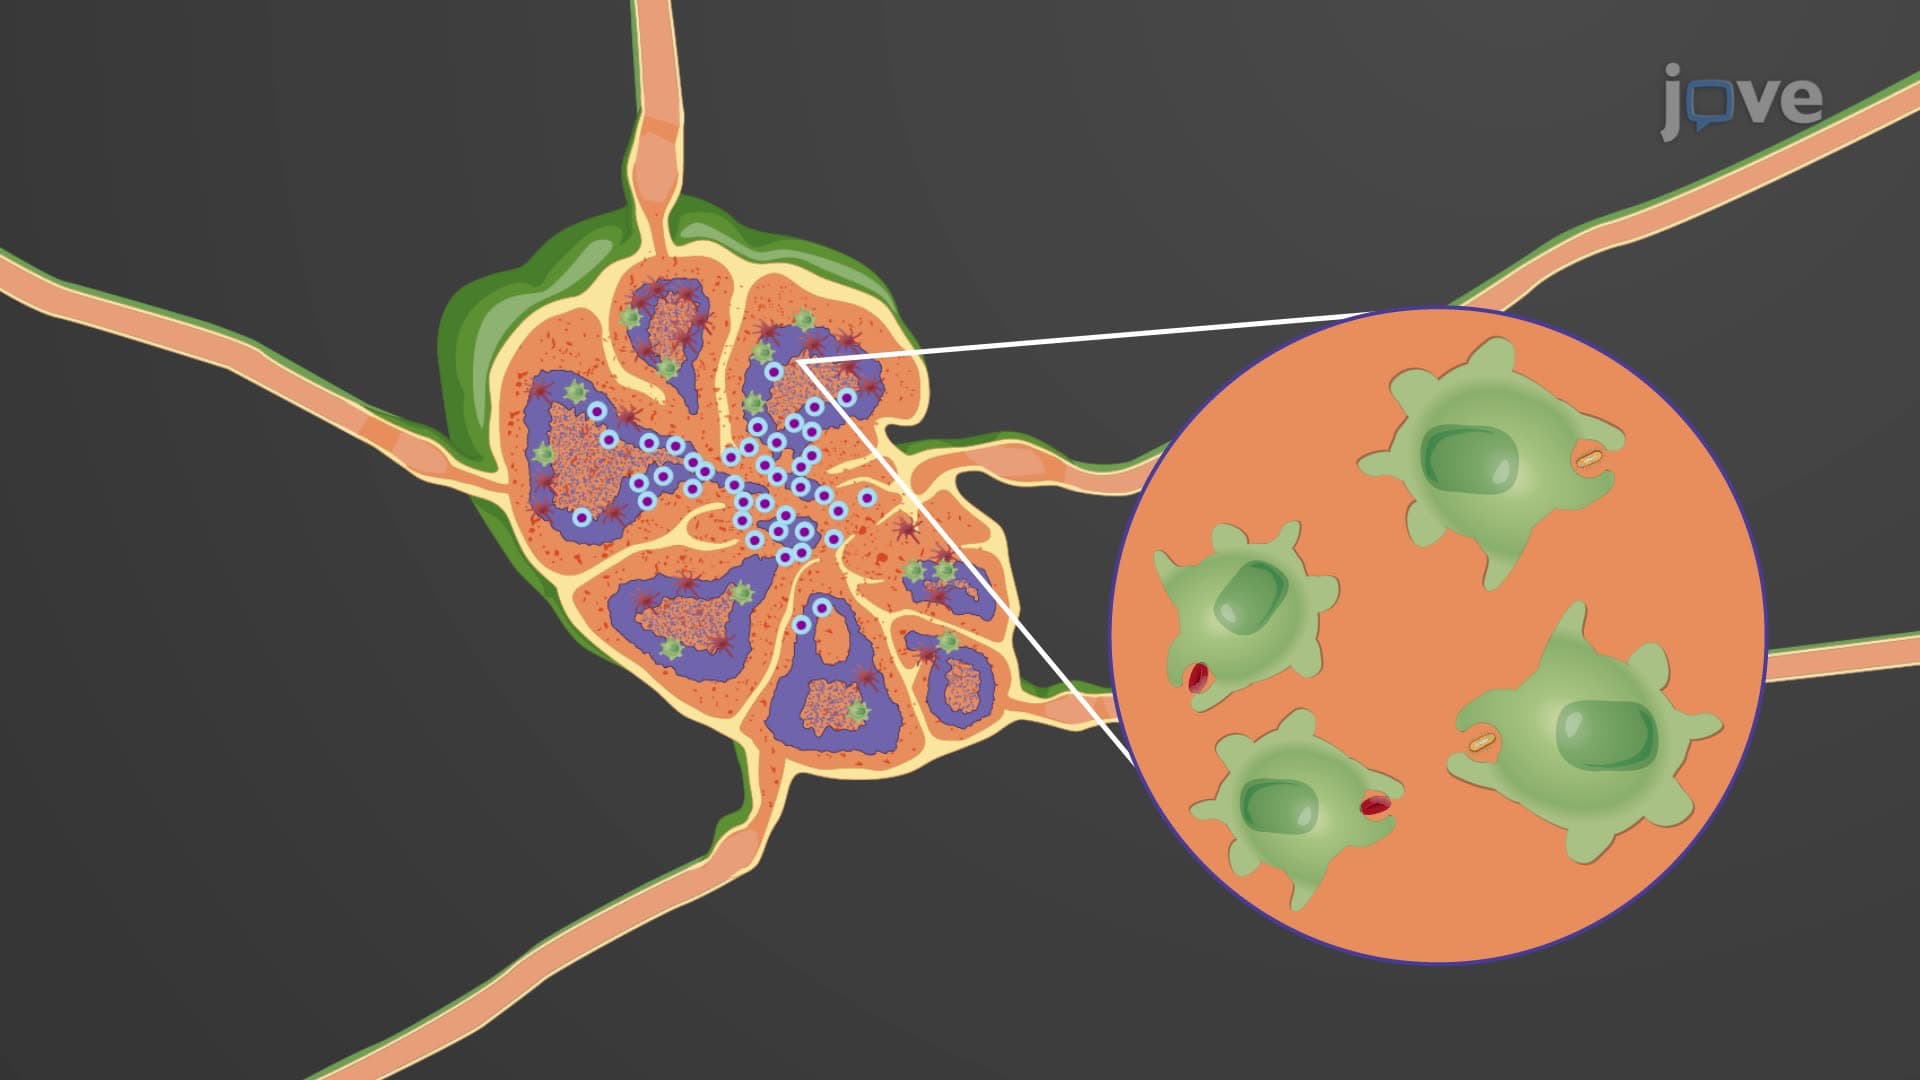
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency disorders...
 01:26
Sexually Transmitted Infections
 01:27
Cryptococcal Meningitis