Related Experiment Video
Updated: Aug 6, 2026
Robotic Enucleation of an Intra-Pancreatic Insulinoma in the Pancreatic Head
Published on: January 3, 2020
Incidence of pancreatitis in patients undergoing sphincter of Oddi manometry (SOM)
M E Maldonado1, P G Brady, J J Mamel
1Department of Internal Medicine, University of South Florida College of Medicine, Tampa 33612, USA.

Objective:
Sphincter of Oddi manometry (SOM) is a useful diagnostic procedure when evaluating patients with unexplained biliary pain or idiopathic recurrent pancreatitis. Acute pancreatitis is a recognized complication of SOM whose pathogenesis appears to be multifactoral. We conducted this study to determine the incidence of pancreatitis in patients after SOM and to identify any variables that may lead to an increased incidence of pancreatitis.
Methods:
A retrospective review of 100 consecutive patients who underwent SOM between 1992 and 1996 at two university-affiliated hospitals was done. SOM was performed using a triple lumen catheter with each lumen perfused at a rate of 0.25 cc/min using an Arndorfer pneumohydraulic capillary perfusion system. The following data were recorded: age, gender, clinical type of sphincter of Oddi dysfunction, length of procedure, doses of medications used, duct cannulated, sphincter of Oddi pressure, whether endoscopic retrograde cholangiopancreatography (ERCP) with or without sphincterotomy was performed, and the number of patients developing pancreatitis. Statistical analysis was performed using a T test, chi2, and multiple regression analysis.
Results:
The overall incidence of pancreatitis was 17%. Six patients with type II SO dysfunction and 11 patients with type III SO dysfunction developed pancreatitis. The incidence of pancreatitis was significantly lower in those patients who only had SOM, compared with those patients who had SOM and ERCP (9.3% vs 26.1%, p < 0.026). There was no significant correlation between age, gender, duration of procedure, dose of midazolam used, sphincter of Oddi pressure, or type of SO dysfunction with the development of SOM-induced pancreatitis. Multiple regression analysis showed that sphincterotomy added no additional risk, beyond that associated with ERCP, for the development of pancreatitis.
Conclusions:
The results of this study indicate that the incidence of pancreatitis was highest when SOM was followed by ERCP. A potential method of decreasing the incidence of pancreatitis after SOM is performing ERCP with or without sphincterotomy at another session, separated from the SOM by at least 24 h. Before this can be definitely recommended, the results of this study must be validated by others or by a prospective study.
Related Concept Videos
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:24
Chronic Pancreatitis I: Introduction
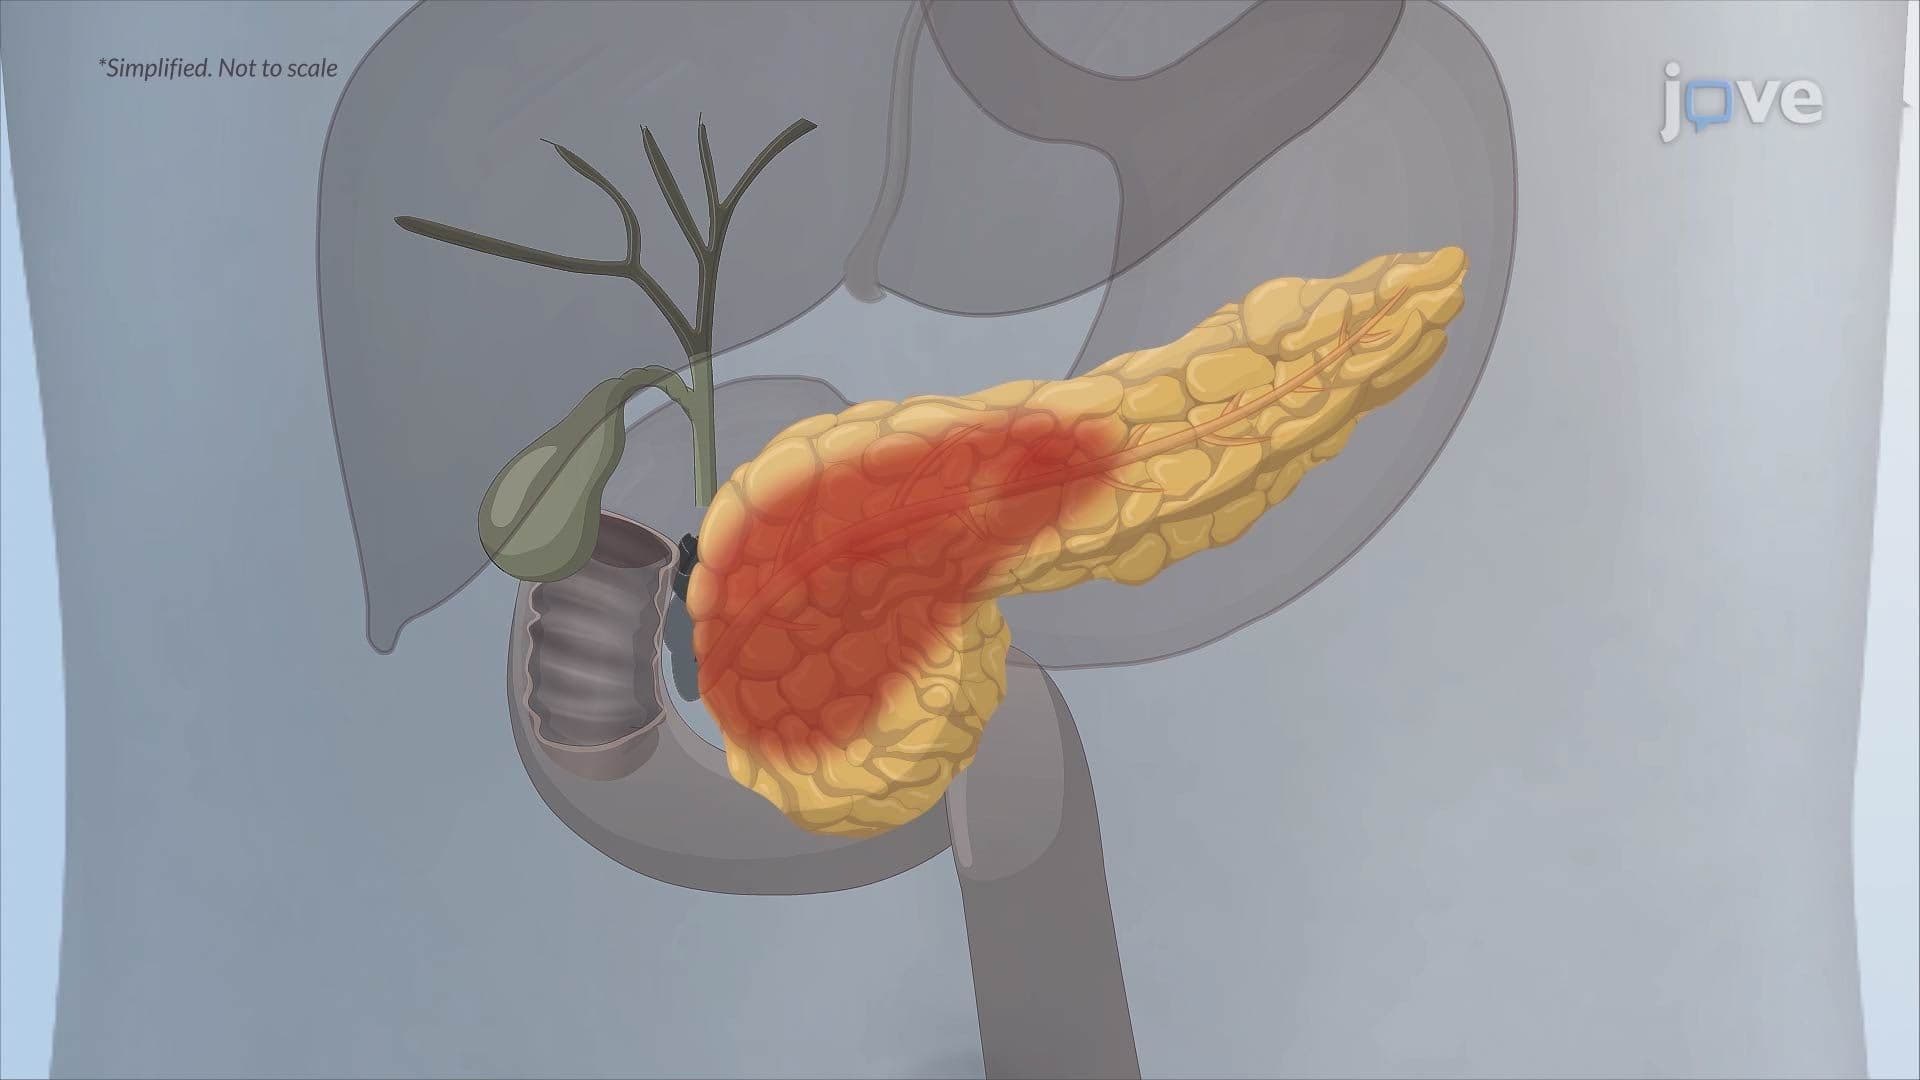
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Acute Pancreatitis I: Introduction
 01:25
Chronic Pancreatitis I: Introduction