Related Experiment Video
Updated: Aug 19, 2026


Assessment of Kidney Function in Mouse Models of Glomerular Disease
Published on: June 30, 2018
Screening school children for albuminuria, proteinuria and occult blood with dipsticks

Insights
This study evaluated urine dipsticks for screening schoolchildren for kidney disorders. Albumin screening is recommended over protein screening due to higher accuracy in detecting genitourinary issues.
Area of Science:
- Nephrology
- Pediatric Nephrology
- Diagnostic Medicine
Background:
- The Japanese Ministry of Health Welfare initiated proteinuria screening in schoolchildren in 1974.
- Genitourinary disorders can be detected early through urinalysis, with albuminuria increasingly recognized as a key indicator of renal disease risk.
Purpose of the Study:
- To evaluate the accuracy of new urine dipsticks for measuring albumin and protein concentrations in schoolchildren.
- To compare the effectiveness of albuminuria screening versus proteinuria screening for genitourinary disorders.
Main Methods:
- Assessed dipstick accuracy using adult patient specimens and applied findings to a cohort of 6197 schoolchildren.
- Established cutoffs for "low risk" as <150 mg/l for protein and <30 mg/l for albumin.
- Evaluated dipstick sensitivity and specificity for both protein and albumin, and analyzed albumin-to-creatinine ratio.
Main Results:
- Protein dipstick sensitivity/specificity was 95.1%/95.5%; albumin dipstick was 83.8%/93.8%.
- Albuminuria screening demonstrated comparable sensitivity/specificity (79.3%/94.4%) to protein screening.
- Estimated prevalence of albuminuria at 2.1% and proteinuria at 4.3% in the studied school population. Albumin-to-creatinine ratio showed promise in reducing false positives/negatives.
Conclusions:
- Albumin screening is recommended over protein screening for detecting genitourinary disorders in schoolchildren.
- Adjusting albumin dipstick cutoffs may improve sensitivity and reduce false negatives.
- The albumin-to-creatinine ratio appears to be a valuable tool for risk assessment in pediatric populations.
Abstract:
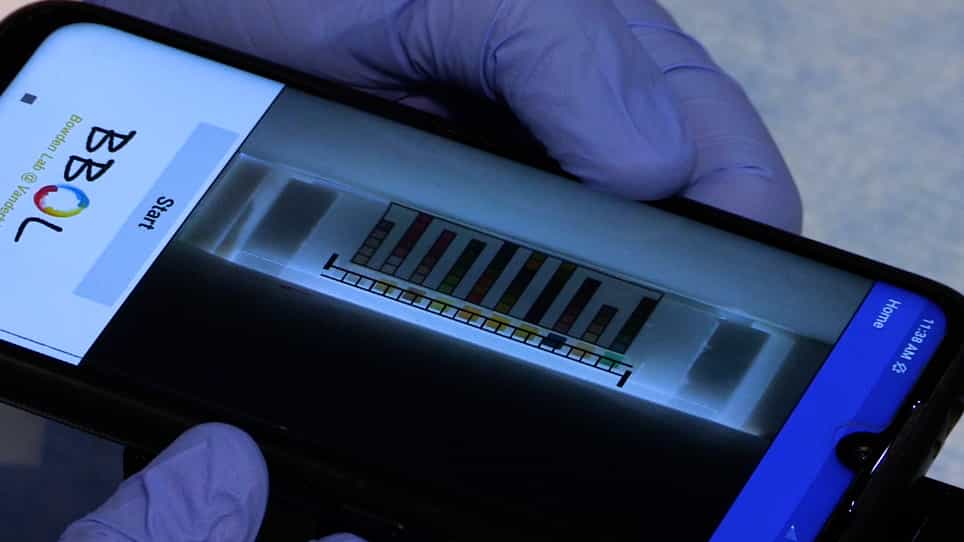
Beginning in 1974, the Japanese Ministry of Health Welfare directed the screening of schoolchildren for proteinuria. We studied their procedure and methods in 6197 school children and also evaluated a new urine dipstick that measures albumin concentrations down to about 10 mg/l and creatinine down to about 300 mg/l. We used specimens from adult in- and outpatients to test the accuracy of the dipsticks. Based on the quantitative results, we set as cutoffs < 150 mg/l for protein and < 30 mg/l for albumin as the concentrations representing "low risk." The quantitative values were assumed to be correct, and the dipstick results were judged accordingly, i.e., a dipstick protein of > or = "150" mg/l or an albumin of I "30" mg/l indicated increased risk of developing or having a genitourinary disorder. The sensitivity/specificity of the protein dipstick was 95.1%/95.5%, and the same for the albumin dipstick was 83.8%/93.8%. The cut-off for the albumin dipsticks probably should be set somewhat lower to reduce the number of false negatives and increase the sensitivity of the dipstick. When we compared the quantitative albumin to the protein dipsticks with the above cut-offs, we found the sensitivity/specificity to be 79.3%/94.4%, i.e., much like the albumin dipstick results. The many reports on the association of albuminuria and risk of renal disease recommend that screening should be done for albumin rather than protein. Based on the data from the school children, we estimate that a dipstick albumin of "30" mg/l is borderline increased risk, and that a protein dipstick of "150" mg/l is the same. If we call the dipstick "10" mg/l albumin, "30" mg/l albumin and the "150" mg/l protein results "low risk," then we estimate the prevalence of albuminuria in the school children to be about 2.1% and proteinuria to be about 4.3%. Children with these values should have a quantitative test for albumin and protein. We also tested a dipstick for creatinine and found increasing values with increasing age in both genders; the older boys had significantly higher creatinine values than the older girls and younger boys. For the albumin/creatinine ratio, we found 6028 children with a ratio of < 30 mg/g indicating low risk and 159 children with a ratio of > or = 30 mg/g indicating increased risk. The ratio may be more useful owing to the likely reduction of the number of false negatives and false positives.
Related Concept Videos
 01:30
Serum Laboratory Studies, Stool Test, Breath Test
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:29
Urine Studies I: Urinalysis
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis
 01:28
Diabetic Nephropathy