Related Experiment Video
Updated: Oct 19, 2026
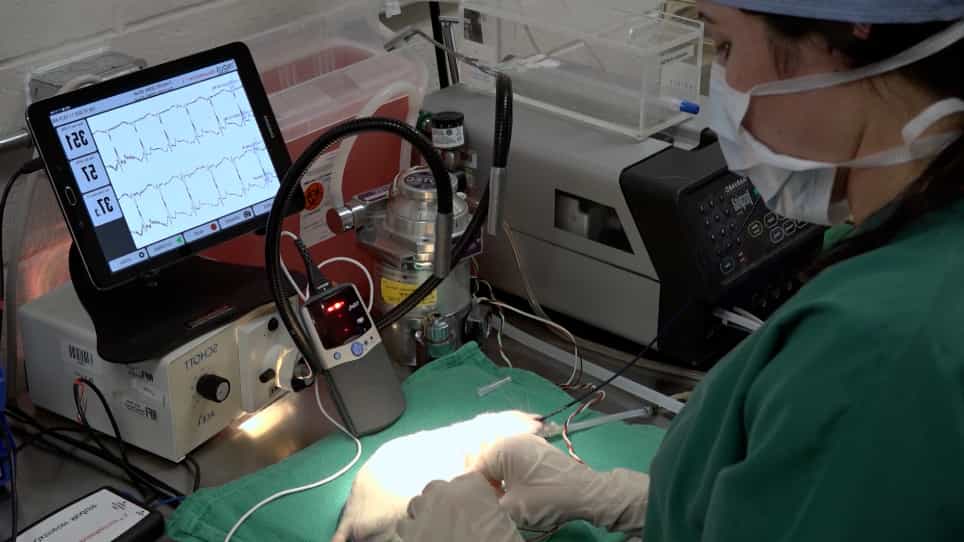
An Image Guided Transapical Mitral Valve Leaflet Puncture Model of Controlled Volume Overload from Mitral Regurgitation in the Rat
Published on: May 19, 2020
Mitral valve compensation for annular dilatation: in vitro study into the mechanisms of functional mitral
1School of Biomedical Engineering, Georgia Institute of Technology, Atlanta 30332-0535, USA.

Background And Aim Of The Study:
Mitral annulus dilatation has been identified as an important factor in functional mitral regurgitation (FMR). However, the pathophysiologic interaction of annular dilatation and papillary muscle (PM) displacement in FMR, which occurs clinically in left ventricular (LV) dilatation, is still not well understood. It is difficult to separate these competing factors in vivo, leading to confusion in identifying the real role of the annular dilatation in FMR and its interaction with PM displacement.
Methods:
To better understand the competing factors, an in vitro model was developed with a D-shaped adjustable mitral annulus that could be changed from 5.5 cm2 to 13.0 cm2 during experiments, independent of varying PM positions. Six excised normal porcine mitral valves were mounted in a left ventricular model with the adjustable annulus device and tested in a physiologic pulsatile flow system under normal cardiac output and left ventricular pressure (5.0 l/min, 120 mmHg). Papillary muscles were placed in normal and then displaced to an apical posterolateral position, to simulate pathological conditions seen clinically. Regurgitation was measured directly by a flow probe and the mitral valve geometry and leaflet coaptation were recorded by video camera through the model's atrium window. In addition, 2D echocardiography was used to evaluate leaflet coaptation and color Doppler flow mapping to detect the regurgitant flow field.
Results:
The results showed that in normal PM position, the mitral regurgitant was consistently at low level until the annulus was enlarged to 1.75 times the normal size, at which time it increased sharply. Papillary muscle apical posterolateral displacement, which simulates a dilated LV, caused regurgitation to occur earlier (1.5 times the normal annulus size), and had an increased regurgitant volume (p < 0.05). The leaflet gaps were first observed at the commissural areas of the valves, consistent with the location of regurgitant jets detected by color Doppler flow mapping. Asymmetric PM displacement created more regurgitation than both the symmetric PM tethering (p = 0.063) and normal PM position (p < 0.01). The regurgitant jets were observed at the same commissural side as the PM displacement, even without significant enlargement of the annulus.
Conclusions:
This in vitro study provides insight into the interaction between annular dilatation and PM displacement on FMR. The resulting effects and their overall similarity to clinical observation could help further understand the mechanism of FMR and provide additional information to improve future therapeutic strategies.

Related Concept Videos
 01:27
Mitral Valve Prolapse I: Introduction
 01:25
Mitral Regurgitation III: Medical Management
 01:20
Mitral Regurgitation I: Introduction
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:22
Mitral Stenosis I: Introduction